Cold Cream
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes cold cream as an ointment containing a significant amount of water, designed to cool the skin through evaporation. It discusses the historical formulation techniques, including the use of emulsifiers like borax, mucilage, and lanolin, and notes the challenges of preventing rancidity.
Encyclopedia article (1928–1936)
COLD CREAM (English: cold cream), ointments containing a significant amount of water and cooling (by design) the skin due to the evaporation of water (Robert). Numerous works by Unna and his followers have shown that the cooling effect depends not only on the percentage of water content but also on the type of fats and the method of preparing the cream: it must represent the finest possible emulsion of water in oil or oil in water. Most cold cream formulas achieve the emulsification of large quantities of water by adding borax or mucilaginous substances; for the same purpose, lanolin is introduced into the fatty part of the ointment. Due to the abundance of water, cold cream easily turns rancid. Wishing to prevent the rancidity of cold cream, the Russian Pharmacopoeia, and following it the Pharmacopoeia of the USSR, introduced the substitution of water with glycerin (Unguentum leniens), but such an ointment is essentially no longer a cold cream. A good, fairly stable cold cream can be obtained, for example, as a mixture of equal parts of lanolin, almond oil, and water (the amount of water can be increased further) with the addition of aromatic substances (rose oil).
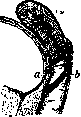
a - vesicovaginal fistula; b - ring of circularly excised tissue
it is necessary to perform releasing incisions, dissect scars, or separate them from the pelvic bones. Furthermore, colpocleisis was especially recommended for vesicovaginal fistulas complicated by ureteral fistulas, when the latter cannot be transplanted into the bladder. A necessary condition for the operation is the integrity of the urethra or the possibility of reconstructing it. Disadvantages of the operation: the vagina is shortened, hindering coitus; isolation of its upper section and the uterus makes conception and childbirth impossible [conception, however, is possible through the penetration of spermatozoa through the urethra (Kronig)]. In the vaginal reservoir above the septum, stagnation of urine occurs, along with its decomposition, the formation of calculi in clots of mucus and menstrual blood, and inflammatory irritations leading to cystitis, ascending pyelitis, and even potentially fatal outcomes; these disadvantages caused many to object to colpocleisis and even reject it entirely. Furthermore, colpocleisis did not satisfy surgeons as an unnatural operation that disfigures the anatomical relations of the vagina; therefore, there was always a tendency to replace it with other operations [for example, transvesical suturing of fistulas (Trendelenburg), transplantation of the ureters into the bladder, transplantation of them into the intestine (Maydl, Subbotin, Mirotvortsev, Gruzdev, Popov), or even extirpation of the kidney (Simon)]. Nevertheless, the dangers of colpocleisis are still not so great (patients can exist for decades even without cystitis), and transplantation of the ureters into the intestine does not guarantee against ascending infection. Therefore, colpocleisis cannot yet be completely struck from the list of gynecological operations, remaining for some cases an ultimum refugium.
Related articles
Mentioned in
Cite this page
“Cold Cream.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/cold-cream/