United States of America
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article provides general data on the United States of America from the 1930s, including population statistics, demographic trends, and healthcare organization. It details the structure of state and federal health departments, highlighting the challenges and unique aspects of the American healthcare system during that period.
Encyclopedia article (1928–1936)
UNITED STATES OF AMERICA. General data. Area - 7,702,000 km2, not including colonies. Population according to the 1930 census - 122,775,040 people, of which 62,137,080 men and 60,637,960 women. Population density in 1910 was 11.9 per 1 sq. mile, in 1920 - 13.7, in 1930 - 16. The extremely rapid growth of the US population occurred due to immigration from overseas countries, mainly from Europe. Table 1. Population movement in the USA. Years Number of inhabitants Including negroes Years Number of inhabitants Including negroes 1790 1800 1820 1840 1860 3,929,211 6,303,483 9,638,453 17,069,453 31,443,321 1,771,655 2,873,618 4,441,830 1880 1900 1920 1930 60,155,783 75,994,575 105,710,620 122,775,016 6,580,793 8,833,991 10,163,131 11,891,143 While negroes, who constituted the labor force, were at one time imported into the USA, the native Indians were dying out. Their number in 1792 was 846,000, in 1865 - only 294,574, in 1930 - 332,397 people. In the last 40 years, the urban population has grown particularly rapidly, and the ratio of urban to rural population has changed: in 1890, the urban population (in settlements with more than 2,000 inhabitants) was 22,298,359, and rural - 40,649,355, in 1930 - urban 68,954,823, and rural - 53,820,223. Table 2. Natural population movement in the USA. Years Birth rate per 1,000 pop. Death rate per 1,000 pop. average whites negroes average whites negroes 1920 1922 1924 1927 1928 1929 1930 23.7 22.3 22.4 20.6 19.8 18.9 18.9 23.5 22.2 22.2 20.2 19.5 18.6 18.6 27.0 26.0 27.4 25.0 22.2 21.3 21.5 13.7 11.8 11.7 12.0 11.9 11.9 11.3 12.6 11.4 11.2 10.8 11.1 11.3 10.8 18.0 15.7 17.7 17.3 17.8 16.9 15.2 Natural population movement. From Table 2, a decrease in birth rate and death rate in the USA is evident. The death rate and birth rate differ among the white and black populations of the USA. The birth rate among negroes is on average higher than among whites, but in many southern states it is lower than among whites. Population movement in the southern state of Tennessee in 1929 was as follows: birth rate per 1,000 inhabitants: whites - 20.8, negroes - 16.9; death rate per 1,000 inhabitants: whites - 10.7, negroes - 18.5; in 1930 - birth rate per 1,000 inhabitants: whites - 20.7, negroes - 16.8; death rate per 1,000 inhabitants: whites - 9.9 and negroes - 18.1, i.e., not only is the death rate among negroes almost twice as high as among whites, but the birth rate is also lower than among whites, and the negro birth rate is lower than their death rate. A genuine extinction of negroes is occurring under the conditions of the capitalist system in the technically most developed country in the world. The average life expectancy for the period 1919-1920 was 54.1 years for white men, and for negroes - 40.5 years, for white women - 56.4 years, for negro women - 42.3. The number of stillbirths is particularly high among negroes. Table 3. Stillbirth rate in the USA (per 100 live births). For all Years population Whites Negroes Years For all population Whites Negroes 1922 1923 1924 1925 3.9 3.9 3.9 3.8 3.6 3.8 3.8 3.5 7.3 7.2 7.6 7.3 1926 1927 1928 3.8 3.9 4.0 3.5 3.5 3.5 7.3 7.5 8.1 No improvement is observed in this area, rather there is even a deterioration. The causes, especially among negroes, lie in the harsh working conditions, lack of rest for pregnant women, and lack of medical assistance. Sanitary organization. In each state there is its own sanitary organization, the type of which varies depending on the state and which is completely independent of other states as well as of the federal government. In some states, the central sanitary organization has no legal authority over county organizations, and its role is purely advisory. In other states, the state central organization is quite strong, and local units - counties - depend more or less on it. The main trend in sanitary organization is the influence on local health authorities through subsidies, financial and personal assistance, which, while externally maintaining full autonomy, makes it possible to exert influence. The federal sanitary organization cooperates with local organizations by creating model medical institutions, model districts, councils, and developing standard plans for the most economically advantageous institutions. Under federal law, such assistance is possible only where the county or state assumes at least half of the expenses for these institutions. In 1929, such federal assistance existed in 21 states. In 1925, 16% of counties had permanent sanitary officials, and 91% of these local organizations received subsidies from the state or federal government. In 1932, out of 1000 counties, 616 were served by full-time sanitary officers. At present, such health departments exist in all states and in most cities. Usually, the health department of a state or large city consists of the following divisions (each state has its own distribution): 1. Administrative division with subdivisions of administration and health education. 2. Division of sanitary statistics, which usually includes registration of births and deaths, marriages, and sometimes divorces. 3. Division of infectious diseases with subdivisions of epidemiology, tuberculosis, and venereal diseases. 4. Division of maternal and child hygiene with subdivisions of child hygiene and school hygiene. 5. Division of social assistance nurses (Nursing Division). 6. Sanitary division. 7. Division of supervision over food products with subdivisions of milk supervision and supervision over food products and medicines. 8. Laboratory division. In some states, there are also divisions for mental diseases and hospitals, division of building supervision, and division of external relations. The health director in a state is appointed by the governor of the state, and in a city - by the mayor of the city. In most states and cities, at least half of the physicians - employees of the health department - are recruited from private practicing physicians (part-time officers), who devote only part of their time to this work and bring a private spirit into the institution and work. In some cities, even the health director himself is a private practicing physician. Almost all health departments of different states and cities are built on the same principle; and cities. A laboratory exists in almost every state and in every large city. It performs free analyses for poor patients sent by private physicians, and often sera and vaccines are prepared there. An engineering bureau is often included in another department. It is responsible for supervision over water sources, water analyses, sewage, garbage removal, and street cleaning. The functions of the Bureau of Maternal and Child Hygiene are purely propagandistic, as it usually has no authority to protect labor. Supervision over child labor lies with the labor department. The school hygiene division also often belongs to the public education department. In some states (very rarely), sanitary officials have the right to draw up reports and apply sanctions for violation of sanitary rules. Almost every state has its own code of sanitary laws, which are usually very similar. These laws are developed and proposed by local health authorities in agreement with local organizations of private practicing physicians and are submitted for approval to the state parliament. The activities of state and city health departments are mainly preventive. Local associations of private practicing physicians strictly ensure that these departments do not engage in therapeutic work. Even the establishment of dispensaries and sanatoriums and free treatment for indigent venereal disease patients are viewed with disapproval by physicians. It can be said that all development of healthcare in the USA occurs in a constant struggle with private physicians. Rural departments and departments of cities and states are often greatly assisted by wealthy private organizations created by large capitalists such as the Rockefeller Mission, Milbank Fund, Rosenwald Fund, etc. (see the budget chapter). The role of these philanthropic organizations in healthcare in the USA is enormous. The federal health department (United1 States Public Health Service) was established in 1798 and is part of the US Treasury. In 1902, the administration was renamed the Department of Health and Marine Hospital, and in 1912 it received its present name. Since then, its influence has constantly expanded, although its legal rights in the USA are insignificant. This department has no right to prescribe or order anything to the health departments in the states or cities, but due to the possibility of receiving financial support from it, and due to the high scientific competence of this body, states and cities are increasingly turning to it for support and advice. The main functions of this department include the organization of sanitary control over land and sea borders and supervision over sanitary relations and trade in sanitary and medical items between states, as well as providing medical assistance to federal employees.
It is divided into the following departments, located in Washington: Department of Scientific Research, headed by the National Institute of Health, one of the largest scientific institutions in the USA; Department of Domestic Quarantine; Department of Foreign Quarantine and Sanitary Supervision of Immigration; Department of Sanitary Statistics; Department of Marine Hospitals; Department of Venereal Diseases; Department of Mental Diseases; Department of Personnel and Accounting. The department is headed by a Surgeon General with several assistants. The entire territory of the USA is divided into 6 federal sanitary districts, and in each there is a representative of the federal department. In total, on the federal sanitary service, including the personnel of federal hospitals, on July 1, 1932, there were 10,844 employees. In 1924, in Havana, the USA signed an international sanitary convention with all American republics and created the Pan American Sanitary Bureau in Washington (see Conventions). A sanitary convention concerning quarantine and inspection of vessels has been drawn up and adopted for all of America. Starting from 1930, credits for health are being drastically cut everywhere. In 1932, most credits were cut by 33% and more. Infectious diseases. Their registration is mandatory in almost all states, usually according to a list developed by the federal Department of Health. Mortality from infectious diseases per 1,000 deaths. Table 1. Disease name 1930. Typhoid and paratyphoid Smallpox......... Measles......... Scarlet fever....... Whooping cough...... Diphtheria....... Influenza....... Dysentery....... Acute poliomyelitis... Epidemic encephalitis. Epidemic meningitis. Malaria.........
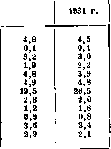
Smallpox. Vaccination is not mandatory and there is strong opposition to it from various charlatan and religious organizations like 'Christian Science', but in most states vaccination is given to all children in schools. From 1928 to 1931, severe epidemics of smallpox were observed, especially in the central eastern states, as a result of which mass vaccinations were carried out on the population, as a result of which the epidemics began to decline. Here are the figures for the last 5 years.
Table 5. Morbidity from smallpox in the USA. Years Number of cases Per 100,000 pop. 1928 1929 1930 1931 1932 39,398 42,282 48,907 30,232 11,168 34.8 39.7 Plague. Only imported cases occur, although infected rats are constantly found in California. In recent years all American ships are built rat-proof. In addition, regulations prescribe the deratization of ships with cyanide gas every 6 months. Diphtheria has decreased significantly in recent years. Mass vaccinations are widely conducted in schools and among preschool children. Malaria is especially prevalent in the southern states, on the coast of the Gulf of Mexico, and in the coastal areas of the Mississippi. In 1929, registration of malaria patients was mandatory in 35 states. In 12 southern states, the number of malaria patients was estimated at 1 million. Mortality from malaria in recent years was as follows: Table 6. Years Number of deaths Years Number of deaths 1926 1927 3,255 3,128 3,341 1928 1929 5,821 5,092 This amounts to 12.5 deaths per 100,000 pop. in malarious areas and 4.2 for the entire country. Morbidity from malaria was as follows: Table 7. Years Number of cases Years Number of cases 1921 1923 1925 1926 188,467 138,334 100,419 120,999 1927 1928 1929 1930 140,651 166,522 98,493 Trachoma is observed in almost all states, but the number of cases is insignificant. Entry into the USA for trachoma patients is prohibited. Foci of trachoma are concentrated in the mountainous regions of the southern states. In 1932, the number of patients was estimated at 17,000 (20 per 1,000 inhabitants) in these states. Tuberculosis. Mortality from tbc has been decreasing in recent years. Among Negroes, tuberculosis is the main cause of death. Their mortality from tbc exceeds that of whites by 2-3 times: Table 8. Mortality from tbc per 100,000 pop. Average Years Whites Negroes mortality Years Whites Negroes mortality 1925 97.3 239.6 1926 63.3 205.3 1927 86.6 207.7 1928 87.7 217.1 1929 99.4 217.1 1930 59.2 199.9 Mortality from tbc among Indians is very high. According to a 1927 survey in the Indian reservation in Oregon, 9.3% of all Indians suffer from tbc, of which 4.9% have pulmonary tuberculosis. Even higher mortality from tbc is found in American colonies: in Hawaii in 1907-11 it was 187 per 100,000. Thus, the apparent decrease in mortality from tbc among whites is in no way accompanied by improvement among the most exploited classes of the population. The fight against tbc is conducted mainly by private philanthropic institutions, as well as by states and the federal health department. In 1904, the National Tuberculosis Association was founded, which is a union of local philanthropic organizations. It subsidizes sanatoriums, conducts propaganda against tbc, and studies the issue scientifically. Almost all states now have state sanatoriums for tbc patients, which are managed by the local tuberculosis department of the health department. This same department conducts health education work and organizes dispensaries and consultations. Sanatoriums are all fee-based, but for the poor, beds are paid for by the state and county or city from which the patient came. Most states have special laws to combat tbc. In 1926, there were 600 hospitals and sanatoriums in the USA, of which 359 belonged to states, cities, the federal government, etc.; with a total of 70,000 beds. The number of dispensaries in 1926 was 600, the number of preventoriums was 24, and the number of forest schools was about 3,000. In 1926, there were 49 antituberculosis organizations in states and 1,154 in counties and cities. In 1925, there were 2,000 small points for combating tbc. In 1929, 7,115 social work sisters were employed in this field. Starting in 1930, credits for combating tuberculosis have been reduced everywhere, and many sanatoriums have been closed. In 1930, there were 50,179 beds in government hospitals for tuberculosis patients and 13,510 in private ones. Venereal diseases. Registration of venereal patients is mandatory in almost all states. In fact, it covers no more than 20% of white patients, mainly the poor, and Negroes: the poor and Negroes are treated in public institutions where treatment is free, not by private physicians, and their registration is incomparably more complete. Morbidity from venereal diseases in the USA is enormous. Table 9. Number of patients Number of patients Years with syphilis with gonorrhea Total 1921 171,231 161,354 332,585 1923 179,511 153,356 332,867 1925 212,633 172,959 385,592 1928 184,514 151,659 336,173 1929 195,569 166,544 352,113 1931-32 260,564 158,083 418,647 In addition, at least 7-8,000 cases of chancroid are registered each year. No tendency toward improvement is observed here; rather, there is deterioration. In 1928, the federal health department examined about 15 million people for syphilis. The proportion of syphilis patients, depending on the state, ranged from 0.55 to 21.29 per 1,000 pop., and gonorrhea patients from 0.29 to 8.04. On average, 11.6 people per 1,000 pop. suffer from venereal diseases. According to this survey, 1.2% of the entire US population is being treated for venereal diseases, i.e., about 1,500,000 patients, which is several times higher than official statistics. The percentage of venereal disease patients among Negroes is very high. Thus, in 1929 and 1930, the above survey found the following morbidity among them per 1,000 population in rural areas: state of Alabama, Macon county-350; state of Georgia, Glain county-269; state of Mississippi, Bolivar county-236; state of Tennessee, Tipton county-259. In Tennessee, according to the official report of the health department for 1929-31, 26% of all Negroes give a positive reaction to syphilis. Venereal morbidity is very high among merchant seamen. By law, they are treated free of charge at the expense of the federal health department. According to its data, 20% of all diseases in the fleet are venereal. Their treatment costs $5⅓ million per year. The fight is conducted by health departments and the Social Hygiene Association, organized on the same principle as the Tuberculosis Association. Health departments conduct the fight by organizing dispensaries, free distribution of medicines to private physicians, health education work, etc. In many US states, laws require physicians to report venereal patients who discontinued treatment before recovery, special quarantine for patients unwilling to be treated, etc. In 1926, there were reports of 416 public clinics, and in 1932 of 533 clinics that send data to the federal health department, but most clinics are private, provide no information, and only observe 'medical confidentiality' for the purpose of exploiting patients. Prostitution is prohibited everywhere in the USA, but in fact it is extremely widespread, and no fight against it is conducted except by the police. Since the crisis and unemployment, prostitution has spread very widely, and it is the main focus of venereal diseases. Cancer. Morbidity from cancer is continuously increasing; thus, in 1921 (per 100,000 pop.) it was 85.6, and in 1930-97.2. Mortality from cancer increased by 51.6% over 29 years. In 1927, the first state cancer clinic was established in Boston. Similar clinics are now being established in many cities (cancer hospital in Buffalo, etc.). Cancer is also studied at the Rockefeller Institute in New York. Most state laboratories have a cancer department for free pathological and anatomical examinations. Mental patients. There is a rapid increase in mental illnesses, outpacing even population growth. This is reflected in the growth of mental patients in hospitals. Table 10. Years Number of mental patients in hospitals Years Number of mental patients in hospitals 1910 159,098 1922 222,406 1928 264,226 1930 272,252 1932 280,251 291,077 At the conference on child protection held in 1930 at the White House, it was found that out of 45 million children in the USA, 5,630,000 suffer from physical or mental disorders. 1 million have speech disorders, 450,000 are mentally retarded children. Almost all hospitals for mental patients are state-owned. In 1929, there were 561 hospitals for mental and nervous patients in the USA with 356,457 beds, i.e., an average of 631 beds per hospital. Most hospitals are large in size. For example, near Washington there is a hospital for 8,000 mental patients. Compared to the usual luxury of American hospitals, mental hospitals seem very poor, extremely overcrowded, and look like prisons with bars on the windows. In the federal health department, there is a department of mental hygiene, which is responsible for organizing hospitals, combating drug addiction, providing psychiatric assistance in places of deprivation of liberty, and studying methods of combating mental illnesses. In 1929, a law was passed on the organization of central institutions for mental patients (Narcotic Farms), one of which has already been built in Lexington, Kentucky (1932). In 1928, 28 states had laws on the sterilization of mental patients, the mentally deficient, and 'habitual' criminals. In most states, there are special classes for mentally retarded children. Entry into the USA for the mentally deficient, idiots, congenital mental patients, alcoholics, tuberculosis patients, and persons with contagious diseases is prohibited. Alcoholism.
The United States of America has always been a country with high alcohol consumption. This was facilitated by the difficult situation of the working masses, the low cultural level of immigrants arriving from Europe, and the absence of cultural life. During the era of rapid capitalist development and a shortage of labor, alcoholism caused serious harm to industry by increasing the number of absences. Additionally, it reduced the productivity of labor among blacks, who were mercilessly exploited by plantation owners in the southern states. It was these states that first, before 1910, adopted laws for compulsory sobriety (Kansas, Mississippi, North Carolina, Oklahoma, and Tennessee, and from the northern states—North Dakota—against mountain miners—and Maine). During World War I, out of fear of disorder, alcoholic beverages were prohibited. In 1920, Congress, on the proposal of Volstead, adopted, as the 18th amendment to the US Constitution, a law for compulsory sobriety (Prohibition Law). In the first years after this law, a decrease in alcoholism and related diseases was observed. But gradually organized smuggling of alcohol developed, and large-scale capitalist and openly bandit exploitation of the population by smugglers (bootleggers), organized into trusts, grew. At the same time, farmers adapted to the new situation, producing moonshine whiskey and the like in huge quantities. At the end of 1932, under the influence of the crisis and the associated impoverishment of the masses, a decrease in tax revenues, as well as the obvious failure of the prohibition system, the repeal of compulsory sobriety was voted on by the Senate and came into force on December 5, 1933. Even during compulsory sobriety, mortality from alcoholism in the USA was significantly higher than in most European countries. Alcoholics constitute a very large percentage of patients in psychiatric hospitals in the USA. The highest mortality rate from alcohol among blacks (11.9 per 100,000 inhabitants), then among the Irish (11.5). Narcotics are a serious social scourge in the USA and show no tendency to decrease in recent years. In 1900, the number of narcotic addicts (morphinomaniacs and cocaine addicts) was estimated at 264,000, and in 1932, according to estimates by the Bureau of Narcotics of the Treasury Department—at 110,000, i.e., on average about 1 addict per 1,000 inhabitants. Narcotics are delivered in huge quantities by smugglers. Initially, the fight against narcotics was conducted by the states, but gradually it was centralized and passed to the federal government. Strict federal legislation has been introduced on the dispensing of narcotics in pharmacies. Hospital affairs. Hospitals in the USA are divided into government (belonging to states, the federal government, and cities), belonging to private philanthropic (non-profit) organizations, and private, commercial, created for the purpose of generating income. All three categories include most of the paid beds. Indigent patients are paid for by counties or states, philanthropic organizations, etc. In 1900, there were 2,070 hospitals in the USA, and since then the growth has been very rapid. In 1932, there were 6,613 hospitals with 974,115 beds. In addition, in 1928 there were 458 unregistered hospitals with 12,000 beds. Along with the growth in the number of hospitals, their enlargement also occurred. On average in 1928, there were 130 beds per hospital. On average in 1929, one bed per 240 inhabitants. In 1929, the property belonging to all hospitals was valued at $5 billion, or an average of $4,714 per bed, but while some private hospitals are distinguished by extraordinary luxury of equipment, far from the entire population is served by hospital care. According to the Committee on the Cost of Medical Care, the proportion of patients needing hospital care who were admitted to a hospital is as follows: annual income up to $1,200—percentage admitted to hospital 59.4; income $1,200-$2,000—52.4; income $2,000-$3,000—59.4; income $3,000-$5,000—63.1; income $5,000-$10,000—79.3; income over $10,000—98.0. In other words, the possibility of being admitted to a hospital is proportional to the patient's income, and patients with an income over $10,000 are served almost completely. The number of employees in all hospitals reached 647,658 in 1929. Due to the crisis, the occupancy rate is increasing in government hospitals. Table 11. Occupancy rate and distribution of hospitals in 1928. Category Number of hospitals Number of beds Percentage of beds occupied Federal hospitals 303 76,923 63.2 State hospitals 39,710 69.7 City hospitals 39,710 69.7 Philanthropic hospitals 92,980 80.9 Private hospitals 55,6 80.9 In 1928, out of 3,072 counties, 1,765 had public hospitals serving one or several counties. In the last 25 years, the proportion of state and municipal hospitals has been growing rapidly. By specialties, hospitals were distributed as follows (1929): Table 12. Specialty | Number of hospitals | Number of beds Skin and cancer..... For convalescents and 4,925 497 141 51 9 12,014 1,567 8,028 2,829 381,079 12,308 356,457 Ear, nose, throat, eyes . . . Nervous and psychiatric In prisons . . . 3,705 58,498 12,185 For chronic and incurable 2,424 4,488 Hospital care in the USA is distributed very unevenly, not approaching the population, and its class character is very pronounced. Almost all non-profit specialties are maintained by the states or the state. Pharmacy is entirely in the hands of private firms and pharmacists. Government organizations (states and federal department) limit themselves to distributing free of charge to private physicians arsphenamine and serums for treatment and vaccinations to indigent patients. Only some serums and vaccines in many states are produced by government laboratories. Pharmacies that sell exclusively pharmaceutical products are very few in the USA. Usually, a pharmacy is a kind of department store in which sweets, toys, books, tobacco, watches, cameras are sold, and there is a restaurant and bar. An increasing number of private pharmacies are also passing into the ownership of trusts. In 1929, there were 61,865 pharmacies in the USA, of which 57,812 were individual and 4,053 belonged to large firms. The number of pharmacists was about 75,000. In 1928, the turnover of these pharmacies amounted to $7,630,987,519. All serums and biological products produced by private firms for sale in the USA must be approved by the Federal Department of Health, but individual states may prohibit the sale of these products within their borders, even if they are approved by this department. For antitoxin serum, scarlatinal antitoxin, and other serums, this department has established standards that must be followed by private firms in the production of these products. This kind of central control over biological products, besides scientific grounds, also has economic ones. These products are now produced almost exclusively by large firms interested in concentrating the business in their hands and capturing the entire US market (Park, Davis & Co, etc.). It is easy for them to produce products meeting the standards in luxuriously equipped laboratories, while small firms cannot do this. Thus, government control contributes to the concentration of the pharmaceutical industry. In the USA there are 58 pharmaceutical schools belonging to the American Pharmaceutical Association of pharmaceutical colleges, and 28 not belonging to it. The course of study lasts 2-3 years, candidates must first complete college. The American Pharmacopoeia has been compiled and published by the Federal Department of Health, and is accepted in all states. Protection of motherhood and infancy. The main work in the field of protecting motherhood is carried out along the lines of hygienic-prophylactic and consists in organizing consultations for pregnant women, and mainly in organizing social assistance sisters to give advice to mothers in the field of women's and child hygiene. All these institutions, state or private-philanthropic, have no right to provide any therapeutic assistance. Working women have no opportunity to follow preventive advice. The health of the woman-mother is actually, with the exception of a few states, not protected by law. This explains the high maternal mortality in the USA, especially among black women. The average maternal mortality in the USA in recent years is approx. 6 per 1,000 births, exceeding the mortality of all European countries. This mortality has no tendency to decrease. The main cause of mortality is puerperal infection and abortion. The number of abortions has decreased recently due to the increasing spread of contraceptives. Since the crisis, maternal mortality in the USA has increased somewhat. Only in 4 states does a pregnant woman have the right to a 4-week leave after childbirth or a 2-week leave before, but this leave is not paid, and the employer is not obliged to take her back to work. In 1927, in 10 states there were laws on assistance to mothers and children dependent on others. Similar laws now exist in other states, but all this has the character of philanthropic assistance, not legislative protection. In 1927, according to official data, 1,034,000 children under one year and preschoolers were covered by private and state institutions for the protection of childhood and motherhood (out of 11,444,390 children under 5 in 1930). Infant mortality in the USA has decreased rapidly in recent years. Nevertheless, mortality among blacks remains very high. Table 13. Infant mortality (under 1 year) in the USA (per 1,000 births).
Years Among whites Among blacks total in cities in rural areas total in cities in rural areas I1II1II1I 72.5 73.2 73.5 66.8 68.8 70.0 60.6 64.0 59.6 74.7 77.3 74.5 68.7 69.4 70.9 61.0 64.6 70.1 68.7 72.9 64.7 67.2 69.4 60.2 63.4 108.5 110.0 117.4 112.9 110.8 111.8 100.1 107.2 102.4 128.2 127.0 188.1 126.7 125.0 127.2 113.1 121.3 99.8 101.7 106.0 104.9 100.5 100.8 92.2 93.5 About 50% of mortality occurs in the first month of life. At present, many states and counties give small loans to assist children and improve hygiene. In 44 states there are laws for assisting homeless children. In 1933 there were up to 400,000 such children who had left their parents because they had nothing to eat. In 1908, the first department of child hygiene was opened in the Department of Health in New York. In 1909, the first conference for the prevention of child mortality was convened. In 1912, the Federal Children Bureau was established. In March 1920, the National Child Health Council was formed. The first day nurseries were established in 1858. In 1919 there were only 63 nurseries in 40 cities and 18 states. Generally, nurseries develop very slowly and there is little interest in them. In 1928 there were only about 100 institutions of the nursery type. School hygiene is one of the best organized areas of health care in the USA. In almost every school, even in rural ones, wherever local health departments exist, periodic examinations of students are conducted, diphtheria vaccinations are given, teeth are examined and some dental treatment is applied. Special attention is paid to oral and dental hygiene, cleanliness, supervision of vision and hearing. For children suffering from mental disorders and for retarded children, specially equipped classes exist almost everywhere. In 1928 there were about 500 special psychiatric clinics for schoolchildren. Mandatory school examinations of children in 1930 existed in 42 states, but only in 16 states was school inspection mandatory in all counties. In 1929, 21 states had laws for the education of abnormal and disabled children. In 29 states there were 47 institutions with courses for parents on child psychology. In 95 cities there were 350 special classes for children suffering from visual disorders. The Institute of Nurses (School nurses) now exists in almost all states, and this yields the greatest results. In addition to official institutions and philanthropic nurses, there are nurses in large firms dealing in soap, children's food products (oatmeal), etc. These nurses, while promoting cleanliness, also promote the use of soap, oatmeal, milk, etc. The same kind of hygiene propaganda in schools and among parents is carried out by the powerful Child Health Association, organized on the same principle as the Tuberculosis Association. In 1912, the first five clinics for the treatment of throat tonsils were established in New York. In 1915 they had to be closed due to opposition from private physicians. In 1925-1926, in Tennessee, 139,500 schoolchildren were under the supervision of school medical inspection, and in 1929-30, already 526,000. In Pennsylvania in 1929-30, over 1,100,000 schoolchildren were covered by inspection. Starting from 1928, a number of states passed laws on mandatory physical education in schools, established free medical consultations at schools and, in case of emergency, free treatment. Municipal hygiene and sanitation. The development of sanitation in the USA relates mainly to the last 25 years and has proceeded at a rapid pace. The greatest successes have been achieved in the field of water supply, which is almost everywhere standardized according to norms developed by the American Public Health Association. Almost all cities and towns are supplied with water mains. Where wells are used, there is appropriate sanitary supervision by the city or state. In many cities, the use of wells is prohibited, as it is detrimental to the operation of the water supply system. Water consumption per capita in the USA is the highest in the world, averaging over 400 liters per day, and in many cities this norm is exceeded by almost 2 times. In 1925, the Federal Department of Health developed rules that drinking water must satisfy, and these rules were adopted as "interstate quarantine rules". Sewerage also exists in almost all cities, even the smallest. It also belongs either to the city or to private societies. Usually, sewage is not treated but is directly discharged into rivers or the sea, but in recent years many cities have created treatment systems with various methods. Usually, the sewerage system is unified for sewage and rainwater. Garbage disposal is less well organized. In the USA, with extremely cheap industrial products, the utilization of waste is not economically interesting, while the amount of garbage in the USA is enormous, and due to the enormous consumption of vegetables and fruits, there is a high percentage of organic waste. Recently, the system of incinerators has been widely applied, with garbage being burned completely, without any sorting, and the ash is dumped in landfills or into the sea. In recent years, the number of swimming pools in cities has been growing. In 1900 there were only 67, in 1918-3,212, in 1928-over 6,000. In 1915, only in one state was their use regulated, in 1928 already in 27 states. Control of food products is exemplary. Improvement in control was a direct result of the concentration of the food industry: large enterprises, which could easily organize strict control and produce high-quality products, displaced small enterprises from the market. Standardization of products was also a result of the industrial trust system. At present, both state and federal authorities have the right to enact laws and regulations concerning food products. Federal authority pertains to products imported from abroad or sent from one state to another, while state authority applies within the state. Supervision of compliance with federal regulations rests with the chemical division of the Department of Agriculture in Washington. Milk under federal law is divided into 3 categories: A, B, C. A-raw milk obtained from cows under the best conditions of hygiene and cleanliness, tested for tuberculosis reaction, and which can be consumed raw. B-pasteurized milk, which may come from cows not tested for tuberculosis, but milking must follow cleanliness rules. Finally C-pasteurized milk not falling into the first two categories. On bottles at sale, the category and date of milking must be indicated. In 1929, 375 cities in 20 states applied federal regulations. In 1927, in cities with a population over 10,000, 81.8% of all milk sold was pasteurized, and in 1931-87.5%. In the same cities, the percentage of milk from cows tested for tuberculosis or pasteurized rose from 99.1% in 1927 to 99.83% in 1931. The percentage of milk that was pasteurized and obtained from inspected cows rose from 50.8% in 1927 to 74.5% in 1931. Meat. Slaughter of livestock is carried out in private slaughterhouses, at large meat markets (thus, in Detroit in 1933 there were 38 slaughterhouses). Municipal slaughterhouses are almost nonexistent. During livestock slaughter, a city veterinarian is present at each slaughterhouse, immediately inspecting the carcass and internal organs after slaughter and applying a brand. Large canning factories also have slaughterhouses. Since 1891, federal meat inspection has been introduced everywhere. Due to strict inspection of livestock and meat, the quality of the latter is currently very high. In most states, special rules establish sanitary supervision over restaurants (usually by non-physicians), over stores selling food products, and over the health of employees in them. Sanitary educational work is carried out by: the Federal Department of Health, similar departments in states, a number of large public organizations (tuberculosis, social hygiene, etc.), numerous philanthropic funds (Rockefeller, Milbank, Commonwealth, etc.), insurance companies, private firms dealing in food products, sanitary supplies, etc. Sanitary propaganda is carried out everywhere on a huge scale. Its scale is directly opposite to the meager scale of actual sanitary measures in the field of labor protection and workers' health. The purpose of this propaganda is to try to improve hygiene in the country without touching the social system. In each health department, various departments (venereal, tuberculosis, child, infectious diseases) carry out sanitary educational work in their specialty. Propaganda is especially strong on the radio. Most departments regularly publish messages in the press, arrange lectures, print brochures, leaflets, posters. One of the favorite methods of sanitary propaganda in the USA is the organization of demonstration districts, where maximum health protection organizations are concentrated. Huge sums are allocated for the organization of such demonstration districts by philanthropic funds (mostly Rockefeller, several tens of millions of dollars a year).
This demonstration does so much for the wide dissemination of sap. enlightenment as for the advertising of these institutions. The results of sanitary-educational work in the USA even more brightly emphasize the relative barrenness of all this work under existing social conditions. Medical education in the USA is not standardized at all. Along with remarkably well-organized and equipped med. schools (Yale, Johns Hopkins, Harvard), there are also very poor ones. All med. schools can be divided into 2 categories: state or municipal and private, created from capital donated by wealthy philanthropists. The first exist on municipal or state subsidies, fees in them are quite low, but most med. schools are private, with very high fees - from 300 to 500 dollars per year, not counting expenses for textbooks, instruments, microscopes, etc. Thus a class selection of students is created. Scholarships in schools are few. Graduates of large private universities easily find both a position and an income, and a wealthy clientele. Graduates of cheap state universities find this difficult, and doctors from them immediately fall into the category of proletarian intellectuals. Some private med. schools and universities possess huge capital (Harvard - 117,204,250 dollars, Yale - 95,575,043, Johns Hopkins - over 30 million, Vanderbilt - 21 million, etc.). In total there are over 80 colleges and med. schools with capital of over 2 million each. The course usually lasts from 3 to 4 years, but to enter a med. school requires completing a two-year college course. In 1904, out of 160 med. schools, only 60 required diplomas for admission, while 100 did not ask for any documents. Since then, the number of schools has decreased significantly, teaching has become more serious and approaches the European level, while at the same time having a more practical character. Table 14. Number of med. schools and students in the USA. Number of schools Number of students Students per 100,000. 1892 12 930 17 728 18 200 18 840 19 662 16.5 21 597 1892 22 135 - Gradually, under pressure from the American Medical Association, almost all states introduced identical rules for admission. In 1924, in 42 states, including Alaska, candidates were required to have at least 4 years of secondary school and special preparation in college. At present, all schools are divided according to the nomenclature of the American Medical Association into two categories: A and B; 80% of them are affiliated with universities. Out of 80 schools, 74 are regular medical, 2 are homeopathic, 4 are various. In 1927, already 95.4% of students studied in med. schools of category A, whereas in 1913 only 65.4%. In 69 schools, candidates are required to have at least a two-year college course and a 4-year course in med. school with a minimum of 3,600 hours of instruction. In 10 schools, the course is five years, with the last year being completed as an intern. Students graduating from med. school must pass examinations before a special state commission to obtain the right to practice in the state. The diploma obtained is valid only in the state that issued it, but in recent years many states have concluded agreements among themselves on the validity of diplomas from schools of category A. In 1927, diplomas of this category were valid in 39 states. In the best med. schools - Yale, Vanderbilt, Harvard - the number of students does not exceed 250, and they accept no more than 50 people per year. In 1904, there were an average of 176 students per school, in 1919 - 152, in 1925 - 228. At some large med. schools (Harvard, Johns Hopkins), there are special schools of public health for hygienists, future sanitary officials. On average, these schools graduate from 80 to 100 hygienists per year. The number of women in med. schools is very small. Many med. schools do not accept women. Most schools do not accept Negro students. In the Southern states, there are separate med. schools for them (in Georgetown in Washington, in Philadelphia). In some schools, admission of Jews is restricted (Johns Hopkins University, the best in the USA). In addition to med. schools, there are many institutes and courses for the further education of doctors. In 1927, there were 35 institutes, and in 265 hospitals there were places for interns wishing to specialize. Most dental schools are now part of universities. Teaching in them has greatly improved in recent years. A dentist is required to have at least 2 years of secondary school and three years in university. In 1930, at 25 med. schools there were special schools for nurses with a 2-year course. Until 1875, no diploma was required to open a pharmacy, and the development of pharm. schools proceeded slowly. Since 1875, in most states a diploma is required from a pharmacist. In 1932, there were 60 pharm. schools, most of which are affiliated with universities. The course in them is usually two years. In 1928, there were 16 sanitary-tech. schools for training sanitary technicians and engineers. In 4 schools, the course lasted 5-6 years. Doctors, nurses and other medical personnel. The USA is the country in the world most saturated with medical professionals. The class struggle among doctors of different economic positions is very strong and, on the basis of common life in the USA, has led to an extreme lowering of the ethical level and commercialization of medicine. On the one hand, there are wealthy doctors with large practices, who graduated from famous universities, on the other hand, a huge proletarianized mass of doctors. The commercial nature of the medical profession, the absence of laws protecting the right to practice, the ignorance of the population supported by the church, have led to an incredible growth of medical quackery. In 1929, in the USA, 36,150 quacks (osteopaths, chiropractors, etc.) were engaged in medical practice. In 1913, there was one doctor per 640 inhabitants. In 1919, after the reform of med. schools, there was one doctor per 720 inhabitants, in 1924 - per 770, and in 1929 - per 800, i.e., the growth in the number of doctors lags behind population growth. In 1925, there were 147,010 doctors in total, in 1926 - 149,521, in 1929 - 152,203, in 1931 - 159,139 (of which about 22,000 were employed in institutions) and 63,334 dentists, in addition 335,000 diploma nurses. On average, from 7,000 to 8,000 doctor's diplomas are issued per year. The distribution of doctors in the country is uneven. In North Dakota, there is one doctor per 1,386 inhabitants, and in the District of Columbia - per 242, in California - per 455. Despite the apparent overproduction of doctors, their service to the population is completely inadequate. The crisis has only exacerbated this contradiction, as despite the increase in morbidity, patients less frequently can turn to doctors. Labor protection. In fact, if we do not consider the responsibility of employers for accidents, there is no serious labor protection in the USA, everything is left to the 'free' relations between workers and employers, and here the essence of American capitalism is best revealed. There is almost no federal legislation in this area, each state has its own. Federal laws aimed not at protecting the labor of workers in the USA, but only at regulating the influx of foreign workers into them. In early 1933, all states had laws limiting the working day, but usually they apply to the labor of women and children and hardly concern adult men. The limitation of working time in most states is considered contrary to the constitution, and in many cases the US Supreme Court has invalidated the laws of individual states in this area. Protection of female and child labor. Legislation in this area is extremely vague. In 1907, a bill was introduced into the US Senate prohibiting child labor in all states, but it did not pass. In 1916, the bill was introduced again, passed and came into force in 1917. But in 1918, this law was declared by the US Supreme Court to be contrary to the constitution and was repealed. In 1924, the US Congress voted for an amendment to the US Constitution giving Congress the power to regulate or prohibit in states the labor of children under 18 years of age. This amendment did not limit the rights of states, but repealed local laws contrary to this amendment. To come into force, it had to be ratified by 3/4 of the states. Until 1933, only 10 states ratified it, and those the least industrial. This amendment still has no force. In 1931, in only one state was child labor prohibited until the age of 16; in 2, the employment of children under 18 years of age in mines was prohibited; in 25 states, a medical certificate of health was required to employ children, etc. Thus, there is almost a complete absence of legislative labor protection, while there exists a carefully developed and applied system for protecting food products, medicines, water supply, etc. That is why the results of the health system in the USA by no means correspond to the material possibilities of this country. Insurance of workers and responsibility of employers. In the USA, there is none of the types of compulsory insurance for workers. This is opposed not only by the governments of all states, but even by the General Confederation of Labor, which unites the labor aristocracy. At present, there is no compulsory insurance against illness anywhere in the USA. Federal laws compulsorily insure all civilian employees of the federal government and the District of Columbia, sea captains and dock workers, as well as private workers in the federal district (Columbia).
Almost everywhere, laws on compensation do not apply to domestic workers, agricultural workers, temporary employees, and in many states, to enterprises with fewer than a legally specified number of workers. Almost everywhere, to receive compensation, it is required that the accident occurred 'during and because of work'; only in a few states 'during work,' regardless of cause. In some states, occupational diseases are also included. The vast majority of workers and employees insure themselves against accidents and against disease in private enterprises or mutual aid societies. If they stop paying premiums, the insurance automatically ceases, thus the unemployed are in fact not insured. Also not insured are children under 18 and elderly people over 55 and 60 (they are refused insurance), and women are usually not insured either. Although for each type of insurance there are usually special policies, in recent years combined policies have often been used. Insurance now usually covers disease, accidents, loss of ability to work, death from disease or accident, and all medical expenses. Now there is a strong tendency to examine workers before hiring them, which is interesting to the entrepreneur. Social insurance is completely absent. Opposition to social insurance comes from entrepreneurs, private insurance societies, labor unions, and doctors. They all seem to agree that social insurance is necessary, but 'do not want this operation to be carried out by the state,' as this would increase taxes and because the state has no right to interfere in relations between employers and workers. Health budget. In the USA there is no unified health budget, as each state has its own independent budget, as does the Federal Department of Health. The budgets of each state are also not unified, as in most states each county has its own independent local budget. Only occasionally does it include subsidies from the state. Each city also has separate health budgets. In 1923-24, the sum of health budgets of all states amounted to 12,158,886 dollars; in 1926, the budget of 48 states amounted to 25,549,000 dollars; in 1927, 27,824,963 dollars. The sum of all expenditures on health care, concentrated in various departments and counties, in 1928 amounted to 134,931,779 dollars. In 1923-24, the health budget of 72 cities with a population of over 100,000 inhabitants amounted to 20,979,717 dollars (an average of 47.1 cents per person). In the last two years (1931-32), most states have cut health budgets by 30% to 40%. The budget of the Federal Department of Health was: from July 1, 1926 to June 30, 1927 - 9,600,000 dollars; from July 1, 1931 to June 30, 1932 - 15,126,892.69 dollars. In 1932/33, this budget was also significantly cut. In recent years, the federal budget for maintaining hospitals has grown significantly, but the Federal Department must treat merchant seamen and war veterans free of charge. The most extensive material for studying health care costs in the USA is provided by the works of the Committee on the Costs of Medical Care. From 1928 to 1931, the Committee examined the budgets of 36,668 individuals. Here are the data of this survey: TABLE 15. Annual income size % of persons receiving no medical care 46.6 42.2 37.3 38.4 24.4 13.8 1200- 2000 DOLLARS........... 2000- 3000 » ........ 3000- 5000 » .......... 5000-10,000 » .......... In other words, the percentage of people unable to use doctors' services in the USA increases with decreasing annual income and reaches almost half for people with an income below 1,200 dollars per year. The class nature of medical care in the USA is vividly revealed in these data. According to the same committee's data, in 1929 the US population spent 3,656,000,000 dollars on all types of medical care, an average of 30 dollars per person per year. Health care expenditures are distributed as follows (in thousands of dollars): the total amount of expenditures is 3,656,000, of which 2,885,790 (79% of the total) are paid by the patients themselves, 509,500 (14%) by the government, 181,710 (5%) by philanthropic institutions, and 79,000 (2%) by industry. In percentage terms, these expenditures are distributed as follows: to private practicing physicians-29.8%, to hospitals (private and state)-23.4%, to dentists-12.2%, to all kinds of nurses-5.5%, to medical charlatans (legal)-3.4%, public health-3.3%, other types of expenses-4.2%.
Related articles
Mentioned in
Cite this page
“United States of America.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/united-states-of-america/