Intoxication
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Intoxication refers to poisoning by toxic substances, including minerals, artificial compounds, plant and animal toxins, and bacterial toxins. The article discusses various types of intoxication, their effects on the body, natural defense mechanisms, therapeutic approaches, and specific forms like childhood intoxication.
Encyclopedia article (1928–1936)
INTOXICATION (from Greek toxicon - poison), poisoning by poisons. The word toxin is used primarily in reference to poisons of bacterial and animal origin (snake venom, neurotoxin, etc.), but toxic substances in the broad sense also include many other substances that are the subject of toxicology. Thus, intoxication, understood in the broad sense, can be caused by various toxic substances: mineral (inorganic, such as arsenic, phosphorus, etc.), some artificially obtained organic compounds (sulfonal, chloral hydrate, etc.), plant poisons (first of all - alkaloids, then some of the glycosides, which include such cardiac poisons as strophanthus, digitalis, etc.), and animal poisons (see those mentioned above). Bacterial poisons should be singled out into a special group - toxins in the proper sense of the word - substances, although also of plant origin, but differing from pharmacological poisons by certain features: unknown chemical structure; usually a longer, than that of alkaloids, hidden, so-called incubation period of action; in some, however, special cases, special routes of spread through the body, such as the spread of tetanus poison along peripheral nerve trunks; presence of antigenic properties; closer connection with the organs that fix them and are sensitive to them (unlike alkaloids, they cannot be extracted by ordinary methods). The degree of affinity of the poison to vital organs and the reactions that occur between the poison and the cell protoplasm are of essential importance in the origin of I. In the first respect, it is sufficient to point to such factors as, for example, the insensitivity of turtles to tetanus toxin (whereby the latter, when introduced into the body of this animal, circulates freely in its juices for a long time without binding to tissues, in contrast to what is observed in such cases in animal species sensitive to the toxin), and on the different effect of the same toxin in rabbits depending on whether the poison is administered under the skin or directly into the brain (deviation of the action of the poison by less vital organs in the first case) (see also Affinity). In the second respect, the role of certain conditions in the origin of I. is revealed in the works of Overton and Meyer (Overtoil, H. Meyer) on the action of narcotic agents, which established that the so-called coefficient of distribution of the poison between the liquid in which it is dissolved and the lipoids of brain cells is of decisive importance. But between the accumulation of poison in various parts of the body and its specific effect on organs, there is still no unconditional dependence; the latter is generally unthinkable without the former, but the former does not always necessarily lead to the latter, i.e., the poison can accumulate in organs without manifesting its action (Straub). Natural factors counteracting I. in the body act in various ways: in some cases, toxic substances are converted into non-toxic compounds, in other cases they are broken down and excreted from the body. But some poisons, such as strychnine and digitalis, have the property of leaving the body very slowly, and then so-called cumulative action becomes possible. Therapeutically, detoxification is carried out by trying to bind and neutralize the poison with the appropriate antidote (e.g., diphtheria toxin - with antidiphtheritic antitoxic serum), or to promote its excretion from the body by giving emetics, laxatives, diaphoretics, and diuretics, or to reduce its concentration (washing with physiological solution in typhus). With prolonged use of poisons in many cases, habituation to them is possible ('morphinists', 'arsenic eaters'), the essence of which is not yet fully clear; most likely, this is a matter of cellular immunity, but in some cases, such as with respect to alcohol, there is reason to speak of enhanced breakdown of the poison.
G. Spersky. CHILDHOOD INTOXICATION (intoxicatio infantum, food poisoning), a term introduced by Finkelstein for a disease otherwise called dyspepsia toxica (adopted by all-union pediatric congresses in the USSR), toxicosis alimentaria (Czerny), gastroenterite choleriforme (French authors), cholera infantum (older authors). It is characterized, in addition to digestive disorders, by severe manifestations from the nervous and cardiovascular systems and a deep disturbance of metabolism. The term I. d., which has become widespread, is not, according to the latest views, fully corresponding to the essence of the disease and should be abandoned. Occurring most often in children of the first year of life, artificially or mixed-fed, this disease does not manifest itself as such immediately, but usually joins an already existing nutritional disorder - either a severe infectious (enteral or parenteral) one, or a mild dyspepsia; at the same time, there is a turn for the worse in the child's general condition, restlessness or, conversely, lethargy appears, the color of the skin, expression of the eyes, etc. change. Statistics. In statistical accounting, the group of acute digestive disorders is generally taken into account, and cases occurring with toxic phenomena (intoxications) are not singled out from the general mass; thus, it is impossible to give figures on the relative frequency of this symptom complex. Undoubtedly, however, the number of I. d. increases sharply in the summer, parallel to the increase in the number of acute digestive disorders: the hotter the summer, the more cases of I. d. The period of maximum number of cases of I. d. varies: in some years it falls in June-July, in others - August-September. But sometimes a maximum (albeit significantly lower than usual) was observed not in summer, but in spring or winter (data from Goebel for 1928). Mortality also fluctuates within wide limits, depending on age, nutrition, feeding method, severity of the toxic symptom complex, duration of illness before the start of treatment, complications, etc. According to the data of Marfan and Debre, mortality from I. d. is 68-70% (Bytch), and according to Medovikov - 51.1% (Shulgin). Early onset of treatment is of great importance: in Medovikov's clinic, mortality from I. d. in children admitted before the 4th day of the disease was 9%, and in those admitted later - 67.8%. With parenteral (mainly purulent) complications, mortality sometimes reaches 90-98%. Symptomatology. The most characteristic symptoms indicating the transition of ordinary diarrhea to a toxic form, the development of toxicosis, are rapid weight loss, development of collapse, change in consciousness, and a number of disorders from the central and autonomic nervous systems; at the same time, the gastrointestinal symptoms can be either very pronounced - severe vomiting, frequent watery stool (cholera-like type) - or weak, but then lethargy and drowsiness (soporose form) or meningeal phenomena (hydrocephaloid) come to the fore. The developed toxic dyspepsia is accompanied by an increase in temperature with a sharp drop below normal, although in atrophic children the temperature may not rise (see Infantile Atrophy). Weight catastrophically falls (by 200 or more g per day) depending on the loss of water through vomiting, diarrhea, breathing, etc. The child's skin becomes pale, grayish in color with a cyanotic tint, becomes dry, loses elasticity; a peculiar puffiness appears, and in particularly severe cases, sclerema rapidly develops - a peculiar hardening of the skin and subcutaneous tissue on the lower extremities, and when the child lies on his back - also on the back surface of the body. On the pale skin, the bright redness of the lips, and sometimes the soles, stands out especially; phenomena of dermographism appear. Breathing takes on a toxic, 'big' character: frequent and without pauses, with equal duration of inspiration and expiration (see figure). In some
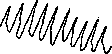
Types a and b - toxic breathing, subnormal. In some cases this type of breathing is so sharply expressed that it is compared to the breathing of a 'driven beast'. Cardiac activity suffers greatly: the pulse is rapid and weak; both heart sounds are very dull, especially the first, which often disappears completely; the second, despite its dullness, takes on a somewhat clapping character. The discrepancy between the heart sounds, which are sometimes almost inaudible, and the pulse, which despite its weakness can still be counted, is striking. The blood - shows signs of thickening (6 or more million erythrocytes) and infection of the body (leukocytosis, neutrophilia and a shift of the formula to the left); an increase in the refractometric index (W. McKim Marriott). From the chemical side in the blood: hyperglycemia (0.155% sugar instead of 0.081%; Fedynsky), a decrease in alkalinity, an increase in the amount of urea. The urine is sharply decreased in amount, contains protein, sugar, much indican, sometimes acetone and acetoacetic acid, and under the microscope - many cylinders of all kinds, leukocytes, and renal epithelium. Manifestations from the gastrointestinal tract may manifest as a very acute catarrh of the stomach and intestines with constant vomiting (sometimes colored dark) after food intake and independently of it, and with watery stools; the latter is by no means always present, but vomiting is a constant and most severe symptom, because thanks to it the child is in effect subjected to complete starvation and deprivation of fluids. The abdomen is sunken, and through the thin abdominal walls peristalsis is sometimes clearly noticeable. Analysis of the stomach and duodenal contents shows a significant decrease in enzymes, the presence of lactic and volatile fatty acids, and bacterial examination - a large amount of Bact. coli, Proteus, and Bac. perfringens. The child's muscles are either completely relaxed or often in a state of catalepsy and hypertonia, especially the occipital and shoulder girdle muscles, so that the child's position is peculiar, resembling the posture of a fencer or boxer. The face becomes immobile, all movements are slow. Consciousness is severely disturbed, gradually deteriorating as the disease progresses until complete coma sets in. Clouding of consciousness can be noted relatively early by a peculiar change in the expression of the eyes: in the developed disease, the 'frozen' gaze of the child's wide-open, rarely blinking eyes is directed somewhere into the distance, the pupils are sometimes dilated, or conversely, narrowed. All these symptoms, fluctuating in intensity and combining to varying degrees, still give a definite picture of toxicosis with deep damage to all organs and systems, but this large number of symptoms is not a help but an obstacle to clarifying the pathogenesis of the disease. Patho-anatomical changes in children who died from I. d. often do not correspond in severity to the disease. In some cases, acute catarrhal phenomena of the gastric mucosa and thin intestines with sero-hemorrhagic exudate are found in the digestive organs, sometimes with impregnation of the organ wall itself, with pinpoint or at least small hemorrhages in the mucosa, swelling of Peyer's patches and solitary follicles, with increased mucus secretion and desquamation of the epithelium. In other cases, changes in these organs are relatively insignificant, but the always existing parenchymal degeneration and fatty changes in the organs, especially in the liver (fatty liver), in the heart (flabbiness of the muscle), in the kidneys (nephrosis) and changes in the spleen (hyperplasia) suggest significant poisoning of the body or a septic process. In the lungs, distension is found, which corresponds to volumen pulmonum auctum, found clinically. From the side of the nervous system, no regular changes explaining the severe clinical symptoms are noted. Often, especially in prolonged cases, various purulent processes are found, most often purulent otitis, mastoiditis, as well as pyelitis and pneumonias. Etiology and pathogenesis. The close connection of I. d. with acute dyspepsia extends so far that many authors consider them only different stages of the same disease; for the transition of simple dyspepsia to toxic dyspepsia, the presence of certain conditions is required, which are acutely created in the body or are inherent in it in general. Therefore, etiological factors of toxic dyspepsia must be sought, also as in dyspepsia, in food defects or in infection, and it can be noted that the age of the child, constitutional data and nutritional status, as well as external conditions (care) play a major role as predisposing factors in terms of frequency, severity of the disease and speed of development of the toxic syndrome. The smaller the child, the worse his nutrition (hypotrophy), the sooner the picture of childhood I. can develop, all other conditions being equal. Two conditions should be noted that especially contribute to the development of toxicosis: 1) the presence of a constitutional anomaly - instability of water binding by cells (paratrophia hydrolabilis Finkelstein's); 2) the external condition - overheating of the body, which explains the appearance of a mass of diseases during summer heat - among children living in poor hygienic conditions, in narrow, stuffy, poorly ventilated basement and attic rooms. The role of food in the etiology of I. d. is undeniable, and the appearance of toxic symptoms is connected not only with poor quality (resp. infected) products or 53v improperly composed nutrition, but also with abnormal processes of food processing in the intestine and utilization of absorbed breakdown products (primary alimentary form). Proof of the food etiology of I. d. is the frequency of the latter in artificially fed children, as well as cases of rapid disappearance of I. d. when food is withheld from the child and a sufficient amount of water is introduced (detoxification therapy). In some cases, the primum movens has to be considered some or other, often insignificant infection, which may have already disappeared, however dyspepsia worsens, and toxic symptoms develop uncontrollably. Such forms have to be considered etiologically secondary-alimentary. And finally, in a large number of cases, I. d. develops in the child under the influence of an infectious process in the gastrointestinal tract (acute dyspepsias, typhoids, colitis) or outside it (pneumonias, otitis, pyelitis and other purulent processes), and the above-mentioned predisposing factors undoubtedly also play a major role here as factors lowering the body's resistance. Thus, there are many etiological moments, and they most often combine with each other in various combinations, so in each particular case it is always difficult to connect the appearance of I. d. with any one cause. The clinical picture and patho-anatomical changes undoubtedly indicate poisoning of the body with damage to the nervous and cardiovascular system, and more detailed study definitely says that the result of this toxic effect is a deep disturbance of metabolism, a huge 'metabolic catastrophe' (in the expression of Finkelstein). A similar picture is seen in adults with severe infections (especially cholera), as well as in diabetic or uremic coma. This disturbance of metabolism proceeds with a deep disorder of oxidative processes in the body, with phenomena of acute acidosis: an increase in the pH of blood, urine, and tissues, with an increase in the ammonia coefficient of urine, etc. The state of acidosis of the body explains many clinical data. The relatively frequent appearance of such a symptom complex is a feature of early childhood, and I. d. should therefore be considered as a specific reaction of the body, characterized by its signs, which always manifests itself in the same way and is always detected after certain changes arise in the body, whatever the causes (Finkelstein). In the question of the pathogenesis of I. d., there is no uniformity in the views of pediatricians. Some believe that the agent causing poisoning of the body is directly of infectious origin - a bacterial toxin (Adam, Bessau, Bossert, Hamburger, Medovikov, Moro, Plantenga), and they attribute the main role in this to the endotoxin of Bact. coli; others believe that the toxic effect on cells is produced by products of abnormal or incomplete breakdown of food in the small intestines; on the one hand, these substances damage the intestinal wall, so that the epithelium loses its selective ability to retain polypeptides and amines, and thus the intestinal barrier is disrupted, on the other hand, these unphysiological products of intermediate metabolism, entering the blood in large quantities, produce the disturbance of cell function that leads to a deep disturbance of metabolism. Apparently these toxins are of protein origin, and it is very likely that in most cases both agents participate in the pathogenesis of I. d., reinforcing each other, because in pure forms of infection, metabolism in cells is very quickly disturbed, and on the other hand - with disturbances of metabolism, the body's resistance to infection sharply decreases. This is especially evident in disturbances of water metabolism, when the cell loses the ability to retain water.
Such a state of exicosis, as has been proven experimentally (Bessau, Schiff, Beyer, and others), gives many symptoms that coincide with the clinical picture of I. d., and is also connected with acidosis. This exicosis, which occurs with large losses of water from vomiting, diarrhea, respiration, at elevated external temperature in combination with the action of toxic products penetrating from the intestine or from a parenteral inflammatory focus, affects the protoplasm in the sense of changing its dispersity, thereby causing a disturbance of cellular exchange; in this case, the cells of the liver suffer first, and the change in their function in turn leads to a disturbance of protein, carbohydrate, and salt metabolism. Disturbance of liver function also occurs through disruption of the so-called venous hepatic lock (see Liver), the result of which is the entry into the blood of unphysiological products of food decomposition, which are normally broken down in the liver (Heim). These same products, when the barrier is disrupted due to exicosis, penetrate the central nervous system and cause a series of cerebral symptoms, which we see in cases of developed I. d., along with signs of disturbance of the equilibrium of the autonomic system. In the infinitely complex picture of the disturbance of the activity of cells and organs in I. d., it is easy to mistake the effect for the cause, and vice versa; it is impossible to encompass all the interaction of pathological processes; even objective data from various authors contradict each other, therefore we still do not have an exact idea of the pathogenesis of the toxic condition for all cases. The diagnosis of the developed disease presents no difficulties. The mother's complaints and the child's external appearance in most cases make it possible to immediately make a diagnosis. It is much more difficult, and sometimes impossible, to connect the disease with this or that etiological factor, which has great practical importance. The diagnosis of the primary-alimentary form is established by the rapid disappearance of toxic symptoms when a starvation-water diet is prescribed, but in infectious cases, determining the initial moment and localization of the source of infection often presents an insoluble problem even in the presence of this or that inflammatory parenteral process, since the latter may be a complication of the main disease. -Prognosis and prevention. Alimentary I. d. always represents a severe disease for young children and is in the summer one of the main causes of high child mortality, especially of children with nutritional disorders and those on artificial feeding. The high child mortality rate in summer months exactly coincides with the frequency of I. d. cases and the height of the average summer temperature. Mortality in neglected cases reaches colossal figures - 80-90% (see above); if the first signs of I. d. can be noted, in most cases it is possible to prevent the development of severe symptoms, provided the basic suffering can be eliminated. The etiological factors of I. d. clearly indicate the path of prevention. Covering all young children with institutions for the protection of motherhood and infancy (consultations, milk kitchens, day nurseries, patronage, etc.) and the widespread dissemination of hygienic knowledge through sanitary education gives indisputable results in terms of preventing the appearance and reducing the number of severe cases of child I. d. Children of the poorest parents, artificially fed and suffering from chronic and acute nutritional disorders during hot weather require special attention. The maximum possible time for children to be in the open air without overheating them, careful observation of adequate fluid intake (at least 150 g per 1 kg of weight), and proper, preferably breast feeding under regular medical supervision are conditions that almost exclude cases of alimentary type I. d. -Therapy of child intoxication consists first of all in eliminating toxic phenomena (detoxication therapy), and then in helping the body to fight the cause of the disease (establishing proper nutrition, raising immunity, eliminating the purulent focus, etc.). To accomplish the first task, the following are prescribed: 1) complete deprivation of food, since in I. d. food is directly or indirectly a source of the formation of poisons that poison the body; fasting is prescribed for 12-24 hours, depending on the child's nutritional state; longer fasting, recommended by some authors (Monrad, Men'shikov), is permissible only when necessary in well-nourished children; 2) administration of fluids up to the body's full need to eliminate exicosis and to wash out toxic products as quickly as possible in the form of drinking frequent but very small portions (5-10 g every 10-15 minutes) or enemas (30-50 g 3-4 times a day), and since vomiting and diarrhea interfere with this, fluid must be administered subcutaneously, intraperitoneally, or intravenously. Often, constant administration of fluid drop by drop from a pipette into the mouth or by drip enema is of great benefit. Either pure water, or tea sweetened with saccharin, or Ringer's solution diluted with half water is administered into the mouth. For the purpose of retaining water in the body, other fluids containing salts are also recommended: Heim-John solution, vegetable soups (Mogo, Megu). These salt solutions should not be administered in more than 200 g per day (edema!)-For enemas, subcutaneous and other infusions, only Ringer's solution is used, also up to 200 g per day, with the addition of 10-15% glucose. It should be noted that administration of fluids per vias naturales gives better results than infusions. These two measures - fasting and administration of fluids - in non-neglected cases of I. d. of primary and secondary alimentary origin give a rapid effect: temperature falls, consciousness clears up, vomiting and diarrhea weaken, heart tones become clearer, the color of the skin, the look changes - in a word, there occurs incomplete or complete liberation of the body from poison. In cases where the basis of child intoxication is infection, especially parenteral, the results of such therapy are negligible. To restore normal nutrition, metabolism, and strength of the body, the introduction of food is necessary, the choice of which presents great difficulties, since the requirements made of it during this period of the disease are as varied as the views on the pathogenesis of I. d.; according to most authors, food should contain a small amount of fat (all agree on this), should not provide a basis for fermentation in the upper part of the intestine (i.e., should contain little sugar subject to fermentation and a significant amount of protein) and at the same time be hydrogenic. Although female milk does not meet these requirements in its chemical composition, due to its other valuable properties it is still in most cases the best food in the dietary treatment of I. d., but sometimes requires certain combinations for better influence on the course of the disease. The following correction is made: in severe cases with persistent vomiting, female milk is given in the first days skimmed, and along with it proteins are introduced in the form buttermilk (especially during the recovery period), its hydrogenic nature is increased by the joint administration of salt water and little fermenting carbohydrates (rice broth, solution of nutritive sugar). The method of food administration is of very great importance. In view of the significant decrease in food tolerance and decrease in enzymes, its amount should be very small at first and only gradually increased. The proposed scheme is as follows: in the first day after fasting, 10 or even 5 g is administered 10 times (every 2 hours) with an increase of 50-100 g on each subsequent day (see separate table), regardless of the child's condition and continuing vomiting and diarrhea, until the physiological minimum of food is reached, approximately 300 g pro die. After some pause (1-2 days), further increase in the amount of food proceeds in accordance with clinical data. The recovery of the body occurs slowly even in non-neglected cases; exceeding the limit of tolerance even with female milk (nursing!) threatens a life-threatening relapse. When female milk is not available, acid mixtures with reduced fat content (buttermilk, protein milk, skimmed milk with lactic acid, etc.) and sugar (up to 1-3% addition) are used; the latter is replaced by the addition of broth or flour. In terms of quantity, these mixtures are given according to the same scheme as breast milk (up to 100 g per 1 kg of weight); further increase in quantity and change in quality of food is adjusted according to the child's condition, his weight, temperature, stool, cardiovascular phenomena, etc. A number of other authors propose other methods of feeding in the first days of treatment of I. d., mainly with the elimination of protein from the diet: whey with broth (Czerny), with 15% nutritive sugar (Schiff), thick rice broth (Bessau), almond milk with whey (Moll), vegetable soups, etc., with a gradual transition to full-fledged food.
The difficulty in prescribing nutrition lies in the need, on one hand, to take into account the patient's ability at a given moment to assimilate the individual components of food (for which we essentially have no objective data) with a sharply lowered threshold of tolerance for it, and on the other hand, to avoid prolonged fasting, which in turn lowers immunity and impairs metabolism due to autolysis of cells. Along with fasting, the administration of water and diet therapy, the child requires the most attentive care of the skin (pyoderma), eyes (danger of xerophthalmia and subsequent keratitis), oral cavity (development of thrush, which interferes with food intake), etc. Baths are necessary: hot baths - when there is a tendency to collapse, cool baths - when the ambient temperature is high; wraps, constant ventilation of the room, in addition to other medical measures. A patient with I. d. requires so much attention that in institutions one nurse cannot care for more than two children suffering from childhood intoxication. Therapeutic measures consist of symptomatic assistance: washing the stomach and intestines, administering laxatives are suitable only at the beginning of the disease; disinfecting and binding agents for the intestines are useless; cardiac medications are used as necessary to buy time until the child's nutrition is somewhat established; caffeine (preferably subcutaneously), digalen, and adrenaline are given; camphor is not particularly recommended by most authors. With strong excitement in the first period of the disease - Veronal and Luminal (not opiates!). Enzyme therapy in the form of pepsin and hydrochloric acid, pancreatin, takadiastase - if it is useful, it is in the reparative period; insulin did not give the expected results. Transfusion of 200 g of blood (Powers) and intramuscular injection of citrated blood are also recommended. Serotherapy in the form of coli-lysosomal serum gave encouraging results to some authors.
Related articles
Mentioned in
Cite this page
“Intoxication.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/intoxication/