Lochia
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Lochia refers to the postpartum vaginal discharge originating from the uterine cavity during its involution. This historical article describes the normal progression of lochia (rubra, serosa, and alba), its cellular composition, and the clinical significance of its changes, including bacterial colonization and delayed uterine involution.
Encyclopedia article (1928–1936)
LOCHIA (from the Greek lochios—relating to childbirth), postpartum discharge from the uterine cavity associated with its reverse involution after childbirth. The processes of regeneration of the uterine mucosa in postpartum women show a significant similarity to the healing of wounds. The latter, as is well known, are accompanied by the discharge of a wound secretion from the wound surface, which in the postpartum period is called lochia. Depending on the duration of the postpartum period, lochia has a different color and character. In the first 2–3 days after childbirth, it has a bloody character (lochia rubra, or cruenta); at this time, under the microscope, erythrocytes prevail among the morphological components in the lochia, which seep from the vessels of the decidua and the placental site (Figure 1). From the 3rd, 4th, and sometimes on the fifth day, the lochia resembles blood serum and is called lochia serosa; microscopic examination reveals that the content of erythrocytes in it is significantly reduced, with leukocytes coming to the forefront among the morphological components, joined on the fifth day by shed shreds of the decidua and epithelial cells (Figure 2). From the end of the first week of the postpartum period, a more abundant admixture of mucus is noticed in the lochia, which partly originates from the cervix; erythrocytes largely disappear, and the microscope reveals only leukocytes, shreds of decidua (up to the 12th day), and detached epithelial cells
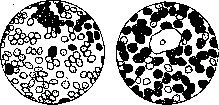
Figure 1.
Figure 2. of the genital tract. The lochia at this time takes the form of a grayish-white, opaque liquid and is called lochia alba. With the complete restoration of the endometrium during the third week after childbirth, the postpartum discharge under completely normal conditions ceases, and in the last days before this, it consists almost exclusively of vitreous mucus. The total amount of lochia discharged by a healthy postpartum woman reaches 1–1.5 kg in the first eight days of the postpartum period. Its reaction is alkaline or neutral. The odor depends on the quantity of pathogenic microbes. Recently, the question of the microbial content in lochia has remained unresolved. At one time, it was assumed that lochia taken from the uterine cavity of healthy postpartum women is free of bacteria, but if taken from the cervix and vagina, a mass of microbes can be found in them. Döderlein established that the germs present in the vulva and vagina in the first days of the postpartum period do not usually penetrate beyond the internal os. Therefore, uterine lochia under normal conditions is free of germs, odorless, or has the musty smell of aseptic secretions. In the cervical canal and vagina, the number of germs (cocci and bacilli of various types) can become so large that the lochia begins to show signs of decomposition, and if it is abundant and stagnates in the fornices, it acquires a strongly putrid odor, which does not yet indicate illness in the postpartum woman if temperature and pain are absent. However, more recent studies show that the uterine cavity is apparently free of bacteria only for the first 3 days; from the 4th day, microbes penetrate there as well, without manifesting clinically in the form of any painful process. Disorders of mucosal regeneration and uterine involution change the character and quantity of lochia. With insufficient retraction, retention of placental remnants, or any damage to the newly formed mucosa, the discharge remains bloody longer than the time indicated above. A high content of pus in the lochia indicates inflammatory processes in the uterine mucosa. Delayed regeneration of the uterine mucosa makes the discharge from the uterus more prolonged; the lochia is prolonged up to 4–6 weeks, and often turns into chronic fluor albus if inflammatory diseases of the endometrium develop as a result of childbirth. Many believe that prolonged bloody discharge in the postpartum period is a common occurrence. However, it should be pointed out that prolonged bloody lochia definitely indicates poor postpartum involution of the uterus. Sometimes on the 21st–28th day, a secondary appearance of bloody discharge can be observed. Postpartum women should be warned about this, as this phenomenon is the so-called "small menstruation," or the first return of the uterus to its menstrual function.
D. Ginodman. LOCHIOMETRA, a temporary accumulation of postpartum discharges in the uterus due to their obstructed outflow. By the majority of authors, lochiometra is classified as a special form of puerperal wound intoxication (resorption fever, sapremia) with a characteristic clinical picture. Some, however, explain lochiometra by insufficient involution of the uterus (Spiegelberg, Runge, and others) or view it as a special form of benign endometritis (Pobedinsky). Bublichenko classifies lochiometra as resorption fever and draws a line between it and resorption fever in the proper sense of the word. According to his description, lochiometra represents a deviation from the norm associated with the retention of liquid postpartum discharges in the uterus without the presence of any other changes in the uterine cavity, whereas in resorption fever in the proper sense of the word, there is decomposition of the remnants of decidual tissue, and the absorption of decay products occurs even in the absence of discharge retention. Sitsinsky considers lochiometra an independent form of the sapremic process with a clearly defined clinical picture, associates it with insufficient involution of the uterus, and classifies it among bacterial postpartum diseases. Taking into account that the illness of the organism in lochiometra is caused by the absorption of decay products of the contents of the puerperal uterus, this deviation from the norm must, of course, be classified as wound intoxication. An increase in temperature can also occur from the absorption of dying tissue retained in the uterine cavity without putrid decomposition in it, similar to the fever in bruises, tissue crushing, bone fractures, etc., and therefore non-bacterial lochiometra is also conceivable (noted in isolated cases by Bublichenko); but it must be classified as an exceptionally rare phenomenon. Recent studies confirm that by the fourth day of the puerperal period, the uterus is flooded with microbes penetrating into its cavity from the vagina (Leser and others), among which there is no shortage of saprophytic infection. Therefore, in lochiometra, absorption of material that has undergone decomposition under the influence of saprophytic infection usually occurs, which is why this disease must be classified under the group of bacterial puerperal processes. The origin of lochiometra is twofold. First of all, it can arise with a relatively normal state of the uterine musculature in connection with the mechanical influence of overfilled neighboring organs and increased intra-abdominal pressure; relaxed uterine musculature due to overstretching in multiple pregnancy, hydramnios, etc., is an especially favorable condition for the development of lochiometra under the mechanical influence noted above. On the other hand, lochiometra can occur as a temporary complication in insufficient involution of the uterus and blockage of the cervical canal by blood clots, shreds of decidual tissue, remnants of fetal membranes, and placenta. The latter form of lochiometra is an accidental complication of another primary process in the uterus, does not have a definite clinical picture, but only modifies the course of the primary process, and therefore cannot be classified among the typical forms of lochiometra. On this basis, only typical lochiometra, uncomplicated by any disease of the uterine cavity, should be described, since only in this case does it possess a definite, clearly outlined clinical picture. In the normal course of the postpartum period, the uterus in the first few days has a widely open cervical canal, and the postpartum discharges meet no obstacle to their outflow. By the end of the first week after childbirth, the most constricted part along the birth canal is the region of the internal os, which at this time barely admits a finger. Usually by this time, the uterus has a pronounced anteflexion, and therefore, in the presence of pressure from neighboring organs, under the influence of straining, and sometimes simply from a prolonged sitting position or first standing up in bed, the lumen of the canal at the site of the flexion is narrowed to such an extent that even liquid lochial secretion finds no outlet and accumulates in the uterine cavity. In those cases where the uterus has decreased to such an extent that its fundus descends to the level of the pelvic inlet, retroflexion of the uterus, resulting from prolonged lying on the back and overfilling of the urinary bladder, can also serve as the cause of the accumulation of discharges in the uterine cavity. The dying blood tissue is a good nutrient medium for saprophytes that have penetrated into the uterine cavity; the accumulated blood undergoes putrid decomposition, and the decay products, under the influence of increased pressure in the uterus, easily enter the general blood and lymph circulation. Along with the tissue decay products, toxins produced by microbes, and in some cases the microbes themselves (passive bacteremia), enter the puerperal woman's body; but the latter, being saprophytes, quickly perish, as they cannot develop on living tissue. Thus, the disease is caused by the absorption of the uterine contents solely under the influence of increased pressure within it; in the absence of retention of postpartum discharges, the presence of saprophytic infection in the uterus does not lead to disease, since the toxins secreted by saprophytes are carried outward along with the lochial secretion. Developing under the influence of accidental factors, typical lochiometra can quickly disappear; for this, a change in the position of the puerperal woman or a change in the state of neighboring organs is sometimes sufficient; the uterus then straightens, the os dilates, and the contents of the uterus are discharged into the vagina. But the accumulation of discharges in the uterus may be retained for a day or more. In view of the absence of other changes in the uterine cavity, the disease is either limited to a single retention and complete restoration of health upon emptying the uterus of its contents, or the retention of discharges is repeated several times (2–3 times), but as a rule, complete recovery always occurs without any complications. Lochiometra, according to Sitsinsky, occurs in 1–2% of all births, and in relation to all bacterial puerperal diseases, in 17.4% of cases. In connection with the noted features of typical lochiometra, a very characteristic clinical picture is observed. Most often by the end of the first week, less frequently later, a sudden retention of postpartum discharges is noted. Malaise, chills, or a pronounced rigor with a high rise in temperature (up to 39–40°C) appear. The pulse quickens slightly, but never corresponds to the height of the temperature curve; it remains full and regular. The tongue is moist and usually clean. The general appearance of the patient and the expression of her eyes do not bear the character of a severe illness. The attack lasts from several hours to 1–2 days and ends immediately after the discharge from the genital tract of a significant amount of mucous, brownish-watery discharge with a putrid odor; the temperature drops, and its fall is usually accompanied by profuse sweat. There are usually no complaints from the patient regarding the genital sphere, though sometimes mild labor-like pains are noted. The uterus during the attack is painless or only sensitive to the touch, enlarged, spherical in shape, of a soft-elastic consistency, and reacts weakly or not at all to stimulation during massage. The region of the adnexa and ligamentous apparatus is painless. The diagnosis of typical lochiometra is established on the basis of the sudden cessation of discharges, characteristic palpation findings, the onset of the attack at the end of the 1st or beginning of the 2nd week, and a sharp rise in temperature with a relatively satisfactory general condition of the patient and a good pulse. With a prolonged attack, the temperature can show large fluctuations. Although similar spikes in temperature are observed in other forms of resorption fever and pure infectious processes complicated by retention of discharges in the uterine cavity, there these spikes will be against the background of a temperature curve corresponding to the primary disease. Especially characteristic of typical lochiometra is the drop in temperature to normal in connection with the discharge of the lochial secretion retained in the uterus. Prophylaxis of lochiometra is reduced to: 1) maintaining good uterine contraction in the first days of the postpartum period by applying cold to the lower abdomen if necessary and prescribing ergot preparations internally, 2) timely emptying of the bladder and intestines, and 3) conducting early movement in bed. These movements not only improve blood circulation but, by exercising the abdominal wall, have a beneficial effect on the function of the bladder and intestines and promote the timely discharge of lochial secretion from the uterus (see Postpartum Period, physiology). Treatment must first of all be directed toward eliminating the factor that contributed to the anteflexion or retroflexion of the uterus; these measures include emptying neighboring organs and changing the position of the puerperal woman (putting her to bed if the retention of lochia is due to prolonged sitting or movement, placing her on her side or abdomen in case of lateral or posterior displacement of the uterus). If this is insufficient, the position of the uterus is changed manually through the abdominal wall, and if necessary, with the help of a bimanual examination.
If this fails, the uterus is emptied of its contents by introducing a curved dressing forceps or clamp through the cervical canal, followed by spreading the jaws. In cases of a highly pronounced putrid character of the discharge, some authors recommend douching the uterus with disinfectant solutions using an ordinary vaginal nozzle introduced into the cervix between the jaws of the spread forceps, or by means of a Fritsch-Bozeman return-flow catheter. (However, this catheter is not used by some obstetric schools due to the fear of clogging its outflow channel and a possible increase in pressure within the uterine cavity; but this usually does not occur if a catheter approximately the thickness of an index finger is used.) To prevent recurrence of the attacks, it is recommended to carefully carry out those measures indicated in the prevention of lochiometra.
P. Zanchenko. Bibliography—see bibliography for the article Lochia.
Related articles
Mentioned in
Cite this page
“Lochia.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/lochia/