Psittacosis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia describes psittacosis, an acute infectious disease transmitted to humans by parrots. It details the historical search for the causative agent, the epidemiology of the disease, and the patterns of outbreaks observed in Europe and America during the early 20th century.
Encyclopedia article (1928–1936)
PSITTACOSIS, psittacosis (from Greek psittacos—parrot), "parrot disease," an acute infectious disease transmitted to humans by parrots and manifesting in the form of epidemic outbreaks among persons who have been in contact with sick parrots. Etiology. During the Paris epidemic of 1892, Nocard discovered in the bone marrow of parrots that had died of psittacosis a special microbe from the paratyphoid bacillus group, which he considered the causative agent of the disease, but this microbe was not found in subsequent outbreaks nor in the epidemic of 1929–30. During the epidemic in Zülpich in 1909, Bachem, Selter, and Finkler isolated a streptococcus from all patients and attributed a prominent role in psittacosis to it. Even before the 1929–30 epidemic, Nocard's bacillus was identified with the paratyphoid bacillus Aertrycke (Bact. Aertrycke—Bact. breslaviense), which causes diseases that are completely unlike psittacosis. In the 1929–30 epidemic, studies primarily by English, American, and German authors showed that the causative agent of psittacosis is a filterable virus. This virus is found in the blood, liver, spleen, intestines, and feces of sick birds. By injecting parrots with a filtrate from an emulsion obtained by grinding the liver, spleen, and other organs of people who died of psittacosis, it was possible to reproduce the full clinical picture of the disease in the birds. Krumwiede even managed to reproduce the infection in mice, but failed to inoculate the disease into chickens and other domestic animals. Reinecke isolated a special bacillus from the paratyphoid group from patients, but it was not identical to Nocard's bacillus. Other researchers also found various microbes, the role of which has not yet been established with certainty. Therefore, for the time being, based on the data of most authors, it can be considered that the most probable causative agent of psittacosis is a filterable virus, transmitted by sick parrots to humans, but which can also be transmitted from human to human. The role of ectoparasites as intermediate transmitters of the disease has also not been established. Epidemiology. The main carriers of the psittacosis virus are Brazilian green parrots (Chrysotis amazonica, Figure 1). Other species of parrots are apparently not its primary sources, but become infected from bird dealers when placed in the same cages as the Brazilian ones. It is possible that other birds and animals can also contract psittacosis and spread the contagion. In a parrot, the incubation period of the disease lasts from several days to several weeks. The disease begins with the parrot becoming sleepy, lethargic, and refusing food. Its feathers become ruffled and fall out rapidly, and a severe and extremely foul-smelling diarrhea begins. The excrement of a sick parrot contains the psittacosis virus and is extremely contagious. The parrot dies on the 4th–5th day.

Figure 1. Green Brazilian parrot.
with symptoms of emaciation, extreme shortness of breath, convulsions, and often blindness before death. Sometimes infected parrots remain healthy in appearance, but even in these cases of latent carriage, they can be a source of infection for those around them. Infection from a parrot usually occurs during cage cleaning, when feeding the parrot by mouth, or upon contact with its carcass, feathers, etc. Elkeles (1930) emphasizes the danger of contracting psittacosis upon the slightest contact with a sick parrot or its cage. The disease apparently exists in the form of an epizootic in South America; batches of captured parrots intended for export to other countries become infected with it, and these batches, in turn, infect other birds and humans on the way or at the place of arrival. In Europe, imported epidemics usually subside fairly quickly, although it is certain that the virus still persists for some time among birds at bird dealers, which explains the appearance of small outbreaks long after the end of an epidemic. The greatest danger in ordinary times is posed by newly imported parrots. Infection almost always occurs from parrot to human, but during the 1929–30 epidemic, it was established with certainty that the disease can also be transmitted from human to human, although the danger of such infection is far from as great as previously thought. Parrots are usually kept by petty European and American bourgeois. This explains why psittacosis, during all the described epidemics, primarily affected these population groups. In addition, psittacosis affects sailors who bring parrots with them for sale, and bird dealers. It is interesting that among the latter, cases of severe psittacosis are extremely rare, which is attributed by some authors to the existence of a kind of occupational immunity among dealers: psittacosis in them runs a mild course, goes unnoticed, and confers immunity. The center of the parrot trade, as well as the animal trade in general, is in Hamburg. In the countries of South and Central America, in Australia, and in Equatorial Africa, parrots are found in almost every home. Parrots are imported into Europe and North America from South America, Australia, and Equatorial Africa. According to data from Bruno Heymann and Neunzig, about 10,000 Brazilian parrots, 3,000 to 4,000 African grey parrots, and at least 6,000–7,000 smuggled by sailors are imported into Hamburg per year. According to one large Berlin dealer, every year (this refers to the post-war period) 5,000 to 6,000 South African parrots, 20,000 to 30,000 Brazilian, 8,000 to 10,000 Australian, etc., are brought into Berlin, and a total of 40,000 to 50,000 parrots are sold in Berlin alone per year. But besides that, a whole stream of parrots flows into Europe through other major ports—Bremen, Marseille, Bordeaux, Lisbon, London, etc. The same stream flows into New York, Boston, and San Francisco. This stream does not yet reach the USSR, but individual parrots can be imported into the USSR even now; Epidemics of Psittacosis. Psittacosis has been known in Europe since 1876. Its first description was given by Jürgensen, who considered it an atypical pneumonia of animal origin. In 1879, there was an outbreak of psittacosis in Paris and in the same year in Switzerland. Similar outbreaks have been registered in Europe many times since then: in 1882 in Bonn (Germany), in 1886 in Leipzig, etc. The largest outbreak was observed in Paris in 1892—51 cases, 16 of which were fatal. From 1892 to 1898, there were a number of small outbreaks in Paris. During the same period, psittacosis was also observed in other European cities: in 1898 in Stettin and Berlin, in 1895 in Florence, Prato, and Genoa, in 1904 in Brazil and New Hampshire, in 1908 in Hanover. In 1909, an epidemic broke out in Zülpich near Cologne. In 1914 and 1924,
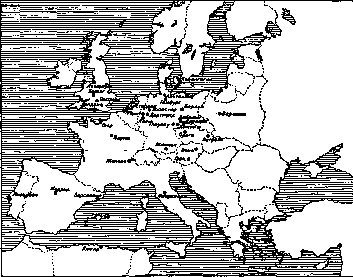
Figure 2. 1930. Geographical distribution of psittacosis in the 1929– epidemic (black circles indicate cities where cases were observed). isolated cases were noted in England and in 1928 in the USA. All illnesses were essentially single, isolated in the form of household or family outbreaks and were limited to the circle of persons who were in direct or indirect contact with parrots recently imported from South America. Only in some cases were parrots from other countries the cause of the disease, but even these parrots could have caught the disease while being at a bird dealer's next to Brazilian ones. In total, from 1876 to 1929, Bruno Heymann counted 164 cases of psittacosis, 54 of which were fatal. In 1929–30, the largest psittacosis epidemic was observed in Europe (Fig. 2) and America. The number of registered patients during this epidemic exceeded 800. Their number was undoubtedly significantly higher, since the disease was not subject to mandatory reporting, and furthermore, especially at the beginning of the epidemic, most cases were diagnosed as atypical pneumonia, typhoid fever, or influenza. This epidemic aroused great interest in psittacosis. All illnesses were observed exclusively in persons who had purchased parrots from newly imported batches. The illnesses occurred in the form of small family or household outbreaks, without any tendency to affect broad strata of the population, which is an indicator of the weak contagiousness of psittacosis from human to human.
A. Rubakin. Pathological anatomy. The most significant changes observed during autopsies of individuals who died from psittacosis are concentrated in the lungs. In 100% of cases, there is a development of pneumonic foci, and the character of the pneumonia changes depending on the duration of the disease. Most often, there is a development of lobular catarrhal-fibrinous pneumonia, sometimes progressing to lobar; however, only in those who died early does this pneumonia remain catarrhal-fibrinous with a peculiar reddish-violet hue. Very quickly thereafter, foci of necrosis of the lung tissue develop with hemorrhages within them, and the pneumonia becomes abscessing (see Influenza, pathological anatomy). Microscopically, the exudate in the alveoli consists of fibrin, desquamated epithelium, erythrocytes, and leukocytes; in late stages, plasma cells sometimes appear. Regarding the upper respiratory tract, a catarrhal state is observed very early, and this catarrh, initially serous, can take on a fibrinous or fibrinous-purulent character. Particularly significant changes are observed in the small bronchi. Phenomena of bronchitis and bronchiolitis develop very early, and the usual catarrhal process takes on a purulent character; the walls of the small bronchi are destroyed, the integrity of the elastic framework is disrupted, and bronchiectasis develops. The destruction of the bronchial wall most often depends precisely on its purulent melting, but sometimes primary necrosis also occurs, and then the process proceeds especially acutely. Complications developing from pneumonia, just like the pneumonia itself, do not present any special forms peculiar only to psittacosis. Pleurisy, empyema, mediastinitis, abscesses, and sometimes gangrene of the lung arise. Very often, phenomena of carnification and sclerosis of the lung develop rapidly. Residual changes after psittacosis pneumonia have been little studied, but apparently, they should not differ significantly from influenzal ones, in particular from the changes observed after Spanish influenza, with which psittacosis pneumonia shares the greatest number of common features. Regarding the lymph nodes, especially the bifurcation ones, hyperplasia of the lymphadenoid tissue and swelling and desquamation of the reticulo-endothelium are noted. Sometimes multiple punctate hemorrhages occur in the white matter of the brain, in the serous and mucous membranes, and in the skin. The spleen is usually slightly enlarged; the increase in volume is mainly due to blood congestion and swelling of the reticulo-endothelium. In the liver, besides swelling and desquamation of the reticulo-endothelium, degeneration of the liver cells themselves is often sharply pronounced. In the kidneys, besides the picture of pronounced degeneration, there are sometimes hemorrhages in the glomeruli. The myocardium undergoes degenerative changes common to an infectious disease. A catarrhal state of the small and large intestines is very often noted. A comparison of data from numerous autopsies of patients who died from psittacosis leads to the recognition that there are no specific pathological-anatomical changes peculiar only to psittacosis. Morphological changes are closest to the changes observed in influenza.
N. Krayevsky. Symptomatology. In humans, the incubation period for psittacosis lasts on average from 8 to 15 days, but it can be somewhat shorter or longer. Apparently, the method of infection has an influence on the length of the incubation: when infected through the mouth or after a parrot bite, the infection is shorter. In the picture of the disease itself, there is not a single sign that could be considered pathognomonic. The disease almost always begins suddenly, without precursors, and only in some cases was a gradual onset noted. The patient develops severe chills, general malaise, and aching, often accompanied by vomiting and a severe headache. Usually, the patient is drowsy and apathetic from the very beginning of the disease. Sometimes excitement and delirium are observed. Quite often, diphtheroid angina is observed in the throat, especially if the infection occurred through the mouth. Diarrhea is as common as constipation. The temperature (Fig. 3) rises from the very first days of the disease to 40–40.5° and stays at this level for 10–15 days, and then gradually descends.
Figure 3. Temperature curve in psittacosis. The most characteristic and constant signs are observed in the lungs. Almost from the first days of the disease, phenomena of diffuse bronchitis can be confirmed, but the pulmonary focus is discovered only towards the end of the first week. At this time, or even earlier, a similar focus may appear in the other lung. Pulmonary phenomena last the entire time that the temperature remains at a high level. If the patient recovers, the focus is rapidly resorbed and leaves no traces in the lungs after recovery. From the very first days of the disease, the patient suffers from shortness of breath, but apparently, breathing is difficult not because of pulmonary phenomena, but because of general intoxication, especially since the difficulty in breathing begins even before the appearance of the focus in the lung. It is characteristic that the patient almost does not cough and has almost no sputum production, and if there is sputum, it is not characteristic (mucous and purulent). The patient is usually pale, their pulse is slow (from 90 to 100 per minute), despite the high temperature, and is often dicrotic, as in typhoid fever. Cyanosis of the cheeks and lips is often observed. The tongue is initially coated but quickly clears and becomes red at the edges. Appetite is absent not only during the disease but also for a long time after recovery. Flatulence and severe thirst are frequent. The liver is usually not enlarged, while the spleen is rarely enlarged. Nervous phenomena are always strongly pronounced: drowsiness, headache, delirium, sometimes even Parkinson's syndrome and Kernig's sign. A tendency to collapse is often observed. There is always protein in the urine, and nephritis with hematuria is also often present. Severe azotemia has been described repeatedly. Eruptions on the body are almost never observed. Blood culture and agglutination do not yield any results. The number of leukocytes is usually lowered (5–6 thousand). Examination of sputum yields nothing. The diagnosis is made exclusively on the basis of etiological data, when it is established that the patient was in contact with a parrot. Psittacosis can be confused with typhoid fever, influenza, pneumonia, and initially with general infections in general, but in typhoid fever, the disease begins gradually, pulmonary phenomena are usually absent, there is a rash on the body; blood culture or the agglutination reaction is positive. In influenza, there is no such state of stupor and depression, the pulse is accelerated, and there is cough and sputum. In pneumonia, the patient is excited, their cheeks are flushed, the pulse is rapid, the sputum is rusty, and the disease ends with a crisis. All these differences are not characteristic until the etiology of the disease is precisely established.
Prognosis in psittacosis is grave; lethality on average reaches 20–30%, and according to Cecil, even 30–40%. In prognosis, the severity of nervous phenomena is of particular importance. If the case is heading toward recovery, the temperature begins to drop on the 10th–12th day, and pulmonary phenomena gradually disappear. Recovery proceeds slowly: weakness, headaches, lack of appetite, and insomnia continue for a very long time. In lethal cases, death often occurs on the 4th–5th day. The patient exhibits increased drowsiness, rising temperature, increased general weakness, and acceleration of the pulse. Death can also occur later, on the 10th–12th day, from pulmonary complications, and even later from uremia. Treatment of psittacosis is only symptomatic and boils down to maintaining the patient's strength, alleviating pulmonary symptoms, etc. The patient must be isolated, and all their discharges and excreta must be disinfected. If there is a parrot in the house, the latter must be examined by a veterinarian with all precautions observed. In the event that the parrot is found to be sick, it must be killed, and its carcass and cage burned. Particular attention must be paid to the parrot's excreta, as they are extremely infectious.
Much more important are general preventive measures for combating psittacosis. First of all, in the event of the appearance of suspicious diseases, the import of parrots and other birds usually imported with them, as well as the import of parrot feathers, must be strictly prohibited. In the absence of an epidemic, veterinary control over imported birds is necessary. Cages with parrots should be kept clean, and water and food should be protected from infection and contamination. Healthy birds must be immediately separated from sick ones, their health monitored day by day, and one should not caress the birds with hands or feed them from the mouth. In the event of a parrot's death, its carcass must be sent to a laboratory for examination, the cage burned, and all objects that were in contact with the parrots disinfected. Any illness of a parrot must be immediately reported to veterinary authorities. A doctor, when diagnosing a typhoid-like disease in a patient, must inquire whether there is a parrot in the patient's environment (where parrots might be). Psittacosis must be included in the list of diseases subject to mandatory registration. For the USSR, the question of psittacosis currently has no practical significance, as there is no import of parrots to us, but in the event of the appearance of this disease in Western Europe, doctors of the USSR, especially in port cities, must be familiar with it. A. Rubakin.
Related articles
Mentioned in
Cite this page
“Psittacosis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/psittacosis/