Immunization
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A historical overview of immunization methods from the early 20th century, detailing active, passive, and combined approaches. The article discusses the use of antigens, toxins, and antitoxins to induce immunity, as well as the technical considerations for selecting animals and administration routes in serum production.
Encyclopedia article (1928–1936)
IMMUNIZATION consists of the systematic action of a particular antigen on the organism of an animal for the purpose of imparting immunity to the latter. In this sense, the concept of immunization is identified with vaccination. Immunization aimed at imparting immunity to a specific infection is performed in two fundamentally different ways. 1. The organism itself is engaged in the production of protective substances (antibodies) to destroy a living pathogen that has penetrated from the outside ("bactericidal" immunity), or to neutralize poisonous microbial products—toxins—secreted by living pathogens ("antitoxic" immunity); in the latter case, the pathogen may remain viable in the immune organism for a long time without causing morbid disorders. 2. The organism receives protective substances (antibodies) with the blood serum of another animal of the same or a different species, which has previously undergone systematic treatment with the corresponding antigen. The first method of immunization is called "active," and it is essentially identified with vaccination; the second is called "passive." Accordingly, a distinction is made between active and passive immunity. In addition, a "combined" method of immunization is sometimes used, which consists of first injecting the animal with immune serum to impart passive immunity and immediately following this with active immunization. For the characteristics of active and passive immunity, see Active Immunization. From these characteristics, quite definite indications for one or the other method of immunization follow. Passive immunization is used when infection has already occurred or must inevitably occur in the near future due to close contact with a highly contagious infection, e.g., in the case of an outbreak of measles in institutions for young children (nurseries, kindergartens, children's homes, etc.) or when medical personnel must come into close contact with patients with pneumonic plague, etc. However, the short duration of passive immunity (3–6 weeks) greatly limits its use in the fight against infections; prolonging it by repeated injections of immune serum is inadvisable for two reasons: a) after the second injection of serum, the immunity obtained is even shorter-lived—lasting only 6–8 days—and b) repeated injection of foreign serum sometimes causes rather severe anaphylactic phenomena, or serum sickness, especially with intravenous injection (see Anaphylaxis). As for active immunization, it finds application in cases where, during a widespread epidemic, ordinary sanitary measures prove powerless and one must rely solely on increasing the resistance of the masses of the population. Combined (passive-active) vaccination is expedient when, after rapidly imparting immunity to a threatened subject by introducing ready-made antibodies, it is necessary to make them long-term resistant to an infection. For example, if a child with a positive Schick reaction has virulent diphtheria bacilli in their throat or nose, then after the injection of anti-diphtheria serum, they are immediately immunized with anatoxin or a mixture of diphtheria toxin and antitoxin. In addition to non-susceptibility, through immunization the organism acquires the ability to react in a special and specific way with the antigen used for its immunization. Such a state of the immunized organism, differing from the normal, is called allergic, and the reactions by which this state is detected are called allergic reactions of immunity or infection reactions. Among them, one can mention the reactions of agglutination, precipitation, bacterio-, hemo-, and cytolytic, complement-fixation, antitoxic, opsonic, anaphylactic, etc. All these reactions are used for bacteriological, forensic-medical, and clinical diagnostics; furthermore, immunization with sera serves therapeutic and prophylactic purposes. Immunization aims to induce the maximum accumulation of antibodies in the blood of the immunized animal. The success of immunization depends on many conditions. Of these conditions, the following are particularly important: 1) selection of suitable animals; 2) preparation of a good antigen; 3) an expedient method of introducing the antigen into the animal's organism; 4) correct dosage of the antigen with appropriate intervals between injections. In addition to the general rules followed in selecting animals for immunization (see Hyperimmunization), there are special signs indicating the particular suitability of animals for a given purpose. Such signs include a high content of globulins in the blood and the presence in it, even before the start of immunization, of those antibodies whose accumulation is the goal of immunization. Thus, for anti-diphtheria immunization, horses having a significant amount of diphtheria antitoxin in their blood are particularly suitable; this is established by intradermal injection of a certain amount of diphtheria toxin (absence of infiltrate when several doses of diphtheria toxin lethal to a guinea pig are introduced into the skin). The more antitoxin there is in the horse's blood, the more toxin it tolerates without reaction upon intradermal administration, and the better the results it gives during immunization (Edwin Banzhaf, Arkhipov, et al.). The same applies to rabbits: the more the normal serum possesses agglutinating or hemolytic action against a given antigen, the more suitable the rabbit is for immunization (Ginzburg and Kalinin). The degree of the immunizing effect of an antigen is usually in direct proportion to its toxicity and virulence, although the weakness of an antigen can be partially compensated for by increasing its quantity. But Ehrlich (P. Ehrlich) proved that strong diphtheria and tetanus toxins, during long-term storage even in a refrigerator, lose part of their toxicity while fully retaining their antigenic properties, from which Ehrlich concluded that part of the toxin converts into a non-poisonous variety—toxoids. At higher temperatures, the process of toxoid formation proceeds faster. The addition of certain chemical substances (iodine, formalin) has long been used to weaken the toxicity of toxins, especially tetanus (Nocard, Löwenstein, et al.), at the beginning of animal immunization. Later, Ramon provided a method for the rapid and complete conversion of toxin into an atoxic state (see Anatoxin). Thus, it became possible to conduct successful immunization using completely safe, non-poisonous materials. However, only those anatoxins give good results in immunization that are prepared from highly active starting material. To avoid the risk associated with introducing strong toxins into a sensitive organism, immunization begins with a weak toxin or anatoxin, and only after the animal has been imparted basic immunity do they switch to unweakened toxins. Park proposed imparting basic immunity to the animal by injecting a neutral mixture of toxin and antitoxin. Three to four weeks after injecting a horse with 30–50 cm3 of such a mixture, it tolerates many lethal doses of toxin, which makes it possible to conduct immunization with a very strong toxin without the risk of losing the animal. Others prefer to impart passive immunity to the animal at the beginning of immunization by injecting the corresponding antitoxic serum (tetanus, diphtheria). Immunization begins with the intravenous administration of a significant amount (for a horse 50–100 cm3) of antitoxic serum, and in the first days, injections of increasing doses of toxin alternate with injections of decreasing amounts of antitoxic serum (the American method of immunization). The method of antigen administration depends partly on the goals pursued (see Hyperimmunization). In addition, the following should be guided by: 1. Intracutaneously, or intradermally, only a very limited amount of material (0.3–0.5 cm3) can be introduced, which is why this method is practiced mainly for the inoculation of live virus (smallpox, anthrax), as well as in cases where it is intended to engage the skin in more energetic antibody production, e.g., in staphylococcal and streptococcal conditions of the skin. Besredka believes that by acting on the skin with an antigen, the elements in it are desensitized, due to whose special susceptibility to a given virus the latter is able to penetrate the organism. Thus, local immunity is created, protecting the organism from infection without the formation of antibodies. 2. Intercutaneous, or subcutaneous injection is used most often due to its simplicity and safety. It is contraindicated only in cases where a too sharp local reaction is obtained, sometimes accompanied by more or less widespread necrosis. Such is, for example, the injection of ricin or certain anaerobic cultures and toxins. With subcutaneous injection, it is recommended to make multiple punctures to facilitate the absorption of the antigen and give a more energetic immunizing stimulus. 3. Injection into the muscles is used when it is desired to accelerate the absorption of the antigen.
For the same purpose, injection is made into the parenchyma of the lungs, which, however, is permissible only for solutions and fine suspensions, but not for coarse ones, which might cause embolism of the pulmonary vessels or blockage of the small bronchi. The latter method, however, is by no means as dangerous as might be supposed, and it is frequently practiced in the immunization of animals. 4. Injection into the abdominal cavity (intraperitoneally) is a favorite method for the immunization of small animals (rabbits, guinea pigs), especially when suspensions of microbes, erythrocytes, or any water-insoluble particles requiring vigorous absorption are used as the antigen. 5. Injection into a vein (intravenously) is suitable only for aqueous solutions or fine (e.g., bacterial) suspensions incapable of causing vascular embolism. With this method of administration, the antigen is distributed throughout the entire organism. Intravenous injection is contraindicated when there is a danger of anaphylactic shock. Due to the absence of a local reaction and the rapid absorption of the antigen, intravenous injections can be repeated more frequently than subcutaneous ones. 6. Administration per os is used for special indications, e.g., in immunization with ricin (P. Ehrlich), which irritates the subcutaneous tissue too severely, or in immunization against intestinal infections according to the Besredka method (Besredka tablets or liquid vaccine). 7. In rarer cases, immunization through the mucous membranes of the nose (Dzerzhgovsky, Ramon—against diphtheria) or the pharynx (Belonovsky—against scarlet fever) is practiced. However, the latter methods have no serious significance, since it is impossible to account for the amount of antigen entering the body, and consequently, the results of immunization must be characterized by randomness and low reliability. Therefore, Ramon recommends his method only in those rare cases where all other methods of immunization are for some reason unfeasible (for example, extreme nervousness of the subject being immunized). The next important task facing the immunizer is the expedient dosage of the antigen. Should one take the maximum doses of antigen that the animal is able to withstand, or is it better to administer smaller doses but more frequently? Initially, it was believed that the result of immunization was in direct proportion to the amount of antigen introduced into the body. From this followed the desire to introduce maximum quantities. Naturally, the animal reacts to such an injection with severe general and local phenomena. However, as early as the end of the 19th century, it was proven (Korshun) that the amount of antibodies accumulating in the animal's blood does not depend on the amount of antigen administered to it, and that better results are obtained with the "conservative" method of immunization, when smaller doses of antigen are used, administered more frequently so that the physiological balance of the organism is disturbed as little as possible. But too small doses of antigen do not give a sufficiently vigorous immunizing stimulus to the body (for antibody production). Thus, the art of the immunizer lies in the ability to choose the proper dosage of antigen and to make the correct intervals between injections. The significance of what has just been said is evident, among other things, from the research of Wright, who, determining the amount of opsonins in the blood during immunization, showed the following: the amount of opsonins in the blood decreases immediately after the injection of the antigen ("negative phase"), only to begin rising again after some time and gradually rise to a level exceeding their initial state. If repeated injections of antigen are made at the moment when the antibody curve is rising, then, despite the negative phase accompanying each injection, the amount of antibodies in the blood will increase step-wise, as shown by curve A (see figure). Conversely, if
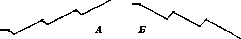
the injection is made before the negative phase has completely leveled out and the height of the curve has exceeded its previous level, then the effect of immunization may even be the opposite (curve B). In practice, all transitions between these two extreme types of curves are conceivable. The depth of the negative phase depends on the dose of the antigen and on the individuality of the animal: the larger the dose of antigen taken for injection and the less resistant the organism is to the given antigen, the deeper the negative phase and the more difficult the animal is to immunize. However, when using small doses of antigen that do not cause a severe and prolonged painful reaction, the role of the negative phase is completely obscured. But in any case, to avoid the cumulative effect of the antigen, the next injection should be performed no earlier than the complete disappearance of the reaction to the previous injection.
Isoimmunization is the name given to the repeated parenteral administration of tissues, organs, or any other components of the body of a given animal species to another individual of the same species. Such is, for example, the immunization of one goat with washed erythrocytes, ground testicular glands, etc., taken from other goats. As Ehrlich and Morgenroth showed, it is possible to obtain isoantibodies in this way, but only with great difficulty. Literature: see literature for the article Immunity. S. Korshun.
Related articles
Mentioned in
Cite this page
“Immunization.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/immunization/