Protective Reflexes
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Protective reflexes in animals range from simple responses like pupil constriction to complex behaviors such as escape from threats. These reflexes can be both unconditioned and conditioned, and play a crucial role in survival by overriding other physiological responses.
Encyclopedia article (1928–1936)
PROTECTIVE REFLEXES. The area of protective reflexes in the organism of animals, both lower and higher, is extremely extensive and diverse. This includes the activity of stinging organs (jellyfish) and electric organs (rays). For the most part, protective reflexes are expressed in the form of movement or secretion; among the most well-known, we mention the action of the muscle that constricts the pupil, as well as the circular muscle of the eye; each of these muscles protects the most important organ of vision from the effects of excessive light and threatening mechanical stimuli. From these reactions, one can see that protective reflexes can be caused not only by unconditioned but also by conditioned irritation. Among the more complex manifestations of protective reflexes, we can name the secretion of poison from a special gland into the oral cavity in snakes, as well as the secretion into the same oral cavity of the secretions of the salivary glands of mammals in response to the action of an irritating substance (acids, alkalis). With the establishment of the possibility of causing such protective reflexes by merely showing a vessel with acid, in essence, the physiology of conditioned reflexes began. If the simple protective reflexes listed above are regulated from the spinal cord and the lower parts of the brain, then complex protective reflexes, which include acts of escape from a stronger opponent, as well as various actions observed "in a state of necessary self-defense", are coordinated with the help of centers located in the cortex of the cerebral hemispheres, in particular in the so-called motor sphere (analyzer). Such protective reflexes have been repeatedly studied by representatives of American behaviorism (see). I. P. Pavlov gives protective reflexes (self-defense) first place in the "hierarchy" of instincts as complex unconditioned reflexes. When applied in experiment, protective reflexes, provided they have a certain strength, have an inhibitory effect not only on sexual but even on food reflexes (negative induction). Therefore, when training animals, it is recommended to avoid the use of protective reflexes, using them only as the most extreme means of influence. Protective reflexes are thus, as it were, a natural dominant (see) in the sense of Uktomsky. However, this by no means follows that the reflex itself cannot be made a conditioned exciter, i.e., associated with some other reaction of the body. Thus, in one of Pavlov's basic experiments on a dog, the protective reflex to electrical irritation was, through starvation, switched to the food center, the importance of which is particularly emphasized by Sherrington.
Y. Frolov. Protective reflexes in pathology. 3 p. (reflexes de defense, Abwehrreflexe), or 'reflexes of spinal automatism' (reflexes d'automatisme medullaire, Pierre Marie), are involuntary complex tonic movements that usually involve several segments of a limb, allowing one to detect certain spinal synergies in their motor formula. They appear in response to irritation of the skin or deep tissues and develop under conditions of more or less complete functional isolation of the spinal cord, i.e., in various types of spastic paralyzes. Van Gehuchten was the first to propose distinguishing between proper skin reflexes (abdominal, cremasteric) and 'protective skin reflexes' (reflexes cutanes de defense), which are intensified in pathological conditions. He was also the first to express the idea, later confirmed, that these latter reflexes possess a short, purely spinal arc. Subsequently, Babinski and Pierre Marie-Foix (Babinski, 1911; Pierre Marie, Foix, 1912) drew attention to these reflexes through their works, and further study of which has been actively continuing to the present time, mainly in French (and partly in Russian) literature. Unlike periosteal and tendon reflexes, protective reflexes differ both in the method of elicitation and in their slower tempo, but mainly in that they do not lead to the instantaneous contraction of one specific muscle, but to complex movements in which a number of separate muscle groups, innervated from a series of adjacent spinal segments, participate coordinately. In this respect, protective reflexes are analogous to the reflexes of a decapitated frog or dog with a severed spinal cord (experiments of Sherrington and his school). The controversy as to whether protective reflexes in humans (as Babinsky thought) signify a freed spinal 'protection' mechanism (removal from harmful irritant) or (as Pierre Marie thought) a walking mechanism (in favor of which the crossed extension reflex would speak, see below) should be resolved in the sense that protective reflexes are generally a sign of freed automatism of the spinal cord, in which the most diverse synergies may be revealed, including of course protection synergies and walking synergies, as well as (probably) many others. The purely spinal origin of protective reflexes is confirmed by the fact that they are observed in humans even after a complete break in the conductivity of the spinal cord. Protective reflexes are elicited by: stroking the skin, a series of repeated pricks, cooling (a drop of ether!), faradic irritation of the skin, pinching, pressure on deep tissues (tendons, muscles), repeated tapping, and stretched position of muscles. The irritant must always act for a more or less prolonged time (cumulation of irritation). Single irritations (prick, percussion of tendon) are usually without result. Coughing and straining also elicit protective reflexes. After each individual protective reflex, a refractory phase temporarily occurs. The motor formula of protective reflexes can be very diverse, but in each given patient at a certain period of his disease, protective reflexes of the same type are usually observed. On the lower extremities, the 'shortening' and 'lengthening' types predominate. The first, which is significantly more common ('triple retrait', flexion reflex), consists of tonic flexion of the thigh, flexion of the leg, and extension of the foot; the second (extension reflex) consists of extension of the thigh, extension of the leg, and flexion of the foot. The reflex can irradiate in the transverse direction, sometimes causing a reflex of opposite sign on the opposite leg, for example, on the irritated leg—a shortening reflex, and on the opposite—a lengthening reflex (so-called crossed extension reflex). With these movements of the limb in the sagittal plane, movements in other planes can also be combined, for example, in the lengthening reflex, adduction of the thigh can be observed, in the shortening reflex—internal rotation of the thigh—adduction of the foot or else external rotation of the thigh—abduction of the foot, etc. Irritations on the periphery sometimes give shortening reflexes while irritations in the proximal parts of the limb—lengthening reflexes. Furthermore, the motor formula of protective reflexes can be modified in one direction or another depending on the initial position of the limb. On the upper extremities, even more varied combinations of extension and flexion movements of the shoulder, forearm, hand, and fingers are observed. A protective convulsion can spread to the muscles of the back (lordosis, lateral curvatures of the spine) and to the musculature of the anterior abdominal wall, and can also be accompanied by involuntary emptying of the bladder. Protective reflexes are often very painful. The Oppenheim, Marie-Foix, palm stroking reflex, femoral reflex of Remak, and some other reflexes described at one time as independent entities are merely different modifications of protective reflexes. The Babinski symptom has many features in common with protective reflexes. If protective reflexes reach great intensity, spontaneous spasms of the protective type develop, appearing already without any external irritation and sometimes possessing their own rhythm. In their genesis, the cumulation of constantly arriving centripetal irritation, originating for example from a distended bladder or from a bedsore or from irritation of the posterior roots by the same process (tumor, syphilitic meningomyelitis) that led to the disease of the spinal cord, probably has significance. These spontaneous movements, if they continue for a longer time, can lead to the development of a persistent protective contracture, which is always prognostically unfavorable. This includes the 'flexor contracture' of the lower extremities, when the maximally flexed legs are pressed tightly to the trunk; usually at this time the muscles of the anterior abdominal wall are also maximally tensed. In strong protective reflexes, their receptive zone shows wide divergence and can (for example in far advanced lateral amyotrophic sclerosis) occupy the entire surface of the body including the skin of the auricle. If hyperreflexia depends on a locally limited process in the spinal cord (tumor), the upper boundary of the receptive zone of protective reflexes stops at the level of the lower boundary of the spinal process (Babinsky). This is very important for the diagnosis of spinal cord tumors, since other symptoms of the tumor (anesthesias, paralyses) indicate only the upper boundary of spinal compression. By comparing these two levels and, so to speak, subtracting one from the other, one can thus judge the extent of the non-functioning area in the spinal cord (see figure). If protective reflexes are weakly expressed or if the upper boundary of the receptive zone does not rise above the inguinal fold, one cannot use this kind of reasoning. In normal conditions, protective reflexes are absent. They are especially strongly developed in diseases of the spinal cord (tumors of the spine, syphilitic meningomyelitis, tumors, etc.). In Brown-Séquard's syndrome, protective reflexes are stronger on the side of paralysis. Not fundamentally related to tendon reflexes, they can also be observed in their absence (Friedreich's disease, spinal cord syphilis in combination with tabes dorsalis, etc.). It has been expressed that for the realization of protective reflexes, the corresponding segments of the spinal cord must be isolated both from pyramidal and simultaneously from extrapyramidal impulses. In diseases of the brain, protective reflexes are observed only in the initial period, gradually weakening thereafter; they are thus not characteristic for residual hemiplegia. They are very strong (which therefore always means a very poor prognosis) only in fresh cases of extensive cerebral shutdowns (fresh extensive hemorrhages or thromboses, ventricular hemorrhages, encephalitis, extensive trauma, etc.), appearing often during a comatose state. They are then expressed according to the hemiplegic type, preferring the upper extremity, and often irradiate both in the transverse and longitudinal (from arm to leg and vice versa) directions, and like protective reflexes in spinal pathology, they can give rise to the development of spontaneous tonic spasms of the protective type, which, merging with each other, can lead to a state of very strong but variable hypertension (so-called 'early contracture of hemiplegics', according to other authors dependent on direct irritation of pyramidal pathways). If the patient survives, in these cases a rapid reverse development of all protective symptoms occurs, and later tendon reflexes intensify, synkineses develop, and the so-called 'late' contracture of hemiplegics of completely different origin gradually establishes.
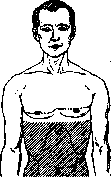
Receptive zone of protective reflexes (shaded) in the case of extramedullary tumor of IV and V thoracic segments. 56
Related articles
Mentioned in
Cite this page
“Protective Reflexes.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/protective-reflexes/