Reserve Alkalinity
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Reserve alkalinity is the volume of carbon dioxide that can be released from 100 cm³ of venous blood or plasma previously saturated with alveolar air or carbon dioxide at a tension of 40 mm Hg. This concept, introduced by Jaquet in 1892 and applied by Van Slyke in 1917, represents the amount of bases remaining after neutralization by non-volatile acids and serves as an indicator of the alkali reserve that can additionally bind carbon dioxide.
Encyclopedia article (1928–1936)
RESERVE ALKALINITY, according to Van Slyke (see Van Slyke methods) - the volume of carbon dioxide that can be released from 100 cm3 of venous blood or blood plasma, previously saturated at room temperature with alveolar air or carbon dioxide at a tension of 40 mm Hg. The concept of R. a. was first introduced in 1892 by Jaquet and again applied by Van Slyke in 1917. In 1877, Walter demonstrated in dogs the relationship between acid intoxication and bicarbonate content in the blood; he found that the carbon dioxide content in the blood is proportional to the amount of unbound bases and that it decreases correspondingly with the amount of acid introduced. Later, in 1909, Henderson showed that carbon dioxide present in the blood in the form of bicarbonates (HCO3-) normally constitutes about 95% of all carbon dioxide in the blood. In 1883, Stadelmann applied Walter's observations in clinical practice - he noted the similarity between the picture of diabetic coma and acid intoxication and found increased acid excretion by the body during coma and in the pre-comatose state. He also proposed NaHCO3 as a therapeutic agent. In 1920, a number of authors observed a significant increase in bicarbonate content in the blood of dogs in which the pylorus was closed and who were subjected to gastric lavage for several days, causing a large loss of HCl. The expressions 'blood bicarbonates', 'carbon dioxide binding capacity' are used to define the same thing that is now understood under the term reserve alkalinity. R. a. represents the amount of bases remaining after their neutralization by non-volatile acids, and represents an indicator of the reserve of alkalis that can additionally bind carbon dioxide. Normal fluctuations of R. a., according to Van Slyke, are 55-70% (equivalent to 23-32 millimoles of HCO3- per 1 liter); for children, normal amounts are somewhat lower. According to Schloss, in infants R. a. is expressed as 46-63%. Constant values are maintained approximately until 4-5 years of age. After that, a progressive increase to adult values is noted. When determining CO2 in plasma, the result obtained to a certain degree depends on how the plasma was obtained, under paraffin or by separating erythrocytes and subsequently saturating it with carbon dioxide.
The CO2 content in the blood can be determined using the Barcroft apparatus or by the Van Slyke method (see). When plasma is saturated with carbon dioxide at 40 mm pressure and 38°, the H2CO3 content corresponds to 2.75 volume %, or 1.23 millimoles of H2CO3 per 1 liter. The total amount of CO2 is equivalent to HCO3- + H2CO3; subtracting from this value 1.23 millimoles of H2CO3, we obtain the HCO3- content (see Bicarbonates). In addition to determining R. a. by volumetric methods, the manometric method is often used recently: The extracted gases are brought to a certain volume, and their amount is determined by the pressure read on the manometer. This makes the determination more accurate, independent of barometric pressure. The advantage of this method is that the researcher can choose the measured volume and pressure such that the errors in volume and pressure determination are equal. The accuracy of determination thus becomes independent of the CO2 content.
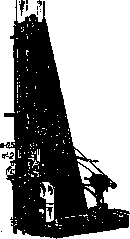
Apparatus (see figure). Pipette A has two marks for setting at a at 0.5 cm3 and a' at 2 cm3. The determination is carried out as follows: 1 cm3 of blood or plasma is admitted through stopcock B, the blood residue is washed out with water, 0.2 cm3 of a CO2-free solution of lactic acid is added. By lowering the equalizing bulb C, a Torricellian vacuum is created and the gases are extracted by shaking for two minutes. The volume of gas is brought to a or a'; pressure px is read on manometer D. 0.2 cm3 of a 5% NaOH solution is introduced into the pipette to absorb the released CO2 and pressure py is read after bringing the gases back to the original volume. The pressure P for carbon dioxide is thus pCO2 = px - py. The determination of plasma bicarbonates can be performed by titration (Van Slyke, Stillman, Cullen). The principle is based on determining the amount of HCl required to convert plasma NaHCO3 to NaCl; the pH at the end of titration must be the same as in the original plasma to prevent other buffers besides HCO3- from participating in the reaction. An excess of n/100 HCl is added to the plasma, free CO2 is removed, and it is titrated with n/100 NaOH to the original pH=7.4. Indicator is phenolsulfonphthalein. Titration does not give as accurate results as the gasometric method, especially when using a manometric apparatus, however the discrepancy rarely exceeds 0.3 millimoles of HCO3- per 1 liter (=0.7 vol. % CO2). Simple titration of plasma or blood does not determine the true (active) reaction (see Active reaction), because it determines not only the amount of free, dissociated ions, but also potential ions, i.e., those released during titration (see Buffer properties).
A decrease in R. a. was at one time considered a sufficient sign for the diagnosis of acidosis, but although this is true in most cases, it can sometimes lead to incorrect conclusions, because a decrease in R. a. indicates only a decrease in bound CO2, but does not indicate the relationship between HCO3- and free carbonic acid, which only collectively determine the state of the acid-base balance and affect the active reaction (see Acidosis - blood acidosis, and Blood - physicochemical properties of blood). The terms acidosis and alkalosis are applied to states associated with changes in 1) bicarbonate content (reserve alkalinity), 2) active blood reaction (decrease or increase in H-ion concentration). To characterize acidosis in relation to blood, two kinds of data are necessary: 1) determination of R. a., 2) determination of free H2CO3. Table 1. Determined by Reserve alkalinity CO2 tension and H-ion concentration Determination Examples Normal Normal Normacidemia - euglycemia Normal - eucapnia Increased Increased Acidemia (acidosis) -hyperglycemia At the beginning of inhaling air rich in CO2 Decreased Decreased Alkalemia (alkalosis)-hypoglycemia At the beginning of artificial hyperventilation Normal or decreased or Decreased Alkalemia-hypoglycemia (alkalosis) Corresponding increased Normal. Normacidemia - euglycemia Some time after injecting soda. Corresponding increased State with prolonged CO2 overload (emphysema) More than corresponding increased Acidemia-hyperglycemia (acidosis) During further inhalation of CO2 Normal or increased or Decreased Acidemia-hyperglycemia (acidosis) At the beginning of injecting acid Corresponding decreased Normal. Normacidemia - euglycemia Some time after injecting acid. State with prolonged decreased CO2 tension. Hyperventilation at altitudes. Apetonemia More than corresponding decreased Alkalemia-hypoglycemia (alkalosis) During further vigorous hyperventilation Table 2. Res. alk. Type of disorder or total CO2 content Examples Acidosis 1) Due to bicarbonate deficiency (non-gases) a) compensated group 8 b) uncompensated group 9 Decreased Diabetic coma, periodic vomiting, infantile gastro-enteritis, dysentery, uremia, salicylate poisoning 2) Due to CO2 excess (gases) a) compensated group 5 b) uncompensated group 4 Increased Morphine poisoning, emphysema Alkalosis 1) Due to bicarbonate excess (non-gases) a) compensated group 5 b) uncompensated group 6 Increased Injection of bicarbonate soda. High intestinal obstruction 2) Due to CO2 deficiency (gases) a) compensated group 8 b) uncompensated group 7 Decreased Conditions of anoxia, hyperventilation at altitudes
While in blood, shifts in active reaction are hardly observed (see: Acidosis - blood acidosis), the active reaction of tissues is a much less constant quantity, and the shift in pH can reach significant values. By combining changes in HCO3- and H2CO3, eight different types of acid-base balance disturbance can occur (Van Slyke) (Table 1). Thus the same condition can be defined by one author as acidosis, by another as alkalosis, therefore it is necessary to more precisely specify to which feature this designation should be attributed. Haldane proposes a classification that in individual cases indicates the processes causing the corresponding change (Table 2).
Related articles
Mentioned in
Cite this page
“Reserve Alkalinity.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/reserve-alkalinity/