Tonsil Pharyngeal
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The article describes the anatomy, physiology, and inflammatory diseases of the pharyngeal tonsil (palatine tonsil), including its structure, function theories, and treatment approaches. It discusses various theories about the tonsil's protective role versus its function as an infection gateway, and examines the histological structure and physiological processes of the tonsillar tissue.
Encyclopedia article (1928–1936)
Tonsil Pharyngeal, Palatine (tonsilla). Under the general name of tonsils are united (anatomically and physiologically equivalent) lymphadenoid formations that are part of the so-called Waldeyer's lymphatic ring of the pharynx. When speaking of the tonsil, one usually refers to the palatine tonsil (tonsilla palatina). The pharyngeal tonsil (tonsilla pharyngea; also called the third tonsil of Luschka) is a collection of lymphadenoid tissue in the vault of the nasopharynx (see Pharynx).-Inflammatory diseases. Acute inflammation, angina retronasalis, develops under the influence of chemical, thermal, and mechanical irritations, but more often from various infectious agents (streptococci, staphylococci, pneumococci) and manifests as fever (sometimes temperature above 39°), runny nose, sensation of dryness, burning, and soreness in the posterior parts of the nose and in the pharynx, moderate pain in the pharynx, dry cough, sometimes tingling in the ears. Upon examination of the pharynx per os, slight hyperemia, especially of the posterior pillars, and thick mucus descending from the nasopharynx along the posterior wall are noted. Posterior rhinoscopy reveals severe redness and swelling of the pharyngeal tonsil, and its fissures are filled with mucopurulent exudate.-Angina retronasalis in children is sometimes accompanied by painful swelling of the cervical lymph glands (so-called glandular fever, see). The disease usually passes without a trace within several days. Of the complications, inflammation of the middle ear deserves special attention.-Treatment: bed rest, heating compress on the throat, atomization or rinsing with alkaline solutions, instillation into the nose twice a day a 1-2% solution of protargol. In frequent recurrences in children-adenotomy.-Chronic inflammations accompany similar diseases of the pharyngeal mucosa, resp. nasopharyngeal mucosa (see Pharyngitis). Hyperplasia of the pharyngeal tonsil-see Adenoids. The palatine tonsil (tonsilla palatina), located on the lateral wall of mesopharyngis, occupies the triangular space formed between the anterior and posterior pillars, the so-called inter-pillar space, or tonsillar fossa. Isolated from the surrounding tissues, the tonsil has an oval, sometimes spherical shape, flattened from the sides. Its long axis runs obliquely from top to bottom and slightly from front to back. In the tonsil, one should distinguish the medial surface, facing mesopharynx, and the lateral surface, which is inserted into the aforementioned inter-pillar space. The lateral surface is smooth and consists of a dense whitish fibrous capsule (about 1 mm), the so-called capsule. From the capsule, connective tissue plates and strands extend in various directions into the thickness of the gland, thanks to which the tonsil is in close connection with the capsule. On the outer surface of the capsule lies a thin layer of loose peritonsillar adipose tissue, which continues upward into the submucous layer of the soft palate, and downward to the base of the tongue, which explains the swelling of the tongue and epiglottic-lingual folds in peritonsillar abscess. Further, outward lies the superior constrictor of the pharynx, which in different cases has varying thickness and is covered on its outer surface with a dense aponeurosis, separating the area of the tonsil from the lateral pharyngeal-mandibular space. The surface of the tonsil facing mesopharynx is rarely smooth. Much more often it is covered with a series of fissures of extremely intricate appearance, with ridge-like elevations alternating with rounded or slit-like depressions. These are the so-called lacunae of the tonsil, or crypts, which are nothing more than simple or common openings of channels penetrating the thickness of the tonsil and extending to the capsule. In view of the frequency of inflammatory processes occurring in the pharyngeal area, normal tonsils are found in adults at least less frequently than pathologically altered ones. Therefore, their size is subject to significant fluctuations. Physiology of the tonsils. Regarding the role and significance of the tonsils in the body, the opinions of authors differ. Some consider them organs possessing a protective adaptation, having the purpose of shielding the body from the penetration of infection (the "protective theory" of Brieger and Gorke). Others, based on clinical observations confirming the indisputable causal relationship between inflammatory diseases of the tonsils and subsequent general diseases, consider the tonsils as "portals of entry" for various infections (the "infectious theory"). These contradictory opinions about the physiology of the tonsils have found reflection among clinicians in one or another approach to patients with tonsillar diseases. Supporters of the protective function categorically oppose any surgical interventions and only in extreme cases allow incision of the crypts, while others advocate for the radical removal of the tonsils as superfluous and harmful formations. The basis of these contradictory opinions is the erroneous concept that the tonsils are independent organs possessing a special function peculiar to them alone. Supporters of the "protective theory" consider the tonsils as excretory organs, assuming that tissue fluid flows through the tonsils from inside to outward to the covering epithelium and through ready-made openings in it, the so-called physiological fissures, due to the emigration of leukocytes, is secreted into the pharyngeal cavity (Gorke, Henke). Fleischmann attempted to classify them as organs with internal secretion, i.e., as endocrine glands, based on the presence of reducing substances in the tonsils. This hypothesis was soon rejected after reducing substances were found in the blood, urine, muscle tissue, lymph glands, salivary glands, etc. Finally, the view was expressed that the palatine tonsils are a regional (regional) gland for the nasal and oral cavities and as such have afferent lymphatic vessels (Henke). Their protective function should consist in the fact that various substances (including pathogenic ones) that have entered under the mucous membrane of the upper respiratory tract are carried by the lymph current to the tonsils and through the intercellular spaces together with tissue fluid are secreted onto the surface of the tonsil into the oral cavity. The view of the tonsil as a lymphatic gland having afferent lymphatic vessels and therefore allowing the existence of constant secretion directed to the surface of the tonsil, i.e., centrifugally, has been refuted by the research of Schlemmer, confirmed by V. Zak and V. Talalaev, which showed that the tonsils do not lie on the path of lymph flow, do not have afferent lymphatic vessels, and therefore are not regional glands; lymph outflow from the tonsils occurs only outward through efferent lymphatic vessels, i.e., centripetally to the anterior-superior group of lymph nodes jugulares. The network of lymphatic capillaries in the tonsil represents a closed system, blindly ending in the direction of the crypts. There is no lymph flow directed to the surface of the tonsil, i.e., centrifugally. Consequently, there is no basis to attribute to the tonsils a protective function in the sense of Brieger and Gorke. Follicles, which are an integral part of the tonsils and the rest of the peripheral follicular apparatus of the pharynx, closely approach the epithelial covering, and these areas are places characterized by fairly high absorptive capacity. The tonsils and the rest of the peripheral apparatus of the pharynx are in constant contact with the external environment, and mainly with the contents of the oral and pharyngeal cavities, rich in bacterial flora (V. Talalaev and V. Zak). The widely held view of Flemming, who considered the light centers of follicles ("secondary follicles") as foci of lymphocyte reproduction, is now abandoned. It has been proven that secondary follicles, which Flemming considers the main site of lymphocyte reproduction, occur only after birth, mainly by the end of the 1st year of life. Since a huge number of lymphocytes are formed by the end of embryonic life, one would expect strong development of follicles in the tonsils, which however is not observed. Recently, Hellman has put forward a new point of view regarding the function of the peripheral follicular apparatus, to which the tonsils in particular belong. The purpose of the follicular apparatus is not only the production of lymphocytes but also the neutralization of infectious-toxic agents penetrating into the blood. Taking into account the permeability of the epithelial covering over the follicles, it must be assumed that throughout human life, infectious-toxic substances are absorbed, which cause reactive changes in the lymphadenoid tissue and, due to the physiological activity of the follicles, become harmless. In the tonsils, so to speak, continuous physiological intoxication occurs. When irritants penetrate in large quantities or irritants possessing high virulence, the follicles go beyond the limits of their physiological activity, and then an increased (pathological) reaction of the lymphadenoid tissue and follicles occurs, the expression of which is hyperplasia. If the intoxication is so significant that poisonous substances (bacteria, toxins) cannot be destroyed and neutralized by the increased activity of the follicles, then cell decay, fibrin deposition, extravasates, etc. occur.
From this point of view, the follicles can be considered as a reactive apparatus, and then many phenomena in the physiology and clinic of the T. receive a different light. It becomes understandable why follicles of lymphoid tissue appear only after birth, and not at the end of embryonic life: milk in the extrauterine life of the organism is exposed to the external environment (bacteria, toxins). The hyperplasia of the lymphatic pharyngeal ring, observed so often in childhood, finds among other things a satisfactory explanation in the circumstance that the child's organism is particularly strongly subject to various harmful external influences and mainly infections. In older age, in connection with infectious diseases and the process of age-related increase in resistance or relative immunity, the lymphatic apparatus of the pharynx and in particular the T. do not have the same significance as in childhood, and therefore undergo involution. The process of involution subsequently leads to atrophy of the lymphoid tissue: disappearance of lymphoid elements, atrophy of follicles and subsequent proliferation of connective tissue. Therefore, in adults one so often has to observe T. with an uneven bumpy surface, with wide fissures and with dilated and deep lacunae. From this point of view, local acute inflammatory phenomena in the area of the T. in scarlet fever, diphtheria, influenza and other infectious diseases should be considered as a partial manifestation of the general infectious disease. According to the generally accepted view, acute anginas (catarrhal, lacunar, follicular) represent a primary manifestation of a general, usually infectious disease. Fein expresses a new view on angina as a secondary disease. He believes that in angina there is never an isolated disease of any one department of the lymphatic pharyngeal ring (palatine, pharyngeal or lingual tonsils), but the inflammatory process always simultaneously involves all these departments. However, the degree of inflammatory phenomena can be different in different people and depends on the greater or lesser development of lymphoid tissue in one or another department of the pharynx. An inflammatory disease involving the entire lymphatic complex of the pharynx can occur only under the condition of simultaneous action of pathogenic bacteria on all departments of the lymphatic pharyngeal ring, which can be admitted only in exceptional cases. Angina, which is a non-specific inflammatory disease of the lymphatic pharyngeal ring, is not a local disease and not a primary manifestation of a general disease, but represents a septic disease of the entire organism, which secondarily localizes in the lymphatic pharyngeal ring. Fein considers acute angina as a secondary phenomenon, as a pathological reaction of lymphoid tissue occurring under the influence of primary inflammation of any other localization. The name "angiosis" in his opinion is the most appropriate for designating the general nature of the disease. Fein's theory is not shared by all, since it does not agree with some clinical observations. Among other things, this theory leaves unexplained the fact that after removal of the T. (tonsillectomy) recurrent anginas cease and their subsequent complications (nephritis, prolonged temperature, joint rheumatism, etc.) are eliminated. The participation of the lymphatic pharyngeal ring of Waldeyer in blood diseases. In leukemia, characteristic changes are observed in the area of the lymphatic pharyngeal ring of Waldeyer and in particular on the palatine T., which reach enormous sizes, even touch each other along the median line and can cause difficulty in breathing. At this, a special pallor, yellowish coloration and dryness of the mucous membrane strike the eye. Besides the palatine T., the pharyngeal T., follicles (granulae) on the posterior wall of mesopharyngis, the lateral ridges and the lingual T. can greatly swell. On the palatine T., ulcerative processes have sometimes been observed, running in the form of torpid ulcers or more often-gangrenous angina. In the latter case, the ulcerative process can be accompanied by deep tissue decay and cause erosion of blood vessels with subsequent bleeding and fatal outcome. In myeloid leukemia, changes in the area of the lymphatic pharyngeal ring of Waldeyer are not so sharply expressed as in the lymphatic form. Here also a marked pallor, yellowish coloration of the mucous membrane and greater or lesser swelling of the palatine T. are noted. (On the condition of lymphoid tissue in lymphogranulomatosis and lymphosarcomatosis-see Lymphogranulomatosis, Lymphosarcoma.) The diagnosis in most cases of leukemias is not difficult, excluding ulcerous forms, which can give rise to confusion with angina Vincenti, scurvy, rarely with syphilis and tbc. Differential diagnosis-see Leukemia. Leukemic infiltrates of the palatine T. and pharyngeal T. can be easily confused with hyperplasia of the T. and adenoids. In such cases, error can be easily avoided if attention is paid to the considerable swelling of the submandibular cervical lymph glands and their density, as well as to perform an examination of the blood and internal organs. In leukemia, any operative intervention is absolutely contraindicated on account of the danger of bleeding.

Inflammatory diseases. Acute inflammatory processes in the area of the fauces with predominant participation of the palatine T. (angina, s. amygdalitis lacunaris, angina, s. tonsillitis follicularis, angina herpetica, angina diphtherica, angina scarlatinosa, angina agranulocytotica, angina syphilitica)-see Angina; phlegmonous angina (angina phlegmonosa, syn.: abscessus peritonsillaris, peritonsillitis abscedens)-acute suppuration of the peritonsillar tissue-see Angina.-Chronic inflammations are often a consequence of various forms of acute inflammation or accompany chronic pharyngitis and develop under the influence of various irritants: acute, too hot food, abuse of alcohol and tobacco smoking, inhalation of dusty air when breathing through the mouth, etc., whereby the T. passes into a state of chronic lacunar inflammation. - Hyperplasia of the palatine T. (fig. 1) can be an expression of a general lymphatic constitution. Due to their anatomical position, the palatine T. with their deep crypts to a much greater degree than the rest of the lymphatic apparatus of the pharynx, are under the influence of external factors, mainly infectious and toxic substances. Hyperplasia of the palatine T. is often observed simultaneously with hyperplasia of other departments of the pharyngeal lymphatic ring, especially with adenoids. In adenoids, approximately in 20% the palatine T. are also enlarged. Hyperplastic T. are subject to inflammatory diseases to a much greater degree than normal T., and they usually present a picture of chronic tonsillitis, their crypts are deep, gape, are often filled with plugs, etc. A special rare group is formed by the so-called atypical forms of T. hypertrophy, when not the entire gland enlarges, but its individual lobes, mostly the upper lobe, and these lobes, undergoing considerable hypertrophy, can take the form of either rounded tumors (accessory T.) or tumors on a stalk (tonsilla pendula, lymphoid polyp). If many lobes hypertrophy simultaneously, then papillary papillomatous formations are obtained. Finally, the T. can appear in the form of a large grape-like tumor, on
resembling a bunch of grapes (A. Ivanov). Symptoms caused by hypertrophied tonsils depend on their size and accompanying inflammatory processes. Greatly enlarged tonsils constitute a serious obstacle to breathing, especially if adenoids are also present. However, difficulty in swallowing is usually not observed with them. Often, the symptoms caused by acute inflammatory processes come to the forefront, to which hypertrophied tonsils are particularly predisposed: repeated anginas, peritonsillar abscesses, prolonged fever, parenteral indigestion in early childhood (up to 3 years), as well as their consequences: nephritis, endocarditis, joint rheumatism, chorea minor (more often in children aged 7-16 years), and general sepsis. The diagnosis of tonsil hypertrophy is not difficult: by gently pressing the root of the tongue downward, it is easy to examine the area of the tonsils. In some cases, the tonsils protrude from the arches into the pharyngeal cavity in the form of a large tumor reaching the size of a walnut; sometimes they are so large that they reach the uvula and touch each other. They have a hemispherical shape or are constricted at the base. If the lower pole of the tonsil is hypertrophied, they appear to hang from the base of the tongue (so-called pendulous tonsils). In other cases, the tonsils protrude relatively little from the arches, but their main mass spreads outward. If at the same time the tonsil is covered by a well-developed triangular fold, the tonsil is found to be compressed between the arches (so-called 'amygdale enchatonnee' according to French authors). Such tonsils are only accessible to examination during vomiting movements, when they protrude from the arches compressing them. The examination is supplemented by sounding the deep pockets and crypts, in which purulent fluid and plugs are sometimes found, and the presence of adhesions and scars of the tonsils with the arches is established, indicating former inflammatory diseases of the tonsil. Treatment. In hypertrophy of the tonsils, which is a symptom of constitutional anomaly and is not accompanied by noticeable inflammatory phenomena, surgical intervention is indicated only in cases where their volume causes breathing disorders. Surgical treatment up to 12-15 years consists of the removal or amputation of the hypertrophied part of the tonsil protruding from the arches. Indications for tonsillotomy: breathing disorders, repeated anginas, as well as their complications. Contraindications to the operation are hemophilia, menstruation, acute inflammatory disease of the pharynx, general weakening of the body due to other diseases, the presence of acute infectious diseases in the family or household, the presence of concretions (stones) in the tonsils, detectable by palpation, leukemia. The operation (tonsillotomy, synonym amigdalotomy) is performed with the help of a special guillotine-like instrument - the tonsillotome (Mathieu) or amigdalotome under local anesthesia (smearing with a 5-10% solution of cocaine); in small children local anesthesia is unnecessary, as the operation takes several seconds. Tonsils provided with a stalk and constriction are more conveniently removed with the cold wire loop of Krause or better Brunings. Postoperative regimen: complete rest (bed rest) for 7-10 days, diet (cold liquid or semi-liquid food), gargling. Along with this, general treatment of the body is necessary, which plays a major role: climate, treatment on the seashore (especially the Baltic), salt baths, cod liver oil, hardening, etc. Among the complications after tonsillotomy, bleeding deserves special attention. Some of these bleedings occur immediately after the operation and exceed in size the normal bleeding usually observed after the operation and passing after several gargles - this is so-called primary bleeding. Secondary bleeding appears after a certain interval, sometimes after several days, and is much more serious than primary, as the patient may lose a large amount of blood before help is rendered. Bleeding is rarely arterial, more often the entire surface of the wound bleeds. Methods for stopping bleeding: 1) gargling with cold or icy water, preferably swallowing or sucking pieces of ice; simultaneously cold is applied externally in the form of an ice bag applied behind the angle of the jaw on the operated side; 2) application of astringent solutions, for example tannin, especially in mixture with hydrogen peroxide (a cotton ball soaked in hydrogen peroxide is dipped in tannin powder and then with the help of forceps pressed to the bleeding site); 3) application of chromic acid, fused on a probe (the most effective means for small primary parenchymal hemorrhages); 4) pressure with the finger: the index finger, wrapped in sterile gauze, is inserted into the patient's mouth, and the pulp presses the bleeding tonsil wound, while the thumb of the same hand remains outside the oral cavity and produces counterpressure on the branch of the lower jaw; on the right side the pressure is done with the right hand, and on the left with the left; 5) for pressing the bleeding wound, a number of instruments have been proposed, of which the Mikulicz-Stork hemostat clamp is best known; 6) unquestionably above the listed ones are operative methods. 1) Clamping the arches with Muse forceps or an arterial clamp, the instrument being left in the patient's mouth for a more or less prolonged time. 2) Suturing the arches by applying clips (clips of somewhat larger size are used - approximately 2 cm). First, a long gauze tampon is introduced into the wound with forceps, and over the tampon two clips are applied on the anterior and posterior arches at a distance of 1 cm from each other. To prevent accidental entry of clips into the larynx or esophagus, silk threads are tied to the clips, which are brought out of the mouth and fixed outside the cheek with adhesive tape. The clips are removed after 1-2 days. 3) If it is impossible to stop the bleeding by the above-mentioned method, one has to resort to the last resort - ligation of the external carotid artery on the neck as close as possible to its origin. In case of cardiac failure, fainting, and weak pulse, the subcutaneous injection of saline solution, camphor, etc., is indicated. As mentioned above, hypertrophy of the tonsils is often accompanied by inflammatory phenomena. Chronic tonsillitis is more often observed in adults after physiological involution of the tonsils. On the other hand, certain anatomical peculiarities may be the cause of pathological conditions of the tonsils, predisposing to their diseases. These include adhesions of the tonsils with the arches, strong development of the triangular fold, hypertrophy mainly of the upper pole of the tonsil (so-called pars palatina), which is covered by the arches and deeply immersed in the thickness of the soft palate, etc. Among conservative methods, cauterization should be mentioned, which is indicated in cases where there is free access to the tonsil, i.e. there are no adhesions with the arches, no strongly developed triangular fold. It is contraindicated in hypertrophy of the palatal lobe (pars palatina), in tonsils compressed by the arches. It is performed under local anesthesia by smearing with a 10% solution of cocaine. Operative methods: partial tonsillotomy consists in the removal of the upper pole of the tonsil, as in this place the deep pockets open predominantly, which serve as foci of infection. Removal in parts (morcellement) with the help of the tonsillotome (forceps) of Hartmann. The aim of the operation is the wide opening of the crypts and the most complete removal of the tonsil to its capsule. With the above-mentioned anatomical peculiarities, these operative methods do not achieve their aim. It goes without saying that there can be no question of any single universal operative method. In each individual case, it is necessary to strictly individualize the choice of one or another surgical intervention. This must be said especially about cauterization, which has many hot supporters who apply this method exclusively in all cases. The application of this method in the case of a strongly developed triangular fold, in compressed tonsils must inevitably lead to the opposite results: the formation of new adhesions and scars and consequently to the worsening of the previous condition. The only reliable method is the complete removal of the tonsil together with its capsule, so-called tonsillectomy, after 15 years, i.e. after physiological involution of the tonsil. Indications for tonsillectomy are: 1) Local diseases of the tonsils - repeated anginas and peritonsillar abscesses, chronic tonsillitis causing bad breath in the absence of other causes (cavities), painful sensations on swallowing, talking, cough (so-called tonsillar cough), tickling and burning in the throat, sensation of a foreign body - are relative indications when other therapeutic methods are ineffective. 2) Diseases of distant organs, occurring after an angina or as a result of a long-lasting disease of the tonsil: polyarthritis, chronic rheumatism, endocarditis, nephritis (glomerulonephritis), subfebrile fever, sepsis, asthma. Contraindications are the same as for tonsillotomy. The operation is performed under local anesthesia, which is achieved by injecting a 1/2% solution of novocaine with adrenaline into the upper and lower end of the anterior arch and into the posterior arch.
Complete anesthesia sets in after 10 minutes. The tonsil is grasped with forceps (preferably Yankauer's) near the triangular fold and slightly pulled outward and forward; the incision is made through the mucous membrane along the entire anterior pillar (Fig. 2 and 3). Through the incision, the whitish-colored capsule of the tonsil is revealed, which is then separated from the peritonsillar fat tissue partly by blunt means (with an elevator) and partly by scissors from all sides, as well as from the posterior pillar to such an extent that it is possible to place a wire tonsilotomy loop of Bruenings around its base, with the help of which it is removed. Postoperative treatment and complications are the same as in tonsillotomy. After partial or even complete removal of the tonsils, almost complete regeneration sometimes occurs soon due to the regenerative ability of lymphoid tissue through the transformation of scar connective tissue into reticular tissue (Dietrich) or due to the growth of lymphadenoid tissue of the tongue root, which can occupy the niche of the tonsil (Norsk). Such a tonsil usually has a smooth surface devoid of crypts and can be easily removed with a Hartmann tonsillotomy. - Tuberculosis, syphilis, tumors of the tonsil - see Pharynx. Cystic formations. As a result of acute tonsillitis, the opening of the crypts may become occluded, in which the contents (mucus, epithelium, lymphocytes, microorganisms and their decay products) are retained. The accumulated masses, finding no outlet to the outside, form the so-called retention cyst. Sometimes existing for an indefinite time, they cause almost no subjective complaints. Objectively, they appear as yellowish, translucent, slightly elevated areas above the surface of the tonsil, ranging in size from a pinhead to a pea; inflammatory phenomena are absent in their vicinity. - Treatment. Since the cysts are located very superficially, a shallow incision is sufficient to empty the contents. - Tonsil stones form when there is retention in the tonsillar crypts of plugs or pathological secretions, which become impregnated with lime salts. Their size varies greatly - from small stones to voluminous concretions (18-24 g). They are rare and occur only in adults. Usually, the stone causes inflammatory irritation in the surrounding tissue, sometimes with suppuration forming a fistulous tract. - Treatment: widening of the fistulous tract by incision and extraction of the stone with forceps. - Foreign bodies. The tonsil and the adjacent lateral wall of the esophagus are the place where foreign bodies most often get stuck. In the tonsil, only small pointed objects almost exclusively get in: bones (especially fish bones), grain awns, bristles, needles, splinters, etc. Often they do not cause noticeable disturbances. The most distressing symptoms are a painful sensation in the neck and pain when swallowing. The diagnosis presents no difficulty in cases where the foreign body is accessible to direct inspection per os. If the foreign body is deeply embedded in the tonsil tissue, it is necessary to resort to digital examination. Among the complications, abscesses have been observed, rarely general septic phenomena. Treatment: extraction with forceps; if an abscess forms - its immediate incision. - Processes of rheumatic granuloma of Graff in the peritonsillar tissue are manifested by the development of granulomas (see Rheumatism). The formation of bone and cartilage in the tonsil and peritonsillar tissue belongs to developmental anomalies and is due to an excessively long styloid process, which can press into the tonsil or in rare cases into the anterior palatine arch and thereby cause difficulty in swallowing and pain (von Eicken).
Figure 2. Incision through the anterior pillar.
Figure 3. Separation of the tonsil along with the capsule. fossa supratonsillaris
Amygdalus communis: 1 - branch with flowers; 2 - branch with fruits; 3 - nut. processes of the upper airways in leukemia, Monatsschr. f. Ohrenheilk., B. XLVII, H. 7, 1913; Schlemmer F., Anatomical, experimental and clinical studies on the tonsillar problem, ibid., B. LV, H. 2, 1921. See also lit. k art. -Pharynx. K. Orleans.
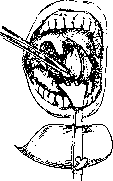


Related articles
Mentioned in
Cite this page
“Tonsil Pharyngeal.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/tonsil-pharyngeal/