Electrocoagulation
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia discusses electrocoagulation as a method of destroying pathological tissue using a diathermic current, particularly focusing on its application in urology for treating bladder papillomas, urethral tumors, and other conditions.
Encyclopedia article (1928–1936)
ELECTROCOAGULATION (from electro and Latin coagulatio - curdling), a treatment method by which the destruction of pathological tissue is achieved using an electric, more correctly a diathermic current. During electrocoagulation, a sufficiently high temperature develops at the end of the electrode, under the influence of which the corresponding tissue is welded. Therefore, it is more correct to call electrocoagulation thermocoagulation. In urology, electrocoagulation is most often used in the endovesical treatment of bladder papillomas. This method was proposed in 1913 by the American physician Beer instead of other, less perfect methods of burning tumors with a galvanocautery or cutting off the tumor with a loop, and is currently generally accepted (see figure). Electrocoagulation requires a
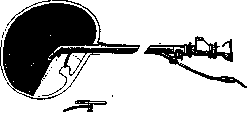
diathermic apparatus, a thin electrode of the caliber of a ureteral catheter introduced into the bladder through a catheterizing cystoscope, and a 12x12 cm lead plate placed under the patient's pelvis. The plate and the electrode are connected by wires to the diathermic apparatus, the end of the electrode is brought through the cystoscope to the surface of the tumor, and the diathermic apparatus is turned on. At the same time, the end of the electrode begins to heat up, and under the influence of the developing heat, the protein of the tumor cells coagulates. By placing the end of the electrode with small pauses for 10-30 seconds on different areas of a small or medium-sized tumor, it is possible to completely destroy the latter in one or several sessions with intervals of 5-7 days. Special attention should be paid, in order to avoid recurrence, to the electrocoagulation of the tumor stalk. With extensive papillomatosis of the bladder or when the location of the tumor is inaccessible for bringing the electrode, electrocoagulation can be performed on the bladder opened by high section.
Electrocoagulation is also used in some other urological diseases - in ureterocele, in the entrapment of a stone in the mouth of the ureter, in a simple ulcer of the bladder, in tuberculous ulcers of the latter that do not respond to conventional treatment, in small fistulas of the bladder, in partial urinary incontinence in women as a result of sphincter weakness, in the so-called bladder barrier in men, etc. The technique of electrocoagulation is relatively simple and easy to master for anyone familiar with cystoscopy and ureteral catheterization. Electrocoagulation can be performed either under local anesthesia of the bladder (preliminary introduction of a 2% alipain solution into the bladder) or without anesthesia. In most cases, electrocoagulation causes an insignificant reaction from the bladder and can therefore be performed on an outpatient basis. Much less frequently, electrocoagulation is used for papillomas or angiomas of the urethra. In these diseases, electrocoagulation is performed through a urethroscope. Relatively frequent papillomatous growths at the external opening of the urethra in women are also successfully destroyed using electrocoagulation.
Related articles
Mentioned in
Cite this page
“Electrocoagulation.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/electrocoagulation/