BACTERIURIA
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Bacteriuria is characterized by the presence of microorganisms in freshly voided urine without causing inflammatory reactions in the urinary tract. It can be true (bacteria multiply in urine) or false (bacteria pass through without multiplying), with various predisposing factors and modes of infection.
Encyclopedia article (1928–1936)
BACTERIURIA (syn. bacteriuria, bacilluria), is characterized by the presence of a greater or lesser quantity of microorganisms in freshly voided urine, where their presence does not cause any inflammatory reaction in the walls of the urinary tract. In true bacteriuria, bacteria multiply and develop in the urine as in a nutrient medium. False bacteriuria, in contrast to true bacteriuria, is characterized by the simple passage of microorganisms through the kidneys into the urine from the blood (without their multiplication) and often occurs during infectious fevers (typhoid, influenza, diphtheria, postpartum infections, osteomyelitis, erysipelas, etc.). This also includes the excretion of Koch's bacilli with urine in tuberculosis of internal organs. This tuberculous bacilluria should be differentiated from initial forms of kidney tuberculosis, based on the presence of protein and leukocytes in the urine in the latter. The most diverse microorganisms can develop in urine, most often the colon bacillus, then staphylococcus, sarcina, micrococci, leptothrix; streptococcus and various types of diplococci have been found repeatedly, with the basis of bacteriuria being either one bacterial form or a combination of several (mixed infection). Age and sex do not influence predisposition to bacteriuria. Predisposing factors are conditions leading to stagnation and hyperemia in the urinary organs: constipation, pregnancy, uterine deviations, prostate hypertrophy, urethral strictures, etc. The routes of bacterial penetration vary: descending, ascending, hematogenous, and lymphogenous. The ascending route of urinary tract infection is more common in women than in men, due to the shortness of the urethra in the former and the easier possibility of transferring bacteria from the anus to the urethral opening. That such a method of penetration of microbes is generally possible and that mechanical influences, such as sexual intercourse, play a role, is indicated, for example, by the frequency of cases of so-called defloration pyelitis after the first coitus. Instrument-induced infection (lack of asepsis or technique) should also be attributed to the ascending route of urinary tract infection. Furthermore, bacteria can infect the urine (bacteriurie par contact direct) from foci of inflammation in the prostate, seminal vesicles or posterior urethral glands, which can be easily proven by obtaining sterile urine by catheter directly from the bladder. It has been experimentally proven that bacteria injected into a vein are distributed throughout the body, enter the kidneys and are then excreted with urine. In the presence of closed bacterial foci somewhere in the body, similar excretion of microbes can also occur. It was previously believed that this could only occur in the presence of mechanical damage to the kidney; recent research shows that even a healthy kidney is permeable to bacteria. Cases have been described of the excretion of typhoid bacilli with urine for many (8-9) years after recovering from typhoid fever. The hematogenous descending route is more common in false than in true bacteriuria. The works of Bauereisen have proven the presence of lymphatic anastomoses between the large intestine and the ureters and kidney. Hence it is understandable how bacteriuria can arise in all kinds of intestinal disorders: by analogy with the frequency of pyelitis and cystitis in appendicitis, which is almost always accompanied by constipation (due to treatment with opium), the possibility of easy development of bacteriuria by the lymphatic route in cases of stagnation and inflammatory processes in the colon should be recognized. The question of the permeability of the healthy intestinal wall to bacteria is a resolved issue. In Posner's experiments with rabbits, which he obstructed at the anus, coprostasis caused the appearance of bacteria in the urine after 18 hours. In these cases, stasis could be accompanied by enhanced intestinal peristalsis, while clinical practice constantly gives examples of bacteriuria after not only mechanical but also paralytic obstruction. Lymphogenous bacteriuria is the most common clinical form. Some authors consider the symptom complex of bacteriuria as a vicarious, protective adaptation of the body, seeking to unload the intestine from the huge number of bacteria and reduce intestinal auto-intoxication. To the present day, the question of why inflammation does not develop in the bladder when bacteria are present in the urine has not been resolved. It is assumed that the development of cystitis is hindered by a number of factors, such as the low virulence of bacteria, the immune state of the organism, and the composition of the urine itself. - The course of bacteriuria depends on the

FIG. 1.
cause producing it. In the presence of stagnation in the urinary tract (in the renal pelvis or bladder), bacteriuria easily passes into cystitis or pyelitis. With a change in conditions, bacteria again seem to lose their virulence, and bacteriuria exists with intermissions (often for many years). The objective symptoms encountered in bacteriuria are frequent urges and cloudy urine, which with difficulty forms sediment, or does not form sediment either on standing or on centrifugation. Urine in bacteriuria slightly opalesces, takes on a greenish tint and resembles slightly turbid water. If bacteriuria is caused by the colon bacillus, the urine has a characteristic, unpleasant odor and is acidic; in other cases it is alkaline. In the latter cases, the turbidity also depends on the precipitated salts, and their quantity can be greatly increased, so that we are dealing with both phosphaturia and carbonaturia at the same time. The microscope sometimes reveals an enormous quantity of microbes. The number of urinations is usually increased (from 9 to 12 times), but without pain. Bacteriuria is not accompanied by any general symptoms. The ease of diagnosing bacteriuria is clear from what has been said. Painless, cloudy pollakiuria should lead to microscopic examination of the urine: the presence of bacteria, in the absence of inflammatory elements - leukocytes - clarifies the matter. The accompanying illustrations show microscopic pictures of urine sediment in the pure form of bacteriuria (see Figure 1) and in the mixed form (see Figure 2). The question of whether bacteria are excreted with urine from the renal pelvis or from the bladder can be decided either by catheterization of the ureters or by the method of Janet. He collects urine by catheter onto an agar medium, then washes out the bladder with sterile water and after X hours collects urine again: if the second portion contains as many microbes as the first, there is renal bacteriuria. - The prognosis of bacteriuria quoad vitam is good, quoad sanationem is doubtful. Treatment of bacteriuria. The general condition is abundant drinking; in the presence of accompanying phosphaturia - the prescription of mineral waters and diet. Autovaccine in bacteriuria is theoretically not indicated, and practically has no effect. Cases of hematogenous infection are so rare that they need not be dwelt upon in therapy. Cases of instrument-induced infection require preventive measures; cases of transition from the prostate or posterior urethral glands require treatment of the latter. Cases of ascending infection, maintained by unfavorable conditions for urine outflow, require improvement of outflow. The most difficult task is the treatment of lymphogenous bacteriuria. The failure of all proposed methods of internal medicinal treatment of this most common form of bacteriuria, as well as local treatment (by washing the bladder and renal pelvis with various solutions in different concentrations, which is associated with the possibility of traumatizing the mucous membrane with a catheter and its inevitable infection with a medium containing bacteria), forces one to think of a different approach to the treatment of bacteriuria. Undoubtedly, in these cases it is more rational to treat not bacteriuria, but the intestine. By eliminating constipation, the absorption and entry of bacteria from the intestine into the lymphatic system and from there into the urine are also eliminated. - Prevention is evident from all that has been said. It is necessary to particularly emphasize the need for a number of preventive measures in typhoid fever, in which in 78% of cases the causative microorganism of the disease is found in the urine. Personnel caring for such patients must take the same precautions with urine as with feces.
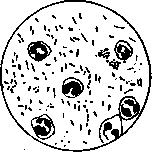
Figure 2.
rare that they need not be dwelt upon in therapy. Cases of instrument-induced infection require preventive measures; cases of transition from the prostate or posterior urethral glands require treatment of the latter. Cases of ascending infection, maintained by unfavorable conditions for urine outflow, require improvement of outflow. The most difficult task is the treatment of lymphogenous bacteriuria. The failure of all proposed methods of internal medicinal treatment of this most common form of bacteriuria, as well as local treatment (by washing the bladder and renal pelvis with various solutions in different concentrations, which is associated with the possibility of traumatizing the mucous membrane with a catheter and its inevitable infection with a medium containing bacteria), forces one to think of a different approach to the treatment of bacteriuria. Undoubtedly, in these cases it is more rational to treat not bacteriuria, but the intestine. By eliminating constipation, the absorption and entry of bacteria from the intestine into the lymphatic system and from there into the urine are also eliminated. - Prevention is evident from all that has been said. It is necessary to particularly emphasize the need for a number of preventive measures in typhoid fever, in which in 78% of cases the causative microorganism of the disease is found in the urine. Personnel caring for such patients must take the same precautions with urine as with feces.
Related articles
Mentioned in
Cite this page
“BACTERIURIA.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/bacteriuria/