Tetanus
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Tetanus is an infectious disease caused by the Nicolaus bacillus. The article details its historical discovery, etiology, epidemiology, pathophysiology, and clinical characteristics as understood in the 1920s-1930s.
Encyclopedia article (1928–1936)
TETANUS (tetanus), an infectious disease caused by the Nicolaus bacillus. Tetanus has been known since ancient times, but it was only in 1884 that Nicolaus established that garden soil, injected under the skin of mice, causes in them a typical case of tetanus. Nicolaus also identified and described in these mice, at the site of injection, special thin bacilli with thickenings at the ends. Two years later, Rosenbach discovered the same microbes in the discharge of a wound in a human tetanus patient, and in 1889 Kitasato obtained a pure culture of the same microbes and finally proved their etiological role in the development of tetanus. The tetanus bacillus is a spore-forming anaerobe (its properties see Microorganisms, cultivation of microbes, Anaerobes). The optimum growth temperature for the Nicolaus bacillus is 37°C. Spores withstand exposure to flowing steam for up to 5 minutes, at 80°C for an hour. Their resistance to antiseptic substances is equally significant: spores die in a 5% carbolic acid solution in 15 minutes, in 1:1,000 sublimate in 3 hours. The tetanus bacilli are very widespread, especially in soil near human dwellings and domestic livestock (in rural conditions), as well as on cultivated garden and garden land, in street dust, etc. Bacilli were found in horse feces in 90% (Lucas), in cattle 100% (Joseph), in humans in 36% (Buzelo, Sonnenburg). However, despite such widespread distribution of the tetanus pathogen, it occurs not as frequently as one might expect. According to data from German insurance institutions, 1 case of tetanus occurs per 10,195 accidents, 1 fatal case of tetanus per 48,430 accidents, or per 165 deaths from accidents. Man is considered highly susceptible to tetanus and is surpassed only by the horse. Among laboratory animals, mice and guinea pigs are particularly susceptible, rabbits less so. Among predisposing factors, thymico lymphaticus is noted, but according to Saegesser, among 21 deaths from tetanus, he found signs of this condition in only 3 cases and therefore does not share this opinion. Monckeberg noted the importance of changes in the thyroid gland. The presence of domestic livestock, despite the almost constant detection of tetanus bacilli in their excrements, is not decisive in the spread of tetanus. Thus, in the Swiss Jura, Engadine, Wales, despite the population being engaged in livestock farming, tetanus is very rare. Essentially, tetanus is observed almost everywhere, the difference lies only in the quantity. During wartime, tetanus was observed from 0.14% to 1% (Faneman, Berezne-govsky, Proskurin). Pribram, Kummell, Simon give almost the same fluctuations for the German army (from 0.37% to 1%). Diseases were particularly frequently observed with severe injuries with muscle crushing. The mortality rate from tetanus varies within wide limits depending on the form of the disease, the use of serum, and other factors. According to old data by Jacob, in acute tetanus the mortality rate was 85.7%, in subacute 34.9% (1906). In 1913 (Permin) the overall mortality rate was 62.1%. In the English army in 1914 the mortality rate was 57.7%, in 1918 - 28%, and in 1917 15%. According to the collective military statistics of Striecker, the mortality rate was 64.5%. According to French data (Berard), at the beginning of the war the mortality rate was 68%, at the end - 46%. The dependence of mortality on the duration of the incubation period is quite pronounced; with an incubation period of 1 week the mortality rate is 75.5%, 2 weeks - 49.4%, 3 weeks - 31.9%, and 4 weeks and more - 18.78%. - Due to the location of the infection in the soil, tetanus is a summer disease. The largest number falls on the months of June and July, followed by May and August, by winter time the cases almost subside (Saegesser). The frequency of the disease also depends on the snow cover of the ground. The source of infection in most cases is a wound. Sometimes the injury itself is very minor and escapes the attention of the victim. Cases have been described of infection penetrating through tongue bites in epileptics, infection through leg ulcers, after operations on the nasal mucosa, etc. Sometimes the initial minor injury has already healed by the onset of the disease. Postoperative cases of tetanus are associated with insufficient sterilization of catgut. Such cases were collected by Rusler, then there are individual reports from a number of authors. Of 39 cases of peacetime tetanus in Saegesser, 35 cases were from rural areas and 4 urban. Of these patients, 6 received injuries while walking barefoot, 8 - from street accidents, 7 - from wooden splinters, 8 - from damage by agricultural machines and 7 - by tools. During wartime, tetanus complicates all kinds of injuries, but primarily, as indicated, injuries with a large area of damage, especially in positional warfare. As for the connection with working conditions, tetanus is most often observed in agricultural work. In general, contamination of a wound with soil should always be considered as a factor causing the danger of tetanus infection. Tetanus bacilli do not spread beyond the area of the wound, and they are not found further than the nearest lymphatic pathways. The disease itself is caused by the absorption and poisoning by a special tetanus toxin, a product of the vital activity of microorganisms. According to Ehrlich and Madsen, tetanus toxin consists of tetanospasmin, whose action causes convulsions, and tetanolysin, which has the ability to dissolve red blood cells. The spread of the toxin from its place of formation in the body, on the basis of a number of studies (Brunner, Marie, Morax, Meyer and Ransom, Lexer), occurs along the axial cylinders of motor nerves. Sawamura and Permin note the spread of the toxin also through the blood vessels. The spread of the toxin along sensory nerves is not observed; it is retained in the spinal ganglia. When the toxin is injected into the posterior roots, a special clinical picture of pains strictly localized at the level of the corresponding segments is obtained (tetanus dolorosus). The endings of motor nerves and then their trunks are affected even when the toxin is administered intravenously, then the toxin is concentrated mainly in the motor subcortical centers of the brain, especially in the nucleus of the trigeminal nerve, as well as in the spinal cord. The clinical picture of tetanus varies somewhat depending on the route of administration of the toxin, which is apparently related to the deposition of the toxin in the central nervous system. With intracerebral administration, strong motor excitement and epileptoid convulsive seizures occur due to predominantly cortical binding of the poison. According to Mendel, the special selectivity of individual parts of the nervous system for the tetanus poison is a consequence of the different adsorptive capacity of different cellular elements. The blood-brain barrier allows some coarsely dispersed colloids to pass through, while finely dispersed and semi-colloids are retained. The affinity of tetanus toxin for certain brain nuclei is explained by the peculiarities of the physico-chemical structure of the surface of groups of these cells. When the toxin is administered intracerebrally, it enters under increased pressure and is able to penetrate and bind with those cells that, under normal conditions of toxin distribution, due to lower adsorptive capacity, do not absorb it (Saegesser).- In experiments on animals, intravenous administration of the toxin leads to a violent picture of generalized tetanus; a similar picture is obtained when the poison is injected into the abdominal cavity. Although all this shows the possibility of the participation of the vascular system in the spread of tetanus poison, the fact that the clinical picture never develops as quickly as it would if the blood route were indeed the path of spread shows that in practice this path has at best secondary importance. The site of infection does not affect the duration of the incubation period. The amount of toxin and the severity of the infection are important in this respect, but still the amount of poison must be very sharply increased to significantly shorten the incubation period. Courmont and Doyn, when administering 30,000 times the lethal dose of poison to guinea pigs, could shorten the incubation period by 2 hours, but still some incubation period always precedes the development of the clinical picture. On autopsy of those who died from tetanus, signs of death from asphyxia are usually found; pronounced cadaveric rigidity, pulmonary edema, small hemorrhages under the serous membranes, liquid tar-like blood are noted. The presence of the toxin can also be established in the blood. In deaths in chronic cases of tetanus, complications, often from the lungs, usually come to the forefront. In humans, the incubation period usually lasts 1-2 weeks, with 45% of cases falling in the second week, 35% in the first week, and 20% at later dates (up to 2 months), sharply decreasing after the fourth week. Very late cases of the disease are explained by late wound infection. The duration of incubation depends on the accumulation and absorption of the toxin from the wound; shorter incubation periods correspond to a more severe clinical course.
The above data on mortality rates depending on the duration of the incubation period also confirm the stated position. A characteristic feature of the clinical picture of T. is contractions of the musculature. The disease often begins with tonic spasms of the masticatory muscles and trismus (lockjaw). These spasms are sometimes replaced by clonic twitchings. Sometimes similar contractions are observed in the musculature of the wound area. In acute cases, the spasms quickly spread to the facial and neck muscles, followed by clonic spasms of the back, abdomen, and extremities. As a result of the contraction of facial muscles, a characteristic expression of the face results, long noted by clinicians and given a special name, namely risus sardonicus, as if expressing contemptuous laughter, as well as generally facies tetanica with the formation of deep wrinkles on the forehead and cheeks. The spasms follow one another; due to the sharply increased excitability of the musculature, the slightest provocations (loud sound, dropping of any object on the floor, light touch, etc.) are sufficient to renew a subsiding spasm with renewed force. Spasms of the extensors of the back cause strong backward bending of the head (opisthotonus) and inability to bend the head. Even outside of spasms, the musculature remains in a state of tension. Less frequently, predominant contractions of individual muscle groups can be noted, e.g., of the neck, back (pleurothotonus) or extremities. If the respiratory muscles and diaphragm are quickly involved in spasms, death from asphyxia occurs within the first day from the onset of the disease, but even in less acute cases, the involvement of respiratory muscles constantly threatens death from the same cause. The act of breathing is sharply disturbed, ventilation of the lungs occurs insufficiently, stagnant phenomena develop. Very favorable conditions for the development of aspiration pneumonias are created, which are a not infrequent cause of death. But the fatal outcome can also be caused by edema of the glottis and paralysis of the heart. Usually from the beginning of the disease, temperature rises, its height depending on the degree of development of muscle contractions. With unfavorable course, by the end the temperature reaches very high figures-43-44° and sometimes increases in temperature are noted even immediately after death. Abundant sweating attracts attention. The pulse is accelerated to 120 per minute, protein is often found in the urine. Consciousness is usually preserved until death. Opokin notes the symptom described by other authors of 'circus smell' from patients when several patients are gathered in one ward. Even in favorable cases of T., the clinical picture of the disease rarely begins to weaken before a week; in such cases, convulsive seizures become rarer and weaker, the tension of the musculature also weakens, breathing becomes freer, trismus weakens and then disappears, although swallowing remains difficult for some time, it becomes possible to bend the head forward, the temperature subsides. Finally, recovery occurs. However, the danger of death is not excluded even in the stage of subsidence of disease symptoms, especially from the addition of pneumonia, therefore the prognosis of recovery should always be made with caution. In the mildest cases, tetanus immediately takes a chronic course; in it the entire picture is expressed much more weakly, the spasms do not immediately capture a large number of muscles and are replaced by temporary relaxation. The respiratory muscles are weakly affected, trismus is not sharply expressed, opening of the mouth is possible, swallowing nevertheless usually suffers. The temperature does not rise high. Still, the course of such cases until complete recovery is sometimes quite lengthy (up to 3 months). Recovery is observed with the gradual weakening of all symptoms of the disease. The course of the wound-the entrance gate of infection-does not correspond to the clinical picture of the disease T. In view of the fact that the bacillus of T. does not belong to the pus-forming microbes, small injuries can heal by first intention; suppuration, development of granulations and in general the course of healing of the wound depend on the accompanying infection with pus-forming microbes. In the brightly developed stage of the disease, the diagnosis of T. presents no difficulty, but since the success of treatment stands in direct dependence on the earliest possible beginning of treatment, until in the central nervous system a lethal amount of poison has already become bound, as this is especially emphasized by Bucello, it is important to recognize T. as early as possible, i.e., before the development of typical convulsive seizures and trismus. As such early symptoms of tetanus Bucello notes: 1) pulling and twitching pains in the area of the musculature surrounding the wound, and sometimes in the entire extremity, 2) profuse sweating, not corresponding to the temperature and other phenomena of the disease. Zegesser adds to this as an early symptom pain in the back. The most effective means of early recognition would be the determination of the tetanus bacillus in the wound secretion, however in the early stages after injury, i.e., in the incubation period, it usually is not possible to detect bacilli. Zegesser recommends making a culture of the wound secretion. Even earlier Bucello proposed to inoculate the discharge of a suspicious wound into a guinea pig or white mouse, whereby after 12-24 hours a diagnosis of T. can be made. However, the following data of Zegesser show that even by this method it is not always possible to make an early diagnosis. Indeed, out of 26 cases with incubation up to 10 days, it was possible to prove the presence of the causative agent in the smear and culture in only 4 cases and 11 times by means of the animal experiment. In 16 cases with fatal outcome, culture succeeded in 5 cases, and the animal experiment-8 times. The following clinical forms of T are distinguished: Rose distinguished 4 forms of T: 1) t. vehemens-rapid course of symptoms, 2) t. lentus-chronic form, 3) t. completus-clearly expressed picture and 4) t. incompletus-atypical course. Bucello also distinguishes 4 forms, mainly from the point of view of prognosis: 1) very severe cases with incubation from 2 to 7 days; 2) severe cases with incubation from 5 to 7 days; 3) cases of medium severity with incubation 2-3 weeks and 4) mild cases with incubation over 3 weeks.-Tetanus neonatorum, T. of newborns (see below).-Tetanus puerperalis, T. in the postpartum period. The entrance gates of infection are the mucous membrane of the uterus and birth canal. It is observed both after childbirth and in artificial abortion. The course of the disease is severe in the presence of a stormy typical picture of T.-Tetanus cephalicus, cephalic T., develops when the toxin penetrates into the area of one of the cranial nerves. In severe cases, symptoms of spasms of the pharyngeal muscles and glottis predominate; the picture of the disease resembles the picture of rabies, why it also has the name t. hidrophobicus (Rose). The picture of the disease includes spasms of the facial muscles and then their paralysis (p. facialis). Depending on this, Rose distinguishes t. facialis and t. paralyticus. Death occurs either from asphyxia or from paralysis of the heart.-Tetanus traumaticus, T., associated with injury, was opposed to idiopathic or rheumatic T. (t. idiopathicus, t. rheumaticus), but this division is unjustified, since in the latter entrance gates undoubtedly exist, but were not noticed due to their insignificance (e.g., scratch).-Local T. represents a limited lesion of the musculature, localized on the injured extremity or on the dorsal and abdominal muscles. In the latter case, the extremities remain free from lesions of the musculature. The disease proceeds more favorably than the general lesion. However, local T. is relatively rare: according to the statistics of Kolesnitsky, Kossak and Rokhlin-1 case in 343. With lesions of the extremities, 2 types are distinguished: monoplegic, when the entire injured extremity is affected, and purely local, when the lesion is limited only to the area of the wound. Fatal cases have also been described in local T. In local T., trismus is never observed.-Ascending T. differs in that the muscle contractions begin from the injured area, but unlike local T., the spasms spread to more distant areas, and trismus also joins. Prevention and treatment of T. are based on the use of specific antitetanus serum (see Sera). In 1891, Behring first reported on successful immunization in horses. According to the new international nomenclature (Zegesser), the preventive dose is 2,500 units, the therapeutic dose is 12,500. Sera of the Institute of experimental med.-preventive 1,500 units and therapeutic 3,000. The preventive significance of serum after extensive experience of the imperialist war is beyond doubt: by systematic injection of serum to the wounded, it was possible to significantly reduce, almost stop the disease T. Thus, according to Pribram, the percentage of T. disease decreased thanks to serum from 1.4 to 0.16. The action of serum continues for 10-12 days and in doubtful cases the injection can be repeated. The injection of serum is not an absolute guarantee against tetanus. There are cases even with fatal outcome despite preventive administration of serum (see below).
When introducing serum, one must keep in mind the possibility of anaphylactic shock and neurogenic anaphylaxis (see), as well as serum sickness (see). Prevention of T. was carried out by Ramon and Zoeller in the form of active immunization. Piorkowski reported on successful active immunization of mice as early as 1915. By means of fractional heating of broth culture of T., it is possible to obtain an asporogenous race, which is killed at 110°, dried, and obtained in the form of a powder. When sprinkled on a wound or injected under the skin of mice, such a powder protects against T. The same goal is achieved by the injection of a filtrate after killing the broth culture. This method has the advantage over serum in that it is free from the danger of anaphylaxis. Ramon and Zoeller proposed a method which they called vaccination against T.—apparently the introduction of a formalin-killed culture of bacilli under the name of anatoxin. They introduce 1 cm3, after 4 weeks 2 cm3, and after another 8 days 3 cm3; the immunity obtained in this way is, according to their data, very prolonged, possibly for a lifetime. Anatoxin is commercially available in Germany, however, observation and the number of vaccinations are too small for conclusions. Be that as it may, the introduction of prophylactic serum against T. is considered in our Union as a necessary additional measure in the treatment of a wound contaminated with earth, especially if it is a wound with a large area of damage and was accompanied by the presence of foreign bodies in it. Instructions issued in this respect are mandatory for on-duty physicians in reception rooms of medical institutions and other similar points of medical care where primary wound treatment is carried out. Both prevention and treatment with specific serum for T. is fully scientifically and experimentally substantiated, but in practice, the introduction of serum does not always prevent the development of the disease, all the more so when it is used for treatment, the outcome of the disease is by no means guaranteed. This occurs because, in essence, the use of serum does not achieve treatment of the patient in the direct sense, but only his protection from those portions of the poison that have not yet been bound to the central nervous system, whereas the antitoxin is unable to detach the bound poison. According to experimental data (Gottlieb and Freund, Gossmann), the toxin can only be neutralized in the wound, in the blood and lymphatic pathways, in the cerebrospinal fluid, and in the motor nerves. According to Permin, the toxin adsorbed by organs and motor nerves is already inaccessible to the antitoxin introduced into the blood, however, by means of endoneural and intraspinal introduction of antitoxin, its further progression can be delayed. Thus, the task of serum treatment lies not in neutralizing all the poison that has already entered the body, but in protecting the central nervous system from new portions of the poison. Hence, according to Kreuter, there is a clear indication for the use of serum in every case of T. Nevertheless, if death occurs, this only means that the introduction of serum was delayed and that the amount of bound poison reached a lethal dose. Therefore, it is important to use serum as early as possible. The practice of using serum shows that in most cases its introduction is already late and a lethal amount of poison manages to bind during the incubation period. Nevertheless, even in military cases, where treatment is carried out under less favorable conditions, the use of serum, based on large statistics, reduces the mortality of tetanus patients by 10% (Opokin). In the hands of individual authors, modern treatment of T., including the use of serum, gives much better results. Thus, according to Zegesser, the overall mortality of T. decreased from the previous 80% to 20%, and for acute cases (incubation up to 10 days) 30-40%. Serum can be administered to the patient subcutaneously, intravenously, endoneurally, intralumbally, and intracranially. Zegesser subjected all these routes to detailed analysis; the endoneural route has not found application due to technical considerations, it can be used in amputations. The perineural route is in essence little different from the intramuscular one. The intracranial route in the form of introducing serum into each hemisphere (Roux and Borrel), into the lateral ventricle and subdurally also appears technically difficult, subdural administration gives almost the same results as administration through lumbar puncture. Subcutaneous creates a kind of depot of serum, from which absorption occurs over a long time, but slowly. Intramuscular is evaluated higher in results, even better results are given by intravenous, then intraspinal (lumbar) route, but practically the most important and valuable should be considered the combined administration of serum intravenously and into the lumbar part of the spinal canal. The amount of serum administered should also be significant, at least 500 cm3 and up to 1,500 cm3 and more. The need for large doses is justified clinically and experimentally. The subcutaneous and intramuscular methods of serum administration should be tested especially at the beginning of treatment in the area of the wound. In 1925, Dufour drew attention to the favorable effect of chloroform anesthesia on the course of T.; this method was called 'chloroformization' of the patient. Dufour believes that chloroform, acting on the cells of the central nervous system, detaches the T. poison and makes it possible for it to bind with the serum antitoxin, therefore 'chloroformization' is understood as part of serum treatment, all the more so that outside of anesthesia, spinal puncture due to muscle contraction can be carried out only with great difficulty, and sometimes it is impossible. The use of chloroform in T. is a special case of the use of narcotic substances, and the use of the latter plays a very important role in the treatment of T. With the help of serotherapy alone, the cure of severe cases of T. is doubtful, and hence the extremely important role that symptomatic, in particular narcotic, substances play in the treatment of T. is clear. But first, it is necessary to note the general measures for creating proper conditions for the treatment of T. patients and care for them. Every tetanus patient should be isolated. This requirement may encounter difficulties only in military conditions. The isolation should be such that no sharp noises reach the ward; there should also be no sharp light irritations and even smells. The patient should be under constant observation by specially instructed personnel. Impeccable general hygienic conditions should be ensured, attentive and reasonable care down to the smallest details. Particular attention should be paid to quenching thirst, food intake, and mouth care. The possibility of injury to the patient during convulsions (cases of dislocations, fractures, muscle ruptures, etc., have been described) should be constantly considered; the use of breakable dishes for feeding and drinking, especially with tips that can be crushed by teeth during jaw contraction, is unacceptable. It is better to use soft tips. All movements and transfers of personnel in the ward should be soft, not abrupt, and silent. Bedding should be easily changeable; at an appropriate temperature, the patient can even be kept without bedding under a light cover. Wound treatment, both in the treatment of T. and especially in prevention, plays an important role. The primary wound treatment accepted at present includes the prevention of any, including tetanus, infection (see Wounds, injuries). In case of the onset of T. symptoms, the wound should be examined again thoroughly and, if necessary, treated. It should be widely opened, all pockets destroyed, blood clots, necrotic areas, and foreign bodies removed. The most favorable conditions for the outflow of discharge should be created. There is no basis to recommend any particular antiseptic; most use iodine, Peruvian balsam, hydrogen peroxide; under suitable conditions, Carrel-Dakin irrigation can be set up. Indications for amputation are based on general considerations; practice has shown that it has little effect on the course of already developed T. Among the measures that have attracted attention in the treatment of T., first place is taken by magnesium sulfate (MgSO4). The basis of the action of MgSO4 is its property to interrupt the conductivity of both sensory and motor nerves (Meltzer and Auer; 1905). In the same year, 1905, Russell, and Murphy even in 1904, proposed to treat T. with the help of anesthetic agents. Blake in 1906 combined both positions and reported on his cure of a case of T. with 7-day incubation using MgSO4. Then this method passed from America to Europe. Solutions of MgSO4 were used subcutaneously, intramuscularly, intravenously, into the rectum, and into the spinal canal by means of lumbar puncture. Due to complications and harmful side effects, the most suitable method of administration is lumbar. Dosage from 2 to 10 cm3 of a 25% solution. Zegesser starts with adults at 3 cm3 of a 25% solution and increases to 6-7 cm3. Lumbar puncture is performed with marked opisthotonus under chloroform anesthesia.
After injection, the patient is placed in a horizontal position with the head elevated. For preparing the solution, crystalline magnesium sulfate (MgSO4) with 7 parts water should be used. Dry, non-crystalline powder of MgSO4 is more difficult to dose due to varying water content. It should be noted that during sterilization the solution may become stronger due to water evaporation. It is therefore better to mark the level of solution in the flask and replenish it with distilled water in case of evaporation. Complications are observed mainly in the form of respiratory disorders with the threat of death from paralysis of respiration. 7 such cases have been described, however in some of them there were obvious technical errors and overdose. For mild disorders, 20-50 cm3 of 5% solution of CaCl2, lobelia, physostigmine, O2 are used. For severe disorders with loss of consciousness—artificial respiration, especially with an apparatus for increased pressure. In addition, urinary retention and in 2 cases a state of excitement of the delirium type, which then passed on its own, have been described. However, all these complications are rare and are fully compensated by the favorable effect of using MgSO4. In children under 10 years of age, the use of the lumbar route of administration of MgSO4 is contraindicated. The best results are obtained with the combination of intravenous serum administration and lumbar administration of MgSO4 solutions. The latter, in addition to its narcotic effect, enhances the effect of the serum by increasing its penetration to the cells of the central nervous system, and possibly also by cleaving off part of the toxin already bound by these cells. In addition to the mentioned means, it is also necessary to use hypnotics, first of all chloral hydrate in the form of an enema. According to the prescription of Zegesser: Rp. Chloral-hydrati 10.0, Mu-cilago Salep ad 250.0, pro klysma 50.0. French authors (Moiroud, Nigay) give chloral hydrate in 3-4 doses per day up to 8-12 g and more. Along with chloral hydrate, Somnifen is used from 80 to 150 drops per os or in an enema. 2-4 ampoules of 2 cm3 intramuscularly or 1-2 ampoules of 5 cm3 intravenously. Furthermore, the same means include morphine, pantopon, potassium bromide, urethane, hedonal. La-wen proposed using for the treatment of T. avvitin.
S. Girgolav. Tetanus of newborns (tetanus neonatorum) is characterized by the fact that the portal of entry of infection is almost always the umbilicus. Here, under conditions of tissue death and decay, the tetanus bacillus finds particularly favorable conditions for its development. Cases of tetanus after circumcision, after injection of insufficiently sterile gelatin have been described. Sex probably plays no role in the incidence of the disease, although some authors (Gerhardt) emphasize the predominance of girls. The primitiveness of living conditions, the absence of asepsis in relation to the umbilical wound play a primary role. Infection is spread by hands contaminated with earth, dust, and sometimes dressings. Thanks to the achievements of hygiene and asepsis, T. is rare in civilized countries, but it is still relatively common in Romania, Italy, in tropical countries where the cause lies in living conditions, finally in villages where childbirth with midwives has not yet been eliminated. In Argentina, 1/3 of all deaths in the first year are due to T., because pregnant women of colored races engage in earthworks until childbirth (Fischl). In some parts of Hungary there is a custom to give birth sitting on bare ground. In Romania in 1904, 10,257 died from T., or almost 1/2 of all children who died before the age of one month (Miron). In the Moscow Educational Home among foundlings there were in 1869 18 cases of T. per 11,140 children, in 1877—7 per 12,719. In the St. Petersburg Educational Home in 1880—8 cases of T. per 8,665 children. Prof. Kisel in the former Olga Hospital observed 14 cases of T. in children over 22 years. Autopsies reveal nothing specific: stagnation and hyperemia of the central nervous system, sometimes hemorrhagic extravasates, especially in the spinal cord. Often purulent processes in the umbilical vessels. Clinic. The incubation period is short. Symptoms usually develop at the end of the 1st week, rarely on the 2nd and 3rd. The onset is with restlessness, crying, difficulty in sucking. Trismus dominates other phenomena (hence the old name 'trismus neonatorum'). Then the spasm spreads to the muscles of the body in descending order. Typical 'attacks' develop as if from an electric discharge. When the respiratory muscles and diaphragm are affected—attacks of cyanosis and suffocation. Zhukovsky observed up to 70 attacks per day. In the intervals between them, the child, usually jaundiced and slightly cyanotic, lies in tetanic stupor: the body in opisthotonus, arms bent at the elbows and pressed to the chest, fists clenched
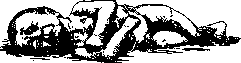
Typical facial expression in tetanus of newborns.
into fists, legs slightly bent and crossed. The face is tearful, characteristically tense (facies tetanica), the forehead is wrinkled, the mouth is closed, with radial folds of the lips and stretched corners (risus sardonicus), sometimes protruding like a trunk. The eyes are tightly closed (see figure), temperature is sometimes normal, more often of intermittent type, in severe forms it reaches 42-43°. The course is sometimes lightning-fast (Finkelstein, 17 hours), more often 2-6 days. Death occurs either during a convulsive attack or later from exhaustion. Along with typical forms, mild abortive forms are observed, where spasms are rare and limited to individual muscle groups. Differential diagnosis with purulent septic meningitis, with brain trauma, with encephalitis is made on the basis of the predominance of trismus, the descending nature of the spread of convulsions, the absence of clonic convulsions and paralyses, and finally (if possible) experimental inoculation of scrapings from the umbilical wound. The prognosis is severe, especially with early onset, rapid development, frequent attacks and high temperature. Large fluctuations in the mortality rate among different authors (Fischl—60, Finkelstein—64, Miller—96.9, Zhukovsky—98%) are explained in part by the possibility of diagnostic errors. Treatment with serum is not very reliable, partly because it is usually administered late, when the toxin is already bound to cells. According to Behring, it should be used no later than 30 hours from the onset of symptoms. 250 units of Behring's antitoxin (1, 2, 3 times) are administered, partly subcutaneously, near the portal of entry, partly intralumbally. American authors (Parrish) administer up to 1,500 and even 3,000 units. Many authors obtained good results from the use of magnesium sulfate along with serum. A reliable means for alleviating severe convulsions remains chloral hydrate up to 3.0 pro die in enemas 3-4 times a day. Luminal 0.015 orally or subcutaneously, veronal 0.075 (Feer). Care has enormous importance. Absolute silence, rest, dim light, possibly rare touches, wrapping in cotton wool, careful nutrition. Frequent feedings should be replaced by the introduction of a probe through the nose 3 times a day. Enemas of 10% glucose and women's milk, drip; artificial respiration and oxygen during suffocation attacks. Prevention consists in strict asepsis of childbirth and subsequent care of the umbilical cord. In the presence of tetanus infection in the environment of the newborn—preventive administration of serum to him.
T. Chebotarskaya. Lit.: Bereznegovsky N., On the treatment of tetanus, Sib. med. zhurn., 1921, № 12; Vvedensky K., Tetanus (General Surgery, ed. by E. Hesse, S. Girgolav and V. Shaak, vol. II, L., 1931); Kolesnitsky A., Kossak L. and Rokhlin S, 343 cases of tetanus, Vrach.-san. izv. Yugo-Zap. fronta, 1916, № 9; Minor V., Robinson I. and Khaim Ts., On the pathological anatomy and pathophysiology of tetanus, Zhurn. dlya usoversh. vrachey, 1927, № 4; Opokin A., Surgery of war field injuries, Tomsk, 1931; Ponomarev A., On the question of the pathogenesis of tetanus and the mechanism of progression of tetanic toxin along the nerve, Arkh. biol. nauk, 1928, № 1; Rubashev S, Prevention and treatment of tetanus, Vrach, delo, 1919, № 24; Fedorov S, Experimental-clinical research on the question of tetanus, M., 1895; Bauer J., Tetanus (Starrkrampt) (Hndb. d. Kinderheilkunde, hrsg. v. M. Pfaundler u. A. Schlossmann, B. II, Lpz., 1923, lit.); Buzello A., Der Wundstarrkrampf beim Menschen, Stuttgart, 1929; Camus J. et Cournay J., Tetanos (Nouveau traité de medecine, sous la dir. de G. Roger, F. Widal et P. Teissier, fasc. 2, P., 1928, lit.); Eisler M., Tetanus (Hndb. d. pathogenen Mikroorganismen, hrsg. v. W. Kolle, R. Kraus u. P. Uhlenhutii, Band IV, Jena-B.-Wien, 1928, lit.); Saegesser M., Der heutige Stand der Tetanusbehandlung unter besonderer Berücksichtigung der Magnesiura-sulfattherapie, Erg. d. Chirurgie. Orthopadie, B. XXVI, 1933; Schittenhelm A., Tetanus (Hndb. d. inneren Medizin, hrsg. v. G. Bergmann u. R. Staehelin, B. I, T. 1, B., 1925, lit.); Sonntag E., Bisherige Erfahrungen über den 'Wundstarrkrampf im jetzigen Kriege, Erg. d. Chir. u. Orthop., B. X, 1918; Sternitzer K., Tetanus (Spezielle Pathologie und Therapie innerer Krankheiten, herausgegeben v. F. Kraus u. Th. Brugsch, B. II, T. 2, Berlin-Wien, 1919, lit.).
Related articles
Mentioned in
Cite this page
“Tetanus.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/tetanus/