DRAINAGE (is used for removing fluids from body cavities,)
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Drainage is a technique used to remove fluids from body cavities, abscesses, and wounds using tubes, gauze strips, or thread bundles. The article describes various drainage methods, materials, and applications in surgical practice during the 1920s-1930s.
Encyclopedia article (1928–1936)
DRAINAGE, is used for removing fluids from body cavities, abscesses, and wounds. For this purpose, tubes made of various materials, gauze strips, and bundles of threads (catgut, silk) are used. Drainage tubes in the treatment of infected wounds were used in very ancient times (Hippocrates, Galen, Paracelsus), but they became especially widespread after Chassaignac (1859) proposed rubber tubes. Previously, metal tubes (silver, copper, tin) were in use. At present, tubes made of red rubber and glass (Fig. 1-a and b) are exclusively used. Glass tubes are sometimes combined with gauze drainage, for which the lumen of the tube is loosely filled with a strip of gauze (Fig. 1-c). Between tubular and gauze drainage stands the cigar-shaped drainage, which consists of a strip of gauze wrapped in rubber fabric (Fig. 1-d). Rubber and glass drainages vary in thickness, from 2 mm to 2 cm in diameter. Side openings (windows) are usually made in the walls of the tubes. Along
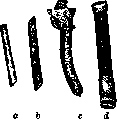
Figure 1.
with ordinary tubes, depending on special purposes and place of application, drainages of various shapes and from various materials are used. Thus, in draining the bile ducts, a T-shaped rubber drainage is sometimes used, with the short horizontal part being inserted into the incision of the duct, choledochus, and the long vertical part being brought out through the wound. For draining individual body cavities with excessive accumulation of fluid in them, various types of internal drainages have been proposed. They are very diverse. Thus, for the purpose of removing fluid from the brain ventricles into the tissue in hydrocephalus, the use of tubes made from a segment of vein (Raug) or a rolled-up plate of the dura mater (Venglovsky) has been proposed. For draining the abdominal cavity, the use of a segment of vein or a bundle of threads that would connect the peritoneal cavity with the preperitoneal tissue was also proposed. Capillary drainage in edemas should be mentioned. These drainages, which are small cannulas with side openings, are inserted into the subcutaneous tissue. The outer end of such a cannula is connected with a rubber tube that is lowered into a vessel for collecting fluid. The absorbable drainages made of decalcified bone proposed by Neuber (1879) did not find widespread use. The use of these drainages was proposed for long-term dressings (plaster) together with absorbable material for sutures. The drainage with gauze strips, introduced into surgical practice by Lister (1891), instead of the previously used rolls of cotton and hemp, became widespread in the treatment of infected wounds. Degreased, unstarched soft gauze has the property of absorbing large amounts of fluid. An essential condition for good absorption is the loose state of the gauze strips. Tightly packed gauze stops absorbing. Absorption also ceases when the ends of the gauze, impregnated with exudate and brought out, dry out. Gauze drainages are used in the form of strips of various sizes. In order not to injure wounds during frequent dressing changes, Mikulicz introduced a special modification of gauze drainage. A square piece of gauze is inserted into the wound, in the center of which a long strong thread is sewn. The place where the thread is attached should be inserted into the deepest part of the wound. The piece of gauze spreads out along the walls of the wound, forming a bag into which the required amount of gauze strips can be inserted. When changing the dressing, only the contents of the bag are changed. Thus, the walls of the wound are not injured. After the wound is cleaned, the bag is pulled out by the thread (Fig. 2). Drainages cause a reaction from the surrounding tissues, consisting in enhanced secretion of lymph in the direction of the drainage. With insufficient vital capacity of the tissues, drainage can cause the formation of necrotic areas nearby; therefore, drainage tubes should not be kept in contact with blood vessels for long, especially in infected tissues, due to the danger of necrosis of the vessel wall with subsequent bleeding. The proximity of drainage tubes to the intestinal wall is also dangerous due to the possibility of its perforation. Therefore, when long-term drainage of the abdominal cavity is necessary, it is advisable to wrap the drainage tubes with strips of gauze, which, due to its pliability, does not lead to necroses so quickly. Drainage is used mainly in purulent accumulations in wounds and body cavities. But one cannot completely refuse the use of drainages even in aseptic wounds, in which drainage tubes are inserted in cases where after wound closure significant transudation can be expected, when there is no certainty in the complete stop of bleeding from the smallest vessels, when there are cavities left in the wound not closed by deep sutures, in which blood or exudate from the surrounding tissues can accumulate. In these cases, drainage is inserted either through the wound or through a separate hole aside from the operative wound and is left for a short time (24-48 hours). In draining purulent accumulations, either gauze strips or drainage tubes are used. With gauze drainage, capillary absorption plays a role; emptying of abscesses through drainage tubes occurs only by the law of gravity. Therefore, drainages should be inserted in the lowest part of the wound to ensure outflow. Drainage of the abdominal cavity requires special mention. The lowest parts of the abdominal cavity, where pus accumulates in the horizontal position of the patient, are the lumbar regions and the pelvis. These areas should be drained with tubes, passing them through corresponding incisions. The female pelvis is drained through the posterior fornix of the vagina, in males - through the pelvic floor in front of the rectum. Drainage of other areas through the anterior abdominal wall is difficult, since the removal of pus is possible only due to capillary absorption, not gravity, and gauze strips quickly become overgrown with adhesions and lose connection with the abdominal cavity. Apparently, more successful than others is drainage with glass tubes with gauze wicks inside, which can be changed as needed. For emptying cavities (in pleural empyemas, in draining urine after high section of the bladder, in draining the bile ducts, etc.), siphon drainage is used. For this, the end of a long rubber tube is inserted into the wound; the rest of the wound is closed with sutures. The other end of the tube is lowered into a vessel with disinfectant fluid. By centrifugal stroking, air is expelled from the tube, the tube fills with pus, which then flows out through the siphon. To prevent the tube from slipping out of the wound and to avoid pain from tension, the tube is tied to the dressing. In recent years, purulent wounds are treated without drainages, especially gauze ones. It is indicated that the insertion of gauze drainages does not accelerate the cleansing of the wound from infection. The constant need to change tampons leads to injury of the wound walls, to destruction of the granulation barrier. When good outflow of exudate is possible after an appropriate incision, healing without gauze tampons proceeds faster. Numerous clinical observations confirm the correctness of these views. Nevertheless, in some cases, drainages have to be used, mainly when deeply located abscesses have difficulty in bringing exudate out due to anatomical conditions; muscle plates, unyielding aponeuroses usually force one to take artificial measures to ensure that the wound passage is passable for purulent exudate.
A. Prokin. Drainage of the uterus—a method of active treatment for local bacterial postpartum diseases in the uterine cavity, developed by Sitsinsky. The author proceeded from the consideration that the infected uterus represents a hollow infected wound. The main requirement in treating such a wound is to create conditions for suction of secretions from the wound outward. The possibility of suction from hollow wounds has been clinically proven in surgery by Mikulich's drainage method. Thus, Sitsinsky sought to treat the affected uterine cavity as any hollow infected wound, eliminating the accumulation of secretions in it and establishing a continuously functioning drainage from the cavity outward. The method consists of the following. First, the uterine cavity is washed with the help of a double glass catheter designed by the author, sequentially with solutions of sublimate 1:3,000 or Kali hypermanganici (19-20°), then with boric acid (47-48°), and finally with pure ethyl alcohol in an amount of 1/3 liter (19-20°). The washing has the task of removing remnants of mucous membrane, particles of the ovum, bacterial and putrefactive products, as well as disinfecting the cavity due to increased osmosis through molecular currents from the walls of the uterus into its cavity. According to Sitsinsky, washing has no actual significance; the main point lies in the constant suction by introducing sterile gauze into the uterine cavity (followed by loose packing of both it and the vagina) and bringing the other end of the gauze outward. This creates conditions for capillary drainage. The latter remains in place for 8-10 hours and is replaced by another only after 12 hours. As a result of such uterine dressing, a drop in temperature, improvement of the pulse and condition of the patient is observed. If unsuccessful, a second dressing can be undertaken. Contraindications to the use of uterine drainage are bacterial processes that have spread beyond the uterus, gonorrheal postpartum endometritis with suspicion of disease of the tubes or ovaries, as well as cases where the visible cervical canal is covered with a grayish-green coating. The method of uterine dressing has not gained particular prevalence in obstetrics and is now almost never used by anyone.
Yu. Gitvlson.
Related articles
Cite this page
“DRAINAGE (is used for removing fluids from body cavities,).” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/drainage-2/