Cornea
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The cornea is the anterior, transparent part of the eye's fibrous coat, making up about one-sixth of its surface. It consists of five layers: epithelium, Bowman's membrane, stroma, Descemet's membrane, and endothelium.
Encyclopedia article (1928–1936)
Cornea, corneal membrane (cornea) represents the anterior, more convex, transparent part of the outer fibrous membrane of the eyeball, occupying about 1/6 of its surface. The boundary between the cornea and sclera is marked as a shallow groove - sulcus sclerae externus. The cornea is as if placed on the eye like a watch glass and has the shape of a meniscus, since its middle is thinner than its edges. Previous figures for corneal thickness - 0.8 mm in the middle and 1.0-1.2 mm at the edges - have recently been disputed based on studies of the cornea with a slit lamp (Koby), and the "actual" thickness of the cornea in the center is determined to be 0.466-0.703 mm, on average 0.583 mm. The radius of curvature of the anterior surface of the cornea averages 7.84 mm (Salzmann), but this figure refers only to the middle, spherically curved third of the cornea, so-called optical zone, while its peripheral parts are noticeably flattened. Thus, the radii of curvature of the cornea in its peripheral parts gradually increase. In addition, the radii in different meridians of the cornea may be different, most often the radius in the vertical meridian is shorter than the radius in the horizontal meridian, consequently the refractive power of the vertical meridian is greater than the horizontal; hence astigmatism arises. According to some recent measurements of the cornea (Berg), its horizontal meridian shows fairly uniform curvature, while the vertical gives greater irregularities, and at the boundary between the middle and upper thirds of it, a line corresponding to the position of the upper eyelid edge with normally open palpebral fissure can sometimes be noted. Berg explains such curvature of the cornea with relative myopic setting by the pressure of the eyelid on the eye. The curvature of the posterior surface of the cornea is considered smaller and spherically curved; its radius is about 7.0 mm (Salzmann) - 6.22 mm (Tscheming). When viewed from the front, the cornea appears in shape approaching an ellipse with a longer horizontal axis - on average 11.6 mm (11.65 in men and 11.54 mm in women) and a shorter vertical one - on average 1 mm shorter. This is explained by the fact that in its posterior layers, the cornea extends into the sclera at the periphery more than in the anterior layers, and the resulting overlapping of the sclera onto the cornea is more pronounced above and below than on the sides. When viewed from behind, the cornea appears round with a diameter approximately equal to the long diameter of its anterior surface. If a plane is drawn through the outer edge of the cornea, it is called the base of the cornea, and the distance from the middle of this plane to the center of the cornea is called the height of the cornea; on average it is 2.6 mm and depends not only on the curvature of the cornea itself, but also on its size. It is believed that the cornea completes its growth during the second year of a child's life; in recent years it has been found that by the second half of the first year of life, the diameter of the cornea reaches the size of an adult's. Everywhere, except at its edge, the cornea has transparency and consists of five layers: 1) epithelium, 2) Bowman's membrane, 3) the cornea's own tissue, 4) Descemet's membrane, and 5) endothelium (fig. 1). 1) The corneal epithelium is multilayered, flat, 0.04-0.05 mm thick with 5-6 layers (fig. 2) (according to some authors up to 8), embryologically a derivative of the ectodermal leaf covering the rudiment of the eye
3==r" ~" = лия P.,базаль-ный, состоит из цилиндрических клеток c плоским основанием, обращенным к Боу-меновой оболочке, и закругленными концами, обращенными к следующему второму слою клеток; ядра клеток овальны, протоплазма в большинстве случаев светлее, чем в клетках следующих слоев..Среди этих светлых клеток попадаются более темные и более высокие, c вогнутыми боковыми поверхностями и ядром, передвинутым к вершине, клетки; это - клетки, поднимающиеся в сле


Figure 1. Cross-section of a normal cornea: 1-epithelium; 2-Bowman's membrane; 3-nerve; 4-stroma; 5-Descemet's membrane; 6-endothelium; 7 and 8-corneal corpuscles; 9-plates of ground substance.
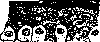
Fig. 2. Corneal epithelium; various layers of epithelial cells.
d following layers of the epithelium, and through them the regeneration of the epithelium occurs. In the second layer, consisting of two rows of so-called wing cells, the cells have a polyhedral shape; their planes (on sections) are convex in front and concave behind, the edges between the concave surfaces are more or less elongated in the form of wings. The diameter of the cells of the second layer is approximately the same in all directions; their protoplasm is darker than in the main layer. In the third layer - 2-3 rows of cells; these cells gradually flatten, and on the surface become completely flat, thin, thickening only in the area of the nucleus, but this thickening extends toward the deeper layers, so that the anterior surface of the cornea is even. The nuclei of the surface cells are also flattened and stained less intensely than in the deeper layers, but there are no traces of keratinization in the cells themselves. Among the cells of the corneal epithelium, wandering cells, leukocytes, mainly in the main layer, are often visible on sections. According to the generally accepted opinion, the connection between the epithelial cells is carried out by means of intercellular bridges in the form of threads, and the spaces between the bridges form a system of slits or channels filled with fluid, the sources of which are sought in the vessels of the corneal limbus and in its main tissue (through pores of Bowman's membrane) (Virchow). In recent years, Mans has put forward a new understanding of the normal connection between epithelial cells. In accordance with the views of Unna regarding the skin epithelium, he asserts that through all layers of the epithelium a system of fibers passes, starting from Bowman's membrane and reaching the uppermost layers of the epithelium. This system forms around the cell nuclei a densely woven basket of fibers, which was previously considered as the cell membrane. The fibers have a connection with the connective tissue fibers at the limbus on one side, on the other hand they probably have a connection with Bowman's membrane. The same system of fibers exists in the epithelium of the conjunctiva, and where there is no border membrane, it is in direct connection with the subepithelial connective tissue. In inflammatory processes, strong changes occur in the fiber system, especially where Bowman's membrane disappears; here, at the end of the process, a completely "unphysiological" epithelium can form. 2) Bowman's membrane (lamina ela-stica anterior, s. membrana Bowmani, s. Reicher-ti), on which the corneal epithelium lies, is a plate of uniform thickness - 0.01-0.016 mm, sharply delimited from the epithelium and not sharply from the underlying corneal tissue and merging with the latter (fig. 1). Structureless under normal examination, Bowman's membrane disintegrates upon maceration into fibrils and is essentially only a modified, compacted and cell-free anterior layer of the corneal's own tissue. On sections of Bowman's membrane, pores can be seen, intended for the passage of nerve fibers (rami perforantes). Bowman's membrane ends, not reaching 1.0-1.5 mm to the edge of the cornea (see below corneal limbus). As a feature of Bowman's membrane, good resistance of the cornea to injuries is noted, but at the same time poor resistance to infectious processes and the absence of the ability to restore its integrity after destruction (Reid). 3) The cornea's own tissue (ground substance of the cornea, substantia propria corneae) (fig. 1 and 2) constitutes the main mass, about 90%, of the entire thickness of the cornea. It has a lamellar structure (fig. 3); the plates, the length of which captures the entire cornea (Virchow), cross each other at large angles (about 90°) and interweave at very small angles of inclination, so that on sections they appear almost parallel to the surface of the cornea; their number, according to Salzmann, is 60-65 (according to other authors up to 100) and thickness about 0.01 mm. Individual plates consist of thin fibrils of connective tissue, arranged parallel to each other and glued together by interstitial substance. Adjacent plates often, in the anterior layers more than in the posterior, anastomose with each other by bundles of fibrils. Usually only two adjacent plates anastomose, but in the anterior layers there are bundles of fibers that pierce obliquely or arcuately several layers to Bowman's membrane (former name-fibrae arcuatae). In the ground substance of the cornea, a network of elastic fibers between the corneal plates is described (Tartuferi, Seefelder and others); a special accumulation of such fibers is located in front of Descemet's membrane. At the periphery of the cornea, the number of plates is greater than in the center. Between the plates are located corneal cells, or corneal corpuscles (fig. 1). These cells have a large, flat, round or irregularly shaped nucleus with
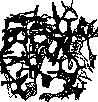
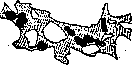
Figure 3. Corneal corpuscles Figure 4. Corneal corpus-
cles of humans lying in different planes.
of the main substance. with how many nucleoli and weakly granular protoplasm with numerous processes, by means of which the cells anastomose with each other, forming a closed network or syncytium (fig. 3 and 4). The old view of Recklinghausen about the existence between the plates of the cornea of a highly branched system of thin canals and slits, intended for the circulation of fluid and nutrition of the cornea, the so-called system of juice canals and slits, in which the cells of the cornea are also located, was not confirmed in the research of Leber, Kryukov and others. According to Leber, the injection of the canal system at the location of the corneal cells occurs because the connection of the cells with the main substance of the cornea is easier to disrupt than the connection between the plates; for the same reason, wandering cells are found mainly between the permanent cells of the cornea and the main tissue. Ranvier, Wolfrum and others also hold the same view. Closely related to this question is the question of the lymphatic vessels of the cornea, which is also resolved negatively by the majority. Virchow states that in this respect, three questions can be put before the anatomist: 1) are the slits we see in the main tissue of the cornea completely filled with cells, 2) can a connection be proven between these slits and the lymphatic vessels, *z 3) are there signs in the arrangement of cellular formations of a system of paths with a definite direction; based on his own experience and a review of literary data, he gives a negative answer to all these questions. Later research with the slit lamp, as well as works with vital staining of eye tissues, have not brought new data to this question. The study of corneal cells from the point of view of the reticulo-endothelial system showed that 1) in normal conditions, corneal cells do not accumulate dyes in themselves and therefore do not belong to the cells of the reticulo-endothelial system; 2) in non-penetrating injuries to the cornea and in the absence of blood vessels in it, histiocytes do not participate in wound healing; 3) together with the blood vessels, histiocytes also penetrate into the cornea from the pericorneal tissue; 4) in penetrating injuries to the cornea, and especially in the prolapse of the iris, histiocytes invade the cornea from the side of the vascular tract. In addition to the permanent cells in the main substance of the cornea, there are a small number of wandering cells - leukocytes. According to the latest embryological research of Seefelder, Fischer and others, after the formation of the corneal endothelium from the mesenchyme adjacent to the eyeball, the cornea consists of one single-layer outer and one single-layer in the center and multi-layered on the periphery inner layer of epithelium-like cells. Between them are the finest fibrils, which are considered as remnants of the anterior vitreous body. It is here that later cells from the undifferentiated mesodermal mass from the edge of the eye cup penetrate, forming the main substance of the cornea. From this same mass, the conjunctiva of the sclera is apparently also formed later. 4) Descemet's membrane (lamina elastica posterior) (fig. 1) sharply differs from the stroma of the cornea in sections and with ordinary staining, especially with staining for elastic fibers. It differs in its homogeneity, although with special treatment (maceration) it disintegrates into separate plates. The thickness of Descemet's membrane in the center of the cornea is about 0.006-0.01 mm, at the edges 0.01-0.02 mm. At the edge of Descemet's membrane, on its inner surface, there are usually warty hemispherical protrusions; the width of the edge occupied by such protrusions, as well as the thickness of the entire Descemet's membrane, increases with age. Descemet's membrane easily separates from the main tissue of the cornea and folds, for example, in operations to open the anterior chamber (extraction of cataracts, iridectomies, etc.), in injuries to the cornea, its inflammations, iritis, acute glaucoma, hypotony, etc. (Samenhof). According to Reid, Descemet's membrane, in contrast to Bowman's membrane, resists infectious processes in the cornea for a long time, but is easily damaged in eye injuries and is capable of independent repair. In its development, Descemet's membrane represents a cuticular formation, i.e., a product of the secretion of endothelial cells, and in this respect also differs from Bowman's membrane. 5) The endothelium of the cornea in the form of a single row of cells, 0.004-0.005 mm in height, with large nuclei and rich in protoplasm, covers the entire inner surface of Descemet's membrane (fig. 1), passing at the angle of the anterior chamber onto the surface of the iris. When viewed from the plane, the endothelial cells are mostly roundly hexagonal in shape. Morphologically, the corneal endothelium resembles epithelium, but embryologically it is of mesenchymal origin - from cells of the mesenchyme adjacent to the eye cup (Seefelder and others). Recently, Sondermann has expressed himself for the ectodermal origin of the corneal endothelium; the greatly thickened ectoderm at the apex of the lens vesicle, after its separation, splits by strands of the connective tissue growing in from behind, with the posterior of the separated cells going to form the endothelium. In in vitro cultures (Matsui), endothelial cells grow in the form of cells of various shapes - polyhedral, rod-shaped, sometimes resembling fibroblasts, but in essence not identical to them, sometimes round, but all these cells sooner or later take on an epithelial-like arrangement. As has been clarified by clinical observations and experimentally (recently by Scholik and others), the preservation of the endothelium is of great importance for the normal condition of the cornea, and damage to the integrity of the endothelium leads to a number of disorders, first of all to clouding of the cornea, and the endothelium itself has the ability to regenerate by multiplication. The limbus of the cornea represents a transitional area from the cornea to the sclera and conjunctiva; in it, the stroma of the cornea turns into the stroma of the conjunctiva, episclera and sclera. The inner boundary of the limbus lies where Bowman's membrane ends (see above), and thus the width of the limbus is on average about 1 mm. The width of the limbus can vary in different individuals, as well as in different races; thus, Ling established a greater width of the limbus in Chinese compared to Europeans. The structure of the limbus differs from the structure of the cornea. The epithelium of the limbus is thickened, the number of its layers can reach 10 or more; the boundary of the epithelium facing the stroma becomes wavy (and not straight, as on the cornea), and here we see the picture of true papillae. In the main layer of the epithelium, the cells immediately become smaller, poorer in protoplasm, and with a strongly staining nucleus. This type of cell of the main layer is maintained on its further course on the conjunctiva of the sclera. The cells of the limbus epithelium are often pigmented; this is especially noticeable in dark human races and in dark-colored animals. The stroma of the limbus first in the superficial, and then in the deeper layers, acquires the appearance of connective tissue, losing the characteristic of the main substance of the cornea the correct arrangement of layers. Here also appear the vessels of the superficial marginal loop network of the cornea as the terminal branches of the anterior ciliary vessels. Thin arterial vessels form between them arcuate anastomoses, from which thin terminal branches depart in the meridional direction, which quickly bend in the form of loops and pass into venous vessels. In the superficial layers of the limbus, elastic fibers are found, the number of which sharply increases when passing into the sclera. The limbus is the site of numerous surgical interventions on the eyeball. The cornea is abundantly supplied with nerves, the study of which at the present time has received great assistance in the form of vital staining of eye tissues with subsequent study of them with the help of a slit lamp. The nerves of the cornea originate from the ciliary nerves; from 60 to 80 nerve trunks, both myelinated and non-myelinated, enter the cornea at the periphery, with the thinner trunks lying in front and the thicker ones behind. Myelinated fibers lose their sheath at a distance of 0.3-0.5 mm from the edge of the cornea. In the main substance of the cornea, the nerve fibers form in its middle and anterior layers, not involving the posterior layers, the 'plexus of the main substance of the cornea' (Virchow). Near Bowman's membrane, a fine network is formed - the 'closing network', according to Virchow, this is plexus annularis corneae, from which branches depart, piercing Bowman's membrane and forming a subepithelial plexus; from the latter, branches depart, breaking down into fibrils and ending in the epithelium with round or pear-shaped button-like thickenings. Under the epithelium at the limbus and under the edge parts of Bowman's membrane, terminal bulbs are found, identical with the terminal bulbs of Krause. The old dispute about whether there is only sensation of pain in the cornea (Frey, Marx and others) or whether, in addition to it, there is also sensation of pressure (Nagel, Goldscheider and others) continues to this day.
Strughold, summarizing the latest literary data on this issue, points out: 1) that sensation of pain is most strongly developed in the center of the Cornea, while its periphery is less sensitive to pain; 2) that sensation of cold is absent in the center of the Cornea and well-developed on the periphery; 3) that sensation of heat is absent on the Cornea and even on the scleral conjunctiva; 4) that the question of sensation of pressure on the Cornea, separate from sensation of pain, remains controversial (Strughold himself is a defender of the positive solution to this question). Nutrition of the Cornea, like that of the entire eye, stands in the closest dependence on the nutrition of the entire organism. Recent years have brought new facts in proof of the significance of avitaminosis for eye and Cornea nutrition. Experiments on guinea pigs, mice (BellaVia), rats (Yudkin) and clinical observations on humans have proven that with a deficiency of vitamin A, a series of changes occur on the Cornea (see Avitaminosis, A-vitaminosis). It has been proven that in children under such conditions keratomalacia can develop (see). In adults, some similarity to the latter is presented by the so-called marantic ulcers of the Cornea, developing in poorly nourished patients, especially with severe liver diseases (cirrhosis, cancer); their course is sluggish, but as a result they can destroy the entire Cornea. Nutrition of the Cornea itself occurs by diffusion and diosmosis. By the first path is distributed the fluid coming from the peripheral blood vessels into the Cornea, since the old concept of Recklinghausen about the existence of a canalicular system has not been confirmed (see above). By the second path, soluble substances from the anterior chamber can enter the Cornea, but since such substances are scarce there, the process of diosmosis has less significance for Cornea nutrition. Fischer's research showed that the permeability of the Cornea depends on the state of its epithelium and endothelium, and that the ground substance of the Cornea plays a subordinate role in this respect. Pathologically altered Cornea has more complex conditions of permeability than normal Cornea. The Cornea has the ability to pass certain substances only in one direction, for example sodium chloride penetrates only into the eye, not back; oxygen from the air also penetrates into the eye, while carbon dioxide penetrates through the Cornea from the anterior chamber only outward. On the other hand, the permeability of the Cornea also depends on the concentration of hydrogen ions of the administered substance. Partly due to the absence of vessels in the Cornea, partly due to evaporation of the tear fluid from its surface, its temperature with the eye slit open is lower than the temperature of surrounding tissues, reaching only 30°; with closed eyelids it rises to 35-36°. Due to the low temperature of the Cornea, growth of mold fungi is possible on it, which do not grow on living human skin due to the too high temperature for them (Fuchs). Due to the absence of vessels in the Cornea, it does not contain under normal conditions in its tissue fluid, especially in its central parts, protective substances characteristic of the normal blood serum of the same organism. With artificial general immunization (vaccination) of the organism, the Cornea participates to a certain degree in the general immunity, but the fluid of the anterior chamber still contains significantly less immune bodies than blood serum (Yamada et al.), and repeated punctures of the anterior chamber are necessary to promote their increase. With local immunization by injections into the Cornea itself or into the anterior chamber (Mutermilch, Yamada, Bursuk et al.), local immunity significantly increases. With infection through the eye, development of humoral immunity significantly lags behind that with the intravenous method of immunization, so that the eye is unsuitable as an entrance gate for vaccination of the organism (Polev and Mikoyan et al.). To obtain with local immunization of one eye development of immune bodies in the Cornea of the other eye, it is necessary to subject it to repeated irritations (scarifications), but even under these conditions there will still be fewer immune bodies than in the primarily immunized eye (Polyak, Bursuk). Experiments are being conducted on vaccination by introducing vaccine into the conjunctival sac in the form of drops and ointments (Polyak, Chirkovsky and Dymshits), but in general clinical application of immunization through the Cornea is still only in the stage of being worked out. The Cornea of the newborn has certain features compared to that of an adult. According to the data of Merkel and Oppa (Merkel, Orr), the Cornea of the newborn on the periphery is more curved than in the center, i.e., opposite to what is observed in adults. Bowman's membrane of the newborn is of the same thickness as in adults, conversely, Descemet's membrane is more delicate; the own tissue of the Cornea is much richer in nuclei. The main growth of the Cornea, as indicated above, falls on the first year of life; as the Cornea increases in volume, the number of nuclei in its stroma decreases; Descemet's membrane reaches its usual thickness; warty growths on its periphery are noted for the first time at the age of 9 years. Later age changes in the Cornea manifest themselves in the form of arcus senilis (see), some cloudiness of the periphery of the Cornea in old age, decrease in the transverse size of the Cornea obviously due to cloudiness of the limbus, flattening of the cornea, with the vertical meridian flattening more strongly than the horizontal and reverse astigmatism developing. The Cornea in normal condition is characterized by: a mirror-smooth surface, spherically convex shape, a certain size, transparency and sensitivity. These properties of the Cornea are paid attention to during its examination: by simple inspection, inspection with side illumination and with a simple magnifying glass, corneal microscope and slit lamp, keratoscope, ophthalmometer, in transmitted light and finally on the state of its sensitivity (see below). For more precise research of the shape of the Cornea and its surface, the so-called keratoscopes are used, the most common of which is Placido's keratoscope. It is a disk on which concentric white and black rings are depicted and in the middle there is an opening. If such a disk is brightly illuminated and held in a strictly frontal plane at a close distance before the eye, looking at its mirror image on the Cornea through the central opening, then with a normal condition of the Cornea a sharp image with distinct regular circles will be visible in its center; on the periphery of the Cornea the circles will be somewhat elongated and stretched in the meridional direction. With pathological deviations in the shape of the Cornea, the images will also be elongated or shortened in the center of the Cornea, and with violations of the Cornea surface the contours of the images are blurred and appear saw-toothed. There are modifications of the keratoscope, where instead of a circle a quadrangular plate with the same lines is taken, or instead of circular lines radial strips are applied. At present, Zeiss has proposed the so-called photo-keratoscopes, where the obtained image is immediately, so to speak, documented on the corresponding photograph. In the absence of a keratoscope, it is permissible to replace it with the reflection on the Cornea of the image of a window frame, and also correct and distinct or distorted and unclear images of the frame are obtained. Further development of keratoscopy - see Ophthalmometer. Changes in the surface of the Cornea are most often a consequence of inflammatory diseases of it, keratitis (see), and are expressed either in depressions of the surface-ulcers, traumatic injuries, or in elevations above the Cornea surface-inflammatory foci, foreign bodies, prolapses through the wound opening or perforating ulcer of the iris membrane, finally the so-called keratocele or descemetocele. Under this name are described small translucent elevations that sometimes form in the place of Corneal ulcers, when the ulcer destroys the entire thickness of the Cornea down to Descemet's membrane, and the latter due to its increased resistance does not break down but protrudes in the form of a hernia, filling the ulcer defect and protruding above the surface of the Cornea. Along with keratocele it is necessary to mention partial ectasias of the Cornea on the basis of former limited ulcers, inflammatory (see Keratitis) and degenerative processes (see below). The Cornea, having lost its elasticity on a given segment due to the mentioned processes, partially protrudes. Changes in the size of the Cornea occur both in the direction of increase-megalocornea, and in the direction of decrease-microcornea, but it should be noted that between macro- and microcornea, on the one hand, and normal size on the other, sharp boundaries cannot be drawn, since they are connected by a series of imperceptible transitions (Peter), and under the names of the above-mentioned anomalies only sharp degrees of deviation from the average size are implied. Both conditions are mostly of a congenital nature, but a definite type of heredity has not yet been established (Peter). Microcornea is often one of the signs of general underdevelopment of the eyeball-microphthalmia, and the size of the Cornea can be the most diverse, up to a small piece of flattened transparent tissue of irregular round shape. Acquired microcornea is one of the symptoms of atrophy of the eyeball. Megalocornea, in which the diameter of the Cornea can reach 14-16 mm, in most cases occurs in the so-called hydrophthalmia, when due to increased intraocular pressure not only the Cornea but also the sclera and the entire eyeball as a whole are stretched.
At the same time, ruptures of Descemet's membrane are often observed in the form of arc-shaped lines on the posterior surface of the Cornea. There may be megalocornea without hydrophthalmos (without stretching of the sclera and without ruptures of Descemet's membrane) with satisfactory vision. This condition is familial. Changes in the size and shape of the Cornea also include keratoconus and keratoglobus (see Staphyloma). Among congenital anomalies of the Cornea, it is necessary to mention the so-called embryotoxon—a ring-shaped opacity of the edge of the Cornea, somewhat resembling arcus senilis (see), but extending further toward the center and, on the other hand, being in direct connection with the sclera. Apparently, this formation represents the sclera that has overlapped onto the Cornea. Congenital opacities in the central parts of the Cornea also belong here, the cause of development of which is considered to be defects in Descemet's membrane and insufficient separation of the pupillary membrane from the rudiment of the Cornea, or disorders in the separation of the lens, or intrauterine inflammation of the eye, or finally, trauma during childbirth (forceps). These anomalies are often observed simultaneously with a whole range of other developmental defects and occur in several members of the same family (Peters). Congenital anomalies of pigmentation of the Cornea, melanosis corneae, have been described, with epithelial and endothelial forms distinguished; in the first, pigmentation is associated with generally frequent pigmentation of the limbus, in the second, the pigment in the form of a spot lies in the center of the Cornea and is considered a remnant of the pupillary membrane. A benign neoplasm of the Cornea also belongs to congenital conditions—the dermoid, usually located at the periphery of the Cornea at the limbus in the form of a dense hemispherical tumor with a smooth surface, on which there are sometimes hairs. Among other benign neoplasms of the Cornea, epithelial hyperplasias—epitheliomas according to Lagrange—and papillomas should be noted. Clinically, both appear as pale pink, flat, delicate papillary formations, which usually originate from the limbus of the Cornea. After removal, they often recur and tend to degenerate into carcinomas (Polev, Lurie). Carcinomas of the Cornea, also developing at the limbus, are initially difficult to distinguish from papillomas, but later they acquire a nodular appearance and cause ulcerations; their growth on the Cornea occurs mainly on the surface, but they can also destroy the Cornea, growing into the anterior chamber, as well as into the orbit and adjacent accessory cavities. Pigmented carcinomas developing from naevus pigmentosus of the limbus, as well as carcinomas in xeroderma pigmentosum, are encountered. Finally, cases of sarcoma of the Cornea developing from the limbus in the form of flat, smooth (non-papillary) formations, more prone to grow into the eye along the course of blood vessels than carcinomas, have been described. The treatment of all malignant neoplasms is surgical, followed by cauterization and the use of X-rays and radium. 7 7 A special group of Cornea diseases are the so-called neurotic keratitis, the cause of which are diseases of the nerves of the Cornea. These include: neuroparalytic keratitis, herpes corneae simplex and herpes zoster, keratitis disciformis, recurrent erosions of the Cornea and ulcus rodens (see Keratitis), keratitis superficialis punctata (Fuchs) and filamentary keratitis. In filamentary keratitis, with signs of irritation, thread-like formations are found on the Cornea, one end of which is attached to the Cornea, while the other is free. The filaments are formed due to the epithelium and often recur. The disease is prolonged, but the prognosis is generally favorable. It is believed that filamentary keratitis is a complication of herpes and recurrent erosions of the Cornea, hence the treatment, common with these diseases. According to the latest views (Hanke), keratitis superficialis punctata also belongs to the neurotic conditions of the Cornea. People who have had influenza often develop keratitis superficialis punctata; initially, signs of conjunctivitis develop, but without catarrhal discharge, and they last for several days, up to a week, and then on one or both Corneas, superficial grayish point opacities appear, arranged in groups or lines, mainly in the central parts of the Cornea. Ulcers are observed as an exception; sometimes there is a decrease in sensitivity of the Cornea and intraocular pressure. The course is prolonged, the prognosis is favorable—the opacities disappear. Treatment is according to general rules. Infections (see Keratitis) constitute one of the most common causes of Cornea diseases. Among infectious inflammations of the Cornea, gonorrheal keratitis (see Blennorrhea, blennorrhea of newborns) have a particularly severe course. Among infectious ulcers of the Cornea, it is necessary to mention the so-called infectious marginal ulcer of Nedden (zur Nedden), caused by a special rod of Nedden—a Gram-negative, straight or slightly curved rod, often arranged in diplobacilli and resembling the bacillus of xeroma. The infectious ulcer resembles catarrhal ulcers (see Keratitis), but differs from the latter in that it does not have true signs of conjunctivitis. These ulcers are less commonly located in the central parts of the Cornea. The prognosis is favorable. Syphilis plays a very large role in Cornea diseases. On its basis, the following develop here: typical parenchymatous keratitis, deep punctate keratitis of Mauthner, sclerosing keratitis (see Keratitis), K. pustuliformis profunda (Fuchs), gummas of the Cornea, and finally superficial keratitis on the basis of acquired syphilis, sometimes developing in the secondary period as a concomitant phenomenon in lesions of the conjunctiva. K. pustuliformis profunda (Fuchs) begins with signs of iritis, and then in the deep layers of the Cornea, gray bands appear, and later yellowish purulent infiltrates (like pustules) of various sizes. There are usually several infiltrates, less often one large one. The Cornea does not ulcerate, hypopyon is present in the anterior chamber, and the deep parts of the eye are involved in the process. The course is prolonged, the prognosis is severe. Gummach of the Cornea—a relatively rare formation in the form of a voluminous infiltrate in the thickness of the Cornea, susceptible to the effect of energetic specific therapy (F. Arkhangel'skii). A fairly large section of Cornea diseases consists of degenerative changes of it or dystrophies of the Cornea. They differ from inflammations of the Cornea: 1) clinically—the absence of inflammatory phenomena; 2) an invariably progressive course of the disease; 3) a pathological-anatomical picture where degenerative processes are present, not phenomena of inflammation. In the doctrine of the etiology of Cornea degeneration, despite the abundance of published observations, much is still unclear, and Hanke, after an extensive review of the literature of recent years, comes to the same conclusion. It is believed that the causes of dystrophy are either age, or disorders of nutrition of the eye, or hereditary developmental defects. Recently, changes in the nerves supplying the Cornea and naturally associated with this nutritional disorders have attracted great attention as an etiological factor. Dystrophies of the Cornea include: 1. Arcus senilis (see). 2. Dystrophia epithelialis corneae (Fuchs), characterized by diffuse superficial opacity of the Cornea, mainly in the area of the pupil. The epithelium over the opacity has a dull, swollen appearance and resembles coarse shagreen; in old cases, it is raised in the form of vesicles. These vesicles, as well as delicate dark points, correspond to small cavities inside the epithelium. Sensitivity of the Cornea is lost. Sometimes intraocular pressure increases. The course is prolonged, progressive, leading to a sharp decrease in vision. The disease affects one or both eyes, usually in elderly people. As a cause, changes in the nerves of the Cornea (Fuchs) or disorders of the glands of internal secretion (Seefelder, Leber) are indicated. Treatment is unsuccessful. 3. Dystrophia calcarea, calcareous degeneration of the Cornea (Axenfeld) with deposits of lime mainly at the periphery of the Cornea in the form of shiny opacities. Pathologically-anatomically: deposits of salts of phosphoric lime between the plates of the Cornea, mainly in the deep layers, without any signs of inflammation. Sensitivity of the Cornea is unchanged. 4. Dystrophia adiposa, fatty degeneration of the Cornea: secondary as a result of the breakdown of exudate, hemorrhages, necrotic masses, or primary, where the Cornea is infiltrated with fat brought from the body. The disease develops slowly and as a result gives a diffuse, except for the periphery, dense, yellowish-white opacity, the surface of which is uneven, slightly pitted and little sensitive. 5. Dystrophia uratica, described by Uthoff and Chevallier, the deposition of crystals of uric acid in the Cornea. 6. Band-shaped opacity of the Cornea in the form of a gray ribbon 3-5 mm wide, running across the Cornea, slightly below its center. It develops slowly over a number of years, first the ends of the opaque band form, which then merge with each other. Anatomically: deposition of lime salts and hyaline concrements in Bowman's membrane, breakdown of Bowman's membrane into parts, and development of connective tissue in its place. Usually the disease develops on blind, degenerated eyes, but in rare cases it can also be on otherwise healthy eyes. In the latter cases, one can try to dissolve the lime with eye baths with a 10% solution of neutral ammonium carbonate, or in old cases, take care of the surgical scraping of the opacities. 7 and 8.
Nodular and lattice-like opacities of the Cornea—two closely related diseases—begin usually in young years and last throughout life, often affecting several members of the same family. On the Cornea, predominantly in the pupillary part, there is in nodular opacity a mass of small, variously shaped grayish opacities, which sometimes merge into larger irregular figures; in lattice-like opacity, along with nodules, there are opacities in the form of streaks forming an entire network. With superficial position of the nodules in nodular opacity, a rough roughness of the Cornea's surface results. At times, there are slight exacerbations of the processes, and the spots gradually increase. The state of sensitivity of the Cornea varies, ranging from normal to almost complete anesthesia. Path-anatomically in nodular opacity, deposits of hyaline are found in the superficial layers, or, according to Fuchs, of two substances—one amorphous acidophilic between the epithelium and Bowman's membrane, and another granular basophilic, mainly in the tissue of the Cornea. Clinically, as a result of the increase of opacities and the formation of cloudy spots consisting of separate points, a third form of this dystrophy may develop—spotted opacity of the Cornea. The etiology of all these dystrophies is not clarified; recently, the opinion of the trophoneurotic nature of the processes has been particularly emphasized. 9. Pannus degenerativus sometimes develops on eyes blinded by iridocyclitis, glaucoma, etc., clinically resembles trachomatous pannus (see Pannus) and represents a dull superficial opacity of the Cornea, penetrated by superficial and deep vessels. Anatomically, there is development of connective tissue under the epithelium and in the superficial layers of the Cornea. Treatment is unsuccessful. 10. Keratitis corneae—see Keratitis. 11. Keratosis corneae—one of the forms of xerosis, in which the Cornea appears dull, dry, not wetted by liquids, and its epithelium is thickened and cornified. Keratosis is observed in trachoma, pemphigus, burns, with insufficient closure of the Cornea by the eyelids. 12. Colloid, hyaline, and amyloid degeneration of scars of the Cornea, especially old ones, is not uncommon. In the degenerated places, calcium salts may be deposited. In the same scar, substances with different chemical reactions may be present, which indicates that they represent only different stages of the same process (Hippel). These degenerated places may ulcerate, and for the treatment of such ulcers, curettage with a sharp spoon can be applied, followed by plastic surgery according to Kuhnt, in case of poor healing. 13. In old people, over a well-developed arcus senilis, a symmetric development of a groove or furrow is sometimes observed on both Corneas, the peripheral edge of which gradually passes into the limbus of the Cornea, and the inner edge steeply, almost vertically—into the arcus senilis. Small vessels are visible in the furrow, but there are no signs of irritation. This is marginal thinning of the Cornea, or dystrophia marginalis symmetrica (Fuchs), or peripheral furrow keratitis (Schmidt-Rimpler), which can later lead to protrusion of the thinned tissue of the Cornea, to the so-called peripheral ectasia, of course associated with the development of strong astigmatism. Sometimes the protruded part of the Cornea even with slight trauma ruptures with all the consequences for the eye. In case of threatening rupture and after it, conjunctival plastic surgery according to Kuhnt (Kuhnt) can be recommended. As after inflammations of the Cornea and especially after ulcers, and after the above-mentioned degenerations of the Cornea, corneal scars may remain in the form of a cloud, spot, or leucoma [nubecula, macula, лейкома' (еж.)]. Leucoma, adherent to the iris (leucoma adhaerens) and protruding under the influence of intraocular pressure, receives the name leucoma ectaticum or staphyloma (see Staphyloma). Injuries to the Cornea are very frequent, and among them the most common—up to 80% of all eye injuries—are: 1. Foreign bodies in the Cornea. On foreign bodies in the Cornea as a professional disease and on their influence on the reduction of Corneal sensitivity—see Vision, professional diseases of the organ of vision. Oxidizing foreign bodies in the Cornea (iron, etc.) irritate the eye more than non-oxidizing ones, which sometimes may not cause any reaction at all. Foreign bodies are removed with a special needle. Deeply seated in the Cornea and chemically indifferent foreign bodies (gunpowder, coal, etc.) are often not removed at all. If a foreign body is seated only in the epithelium of the Cornea, then after its removal no trace remains, otherwise at least a point-like scar remains. The greatest danger in injury by a foreign body is primary or secondary infection and development of Corneal ulcer. To prevent this, the eye is washed with a disinfecting solution (mercuric cyanide, etc.), collargol, optochine, etc., are instilled into the eye, disinfecting ointments are applied, and a dressing is applied.—2. Erosions of the Cornea (see Keratitis) are very common in everyday life and in production. In the fight against foreign bodies and erosions of the Cornea, the most important thing is of course their prevention; on preventive measures see Foreign bodies.—3. Thermal burns of the Cornea can be superficial and deep. In superficial burns (match heads, particles of hot coals, small hot particles of metal, etc.), only opacity of the epithelium is observed with its regeneration after several days. In deeper burns, where the tissue of the Cornea itself becomes necrotic, scars remain after healing; the scarred Cornea may later protrude. Treatment of burns—washing with disinfecting solutions, non-irritating ointments, ointment with Scharlachrot 3-5% as promoting epithelialization, atropin—indicated. 4. Chemical burns of the Cornea are most often caused by acids and alkalis. In mild acid burns, the epithelium becomes necrotic and the Cornea slightly clouds. In the action of concentrated acids, the tissue of the Cornea also becomes necrotic; the prognosis is usually poor. One should not be misled by seeing the transparent part of the Cornea after the rejection of necrotic tissue, because usually in such cases not only the entire Cornea dies, but often the entire eye. The same degrees of damage can occur in alkali burns, and here the prognosis should always be cautious, and in more severe cases—poor. Treatment in acid burns—washing with weakly alkaline solutions, best of all a 1/2% solution of caustic potash, or a weak solution of soda or simply a large amount of water. In alkali burns—thorough washing with weak acetic acid (1:1,000) or abundantly with water. In lime burns, all pieces of it are carefully removed from the surface of the eye and the conjunctiva of the eyelids and washed abundantly with water or even better with oil. Further treatment, as in burns in general—indifferent ointments, atropin as indicated. In severe burns, transplantation of mucous from the lip according to Denig (Denig) is recommended to the burned areas. In burns with salts of heavy metals (zinc, lead, silver, copper, mercury, etc.), opacities of the Cornea are formed to varying degrees depending on the concentration of the solution and duration of action. Treatment—abundant washing with water. Of burns with organic substances (alcohols, chloroform, essential oils, aniline dyes, etc.), it is necessary to especially note burns with aniline ink pencils. In mild cases, there is coloring of the tissues in the color of the pencil, roughness of the Cornea and its opacity; in severe cases—ulcer of the Cornea and its destruction. Treatment—thorough washing of the eye with water and removal of all residues of the cauterizing substance; in burns with chemical pencils—solution of tannin in drops. 5. Burns of the Cornea by radiant energy (ultraviolet rays, X-ray and radium rays, electric arc in electric welding, etc.). In mild degrees of burn, there are only signs of irritation in the eye, and upon examination with a slit lamp, slight desquamation of the Corneal epithelium. In severe burns—infiltration of the entire Cornea and tissue disintegration. Subjectively—strong photophobia, sensation of sharp foreign bodies in the conjunctival sac.—6. Under the action of high-voltage electric current, opacity of the Cornea may occur, disappearing after several days. In lightning strikes, opacities of various shapes in the Cornea have been noted, which usually resolve in the same way. Treatment—protection from light, cold compresses, indifferent ointments, for pain—cocaine. For prevention of damage by radiant energy—special glasses made of glass with lead admixture.—7. Perforating injuries to the Cornea can be of very different sizes and shapes and are usually accompanied by prolapse of the iris into the wound. Uninfected and uncomplicated by lens injury wounds of the Cornea can close very quickly, and in 8-14 days all signs of irritation subside. Infected penetrating injuries can lead to the death of the entire eye. In small uncomplicated injuries to the Cornea, one can be limited to a dressing and atropin. In case of iris prolapse, it should be either repositioned, in fresh cases, or excised; in old cases, cauterization of the prolapsed iris can be done. gaping wounds are sutured or conjunctival plastic surgery according to Kuhnt is performed.—8. In injuries to the eyeball in general and to the Cornea in particular, the epithium penetrating into the wound canal can grow there, forming cysts. In contusions of the Cornea, opacities of the Cornea, usually milky-white in color, or ruptures of the Cornea (relatively rarely) may occur.
Ruptures may go in various directions; if they are very large and the eye is lacerated, then it is necessary to perform enucleation.-The R., especially its limbus, is the site of incision in the most diverse operations. Among operations on the R. itself, one should mention paracentesis of the R., i.e., an incision of the edge of the cornea with a spear-shaped knife with the aim of gaining access to the anterior chamber of the eye for the removal of pus, foreign bodies, cataractous MASSES AND ETC.
A. Pokrovsky. Mitogenetic radiation of the cornea is at present a firmly established fact. The epithelium of the R. belongs to the few sources of mitogenetic radiation described in adult animals. When the R. of a rabbit eye is exposed to an ordinary detector of mitogenetic rays (see0 for 30 sec. - 1 min., it is possible to detect a clear effect of induction of mitoses. Fundamentally coinciding results were obtained for the R. of the frog and man. In the latter case, correspondence of the obtained effect with the presence or absence of blood radiation has been shown,-a circumstance of great methodological importance, as it facilitates the setting up of experiments clarifying the dependence of radiation on the general state of the organism (fatigue, presence of malignant neoplasms, etc.). A number of data, in particular biological spectral analysis, forces one to accept that in the R. there are sources of radiation of two kinds-powerful glycolytic radiation, apparently arising secondarily from primary mitogenetic irradiation from blood vessels passing along the edge of the R., and a weaker-nucleolytic radiation, primarily arising in the R. In 6-day starvation of an animal (rabbit), the chemistry of corneal radiation essentially changes-instead of glycolytic, proteolytic radiation appears, which apparently originates in the beginning of autodigestion of the body's tissues. A number of works have established the significance of the cornea as: an excellent detector of mitogenetic radiation.
s. Zalkind.
Related articles
Mentioned in
Cite this page
“Cornea.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/cornea/