Newborn
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article defines the newborn as a child in the first two to three weeks of life, a period characterized by adaptation to extrauterine existence and the healing of the umbilical wound. It details the physiological and pathological peculiarities of this stage, including the newborn's fragility, susceptibility to sepsis, and specific developmental markers like weight loss and physiological jaundice.
Encyclopedia article (1928–1936)
NEWBORN, a child during the two to three weeks from the moment of birth. During this time, adaptation to extrauterine life occurs, the umbilical cord, which served as the connection between him and the mother, falls off and heals, and the consequences of birth trauma are leveled out. It is very difficult to strictly delimit this period from the subsequent infancy, especially since its duration varies in different children and depends both on the individual characteristics of the given child and on external conditions. Different authors have based this delimitation on different moments. Some on the time of the umbilical cord falling off, others on the duration of physiological jaundice, the presence of secretion of the mammary glands in the child, the period of colostral feeding (Birk), etc. Perhaps the most acceptable of all would be the moment of weight stabilization, indicating that the organism has recovered from the loss that occurred in the first hungry days of life, that it has somehow coped with the difficulties of its independent existence and is already on the path of gradual increase in its body mass. But this moment is very variable in connection with the constitutional features of the given newborn and with the conditions of care and environment. The period of two to three weeks includes, in addition to the above, a whole series of other, also extremely important moments: the blood formula is established, enzymatic abilities increase, some peculiar physiological processes occur, such as physiological jaundice, uric acid infarct, phenomena of 'sexual crisis'; finally, sometimes a peculiar pathology, characteristic only of this age, unfolds. These two to three weeks are a completely special and unrepeatable period in later life: entire systems unfold, which are beginning to function for the first time and are therefore still insufficient, such as the respiratory and digestive systems; the child encounters a whole series of harmful factors unusual for him: low temperature, microbes, feeding difficulties, etc. His protective forces are small, phagocytic ability is lowered, the skin and mucous membranes are especially vulnerable, the intestinal wall is permeable to microbes, the vessels are fragile and easily rupture, which creates a tendency in the newborn to hemorrhages. All this, along with the presence of a physiological umbilical wound in the body, makes the newborn a fragile being in need of a particularly careful approach. Infection, once having penetrated his organism, has favorable conditions for the generalization of the process, for the transition into general infection, i.e., sepsis. Along with this, the newborn proves to be insusceptible to certain banal childhood infections, such as measles. Both the physiology and pathology of this age are peculiar. The functions of the organism gradually adapt to new work. Reactions to various conditions of the external environment also have their own peculiarities and differ from those at a later age. Let us point to the great thermolability of the newborn, to the so-called physiological weight loss, to the 'transient fever of the newborn'. The general reaction of the organism in painful states is distinguished by insignificance or complete absence of temperature increases even in general septic diseases, a tendency to generalization of infection, and blurred forms of the clinical picture, especially in weak and premature children. In general diseases, phenomena from the central nervous system, which is especially vulnerable at this tender age, often come to the fore—convulsions, general depression, respiratory disorders of a central character, etc. In order to create a healthy organism, an in-depth study of the child from the moment of birth and careful care for him are absolutely necessary. The newborn is an object that is still little studied and for a long time was exclusively under the jurisdiction of obstetricians. It must be said that the founders of the doctrine of the newborn are precisely obstetricians, and the works of Runge, Budin, and Jaschke are still classical. Few, however, can, like them, combine an in-depth study of the mother and child, and the most expedient is the joint work of an obstetrician and a pediatrician, into whose care the newborn passes from the moment of birth. The latter measure, along with the separation of the child from the lying-in woman and his transfer into the hands of specially trained personnel, is now carried out in all properly organized institutions, and in Moscow it was first implemented by A. N. Rakhmanov and G. L. Grauerman about 25 years ago. Appearance, weight, height, size. The newborn in the first days of life seems to continue his intrauterine life. He spends all his time in a state of sleep and maintains an intrauterine position with sharply bent upper and lower extremities; extension of the latter seems to cause unpleasant sensations in the child. Only with foot and incomplete breech presentations are the legs extended at the knee joints. In the latter variety, they are also bent at the hip joints and seem to stick up and forward. Characteristic features of the physique of the newborn are the relative size of the head, the relative shortness of the limbs, and the apparent absence of a neck. The head is equal to 1/4 of the total height, the upper and lower extremities are approximately equal to each other, as well as to the length of the trunk (about 18 cm according to Chulitskaya, about 20 according to the Brain Institute). The midpoint is above the navel. The trunk and limbs of the newborn have a rounded shape, because the subcutaneous layer is well developed, especially on the cheeks, thighs, shins, and back of the neck. The skin is delicate, bright pink, covered with down, especially on the shoulders and the upper part of the back. The hair on the head is 2-3 cm long, the nasal and ear cartilages are quite firm, the nails on the hands extend beyond the pulp of the fingers. With various irritations, the newborn cries loudly and moves his limbs energetically. (Regarding indices and constitution, which usually appear in infancy, see Constitution, Infant.) In cases where it is necessary to decide whether a given child is a newborn, it can be decided affirmatively on the basis of the following signs: the presence of an umbilical cord or a fresh umbilical wound on the body, phenomena of physiological jaundice, configuration and remnants of the birth tumor on the head, the meconial character of the stools, the presence of a uric acid infarct. The length of the newborn fluctuates within the range of 46 to 54 cm, but extreme boundaries are rare; 50 cm for boys and 49-49.5 cm for girls can be taken as the average, provided that they are measured with a stadiometer and with the fullest possible extension of the lower extremities. With a large configuration of the head, it is more correct to take the measurement a few days later. A whole series of conditions influences the absolute height of the newborn: parity of births, heredity (children of small and large parents), racial characteristics. Thus, according to Babasyants, among Georgians, boys sometimes reach 69 cm, and girls 56 cm. Determination of body weight is a more important and also more accurate measure of a child's development. The limits of weight fluctuate in quite significant sizes. The vast majority of full-term newborns weigh from 2,800 to 4,000 g, with rare deviations downward to 2,500 and upward to 4,300 g and more. Children weighing less than 2,800 g are usually at least to some extent premature, although this circumstance is often not diagnosed. Small children, although full-term ('petite espece' of the French), are encountered relatively rarely. Children weighing over 4,500 g received the name of giant children ('Riesen-kinder') in Germany. Cases of newborns with a weight of 11,500, 12,000 g have been described, with the first child of the same mother weighing 7,600 g. The majority of children in the USSR are born with a weight of 3,000 to 3,800 g: 64.3% according to Dulitsky (1923-24), 56.05% according to Speransky (1910-13). The increase in this figure for 1923-24 must be linked to the implementation of the law on rest for pregnant women. Among the causes influencing the weight of the newborn, the weight and height of the parents undoubtedly have important significance. Bowditch thinks that the weight of the newborn is 1/20 of the weight of his mother. The significance of racial characteristics is undeniable. In Sweden, the average weight of a newborn is 3,527 g (Petersson), in Norway - 3,466 (Benestad), in France - 3,000-3,250 (Marfan); in the USSR, Georgian children are distinguished by high weight, and Jewish children by low weight. According to Gundobin, the average weight of a newborn is 3,000-3,250 g, according to later statistics it is about 3,400 (Speransky 3,410, Bischoff 3,403, Dulitsky 3,386). Boys are generally somewhat heavier than girls. Some authors note the influence of the season on the average weight of the newborn. The lowest weight falls on the coldest winter months (from November 15 to February 15). Then the weight gradually increases and is highest from August 15 to November 15. Some explain the weight decrease by the vitamin-deficient winter diet of mothers, others see in the weight increase the influence of light and sun on the pregnant woman and the fetus. Children of multiparous mothers are usually heavier than their firstborns. Some authors believe that the weight of the newborn in subsequent pregnancies increases up to the 5th-7th child, and then no increase is observed. Does the nutrition of the pregnant woman affect the weight of the fetus? The answers to this question are contradictory. Although some obstetricians still prescribe a meager diet to mothers with a narrow pelvis in order to reduce the volume of the fetus, most consider the Prochownik diet outdated and devoid of scientific justification.
During the last war, the majority of German authors (Bumm and others) came to the conclusion that as long as the mother is healthy and has a normal blood composition, the fetus draws from her blood the substances necessary for it in a sufficient quantity, despite her starvation. The average weight of a newborn in Germany did not decrease: according to Bumm, 3,250 g for peacetime and 3,320 g for wartime. Similar conclusions were reached in our country by Troitskaya (Moscow) and Binshok (Leningrad). Some authors note that the percentage of children with low weight was higher during the war years, and children with high weight were significantly fewer than in normal times. Material security and the mother's labor, especially heavy or night work, have an undoubted reflection in such indicators of fetal development as weight and height. The importance of the mother's rest in the last period of pregnancy in terms of increasing fetal weight was pointed out by Pinard, and in this sense, the law on prenatal and postnatal rest constitutes an essential link in our measures for antenatal infant protection. The mother's ill health has an influence on the weight of the fetus, obviously mainly in the sense that the percentage of premature infants will be especially high here (in eclampsia, in severe stages of tuberculosis). As for full-term children born to sick mothers, this question is still controversial and requires further precise observations. Along with the hopeless view of these children as doomed (Pinard and others), a more optimistic opinion is emerging regarding their physical soundness in the event that they are full-term and have not suffered from interventions (regarding eclampsia, data from Ivanova; regarding tuberculosis, Debre, Chebotarevskaya). The weight loss that occurs in the first days, both in most animals and in newborns, is called "physiological" due to its constancy. Usually, the weight drops during the first 3 days, and at the end of the 3rd day, it begins to rise and reaches its initial point rarely on the 10th day (Budin's type), much more often by 2 weeks, and sometimes even later (Pies' curves; see Body weight). The average loss according to French authors is from 150 to 200 g, according to German ones—200-250 g. Pies gives even 270-300 g. In the USSR, children lose 200-300 g, and in individual cases that do not go beyond the limits of physiology, the loss reaches 400 g. It is much more correct to evaluate the loss in percentages in relation to the total weight, and a drop of 6-9% can be considered physiological. While the absolute drop is more significant the larger the child, the relative drop (in percentages) is greater the smaller the child's weight. Probably the latter circumstance depends on the relatively larger body surface and, consequently, greater perspiration in small children. Antonov, however, finds the lowest percentage of loss in children with average weight. Physiological loss is more pronounced in children who have undergone significant trauma, causing lethargy, drowsiness, poor sucking, as well as in children of primiparous mothers. By early application to the breast and supplementary feeding of the child, this loss can be avoided or reduced to a certain extent (Schick, Kononova), however, this is already a certain imposition. The main cause of physiological loss is that the newborn in the first days of its life gives away more than it receives. The largest share (about 75%) falls on the loss of water through insensible perspiration, a small part on the loss of meconium and urine. The consumption by the newborn's organism of its own tissues, proteins, and mainly fats also takes place in the first starving days of life. But this forced starvation diet may also be useful, as it gives the digestive tract time to adapt to new functions for it (Reiss). Metabolism. Regarding metabolism in newborns, we know extremely little (Gundobin, Kocharovsky, Birk). Intensive for the entire first year of life—a period of intensive growth of the child—it seems to decrease somewhat during the newborn period. For nitrogen metabolism, it has been established that the absolute amount of excreted nitrogen is very large and increases every day. According to Kocharovsky's data: on the 1st day—131.17 mg, on the 2nd day—213.37 mg, on the 3rd day—272.87 mg, on the 4th day—304.42 mg, on the 5th day—425.60 mg, on the 6th day—423.52 mg. Most researchers found a negative nitrogen balance in the first days of life (excretion > intake), therefore large amounts of nitrogen excreted by the newborn have an endogenous origin—the burning by the organism of its own material as a consequence of starvation; primarily, the burning of fat takes place, and then obviously also a peculiar breakdown of tissues. The distribution of nitrogen in the urine is as follows: the urea coefficient increases during the first week (from 73% to 81%) and does not differ significantly from the coefficient in a healthy infant. The excretion of uric acid is absolutely and relatively quite large, especially in the first 3 days of life. Ammonia excretion is quite high, especially towards the end of the first week. The amount of amino-nitrogen acids is also significant in comparison with that in adults: in the first 3 days—5.8%, on the 7th-8th day—10-12%, while in older infants—2-5%. Niemann found the excretion of purine bases to be significant (2-7 mg), while Birk found them only in the form of traces. Some authors are inclined to explain the large amounts of uric acid and purine bases by the formation of uric acid from the cellular nuclei of decaying leukocytes. From the data on the distribution of nitrogen in the urine, it is evident that in newborns, there is an increased excretion of products of incomplete protein metabolism and that the breakdown of proteins occurs incompletely, perhaps due to the enzymatic insufficiency of the newborn's organism. The first days—days of starvation and physiological weight loss—are characterized by a negative water balance, and with the onset of a positive water balance, weight gain usually occurs (Birk and Edelstein). Gas exchange, somewhat lowered in the first hours after birth, soon begins to constantly and gradually increase. Its magnitude depends on the amount of food, the ambient temperature, the mobility or drowsiness of the child, clothing, etc. The respiratory quotient = 0.702, while in an adult it = 0.89. Regarding salt metabolism, information is extremely scarce. According to Birk, the lowest retention of salts occurs when feeding with colostrum. It is interesting that of the salts, phosphorus and lime, i.e., substances necessary for building the skeleton, are most retained and accumulated during the last months of intrauterine life. Chemical composition. Observations on the chemical composition of the newborn's body are still based on very small material and cannot be considered precisely established. Table 1. Per 100 g of body. Author: Michel... 3,335 g, 69.2% water, 11.75% protein, 14.0% fat, 3.4% ash. Camerer and Söldner... 2,821 g, 71.3% water, 12.3% protein, 11.7% fat, 2.7% ash. Klose... 3,202 g, 66.1% water, 17.6% protein, 11.9% fat, 2.9% ash. The body of a newborn is very rich in water and fats and poor in nitrogenous substances and ash. Water is over 70% (Camerer, Fehling), while in an adult it is 59% (Bischoff). Probably this extreme richness in water of the fetal organism (97.54% at 6 weeks) and the newborn should be brought into connection with the extreme energy of growth, for which an intensified metabolism is necessary; the high water content as a dissolving medium favors this. Of the dry matter, approximately half is fat, which accumulates mainly in the last 1.5 months of pregnancy. Anatomical-physiological features. Individual organs and systems of the newborn are marked by the following features. The skin is thin, delicate, elastic, covered with fine down (lanugo). Especially abundant in premature infants, lanugo is sometimes very abundant in full-term strong newborns as well. The epidermis and dermis are thin, the horny layer is poorly developed and easily desquamates. Sebaceous glands function actively, sweat glands are underdeveloped, the capillary network is rich, and capillaries are wider than in an adult. Hair is soft, thin, gradually falls out and is replaced by new hair. Its growth is probably under the influence of the endocrine-vegetative apparatus. Physiological erythema is a consequence of the rich blood supply to the skin, and perhaps also a reaction to the ambient temperature (Jaschke). "Cheesy" vernix (see Vernix caseosa) covers the child's body sometimes almost entirely, sometimes only in the folds, and is often completely absent. In some newborns, the skin is dry from birth, peels, and easily develops cracks in the folds and diaper rash. Sometimes the heredity of such skin can be established. Functionally, it should be noted that the intensity of skin respiration is higher in newborns than in adults (Camerer), namely: per 1 kg of weight per day, 29.5 g of water and carbon dioxide are excreted in newborns, while in adults it is 18.0 g. It is known that the relative body surface is larger the smaller the child, and therefore the newborn is in unfavorable conditions in terms of heat loss. Table 2. (According to Sychev.) 4-day-old premature infant: weight 2,097 g, body surface 2,129 cm², surface area per 1 kg of weight 1,015 cm². Newborn: weight 2,980 g, body surface 2,097 cm², surface area per 1 kg of weight 704 cm². 6 months: weight 5,138 g, body surface 2,961 cm², surface area per 1 kg of weight 576 cm². The subcutaneous layer in a full-term newborn is well developed, in premature infants—scant. By chemical composition, the fat of a newborn differs from the fat of an adult in that it contains less oleic acid and more solid fatty acids (palmitic, stearic), which easily solidify at lower temperatures. Edema of the extremities and suprapubic edema (oedema neonatorum) are often encountered even in healthy newborns.
It is possible that they are associated with greater permeability of the vascular walls due to their insufficient tone. Regarding the muscles, one must note their richness in water, reduced electrical excitability, and a known physiological hypertonia, especially pronounced in the flexors. The skeleton is distinguished by the relative size of the head and the relative shortness of the limbs. Many bones in the newborn are in the cartilage stage (spine, wrist). The bone tissue has a peculiar fibrous structure, is very rich in vessels, and the periosteum has a strongly developed inner layer rich in cells. The regenerative capacity of the bone is very great. Among the ossification centers, the importance of the nucleus that forms in the lower epiphysis of the femur shortly before birth is usually pointed out; with a diameter of 5 mm, it has significance in forensic medicine as a sign of fetal maturity. However, one can encounter such dimensions even in obvious premature infants, and Eparvier observed its complete absence in 8% of 102 full-term infants. The head is large, with a relatively large vault and a small facial part. According to Bumm: the large circumference of the head is 35 cm; the straight or fronto-occipital diameter is 12 cm; the large transverse (between the parietal eminences) is 9 cm; the large oblique (mento-occipital) is 13.5 cm; the small oblique is 9.5 cm; the transverse diameter of the shoulders is 12 cm; the transverse diameter of the pelvis is 8 cm. Other authors provide slightly different figures (see Maturity). The sutures—coronal, sagittal, occipital—are usually open and fuse by the 2nd-3rd month of life. The large fontanelle, with sharp overriding of the bones, can be very small, but is usually 1.5 x 2 cm; the small fontanelle is closed; in the place of the posterior-lateral ones, a pliability of the bone edges can be felt. Often, even in full-term, strong infants, significant defects in the ossification of the skull are observed, sometimes a true parchment-like state of the parietal bones (Weichschädel). Wieland observed this phenomenon in 20%, Arluck in 9.7% of all newborns. While some authors (Kassowitz, Marfan) see in it a symptom of intrauterine rickets, the majority consider it a congenital and possibly constitutional anomaly of the cranial vault, which quickly levels out in the first weeks of life. In the frontal and facial bones, the absence of sinuses should be noted. Configuration is the term for the change in the shape of the head due to the overriding of bones at the sutures and fontanelles depending on the pressure of the pelvic walls on the head. The occipital and frontal bones go under the parietal ones, one parietal bone overrides the other, and the head is elongated in the straight diameter posteriorly and superiorly. This misshapen form is further increased by the caput succedaneum. The configuration is more or less pronounced in connection with the dimensions of the pelvis, whether it is a first or subsequent birth, and is peculiar to each variety of head presentation (occipital, facial, frontal). The birth tumor, caput succedaneum (see), which is more or less sharply demarcated on the head, can be diffuse on the buttocks, arm, and face, which it particularly disfigures. On the lips and scrotum, blisters with serous or bloody fluid can form. The birth tumor resolves quickly in easy subsequent births, within the first few hours, and in more difficult ones, up to 2 days. The spine of the newborn is entirely cartilaginous and has only one general arcuate curvature; the limbs are also somewhat curved due to the intrauterine position of the child. The chest retains the features of the embryonic type: it is cone-shaped, the lower part is expanded, partly due to the large liver; the anteroposterior and transverse diameters are approximately equal, the direction of the lower ribs is almost horizontal, which seems to shorten the chest and limit its excursion. The brain is relatively large (ratio to body weight 1:7.5-8.5; in an adult 1:32). It is rich in water, on cross-section the differentiation of gray matter is barely outlined, the convolutions are flattened, and some sulci are not yet present—a "blank slate," in the expression of Kraepelin. The cortex, pyramidal tracts, and striate body are underdeveloped. Myelination is still far from complete. While the spinal cord of the newborn is rich in myelin, the hemispheres in many parts are still devoid of it (most of the parietal, frontal, temporal, and occipital lobes, the commissure). Myelination of the main systems of the hemispheres ends by the 8th month of extrauterine life, and of the pyramidal tracts by 2-3 months. The spinal cord descends somewhat lower than in an adult—to the lower edge of L2. Cerebrospinal fluid is usually in small quantity and under low pressure. It may contain blood in case of cerebral hemorrhages and is often colored yellow. This is physiological xanthochromia, which is not related to any pathology and is likely a consequence of the presence of modified bilirubin. Roberts (1925) detected bilirubin up to the 9th day of life. The Babinski reflex in the newborn is always positive; the glabellar reflex is obtained in the form of a contraction of the m. orbicularis when tapping with a hammer in the region of the glabella. The labial, oral, and corneal reflexes are present; the Achilles reflexes are inconstant, as are the cremasteric reflex, the abdominal reflex, the gag reflex, and the nasal mucosal reflex. Those reflexes that have their center in the spinal cord (such as the knee-jerk) are especially lively, due to the fact that the conducting pathways are sufficiently developed (except for the pyramidal ones), and also due to the underdevelopment of the inhibitory and regulatory centers in the brain (Gundobin). The centers for respiration and thermoregulation are also underdeveloped, and this causes a whole series of clinical manifestations, such as thermolability, irregular respiratory rhythms, and attacks of apnea.

Figure 1. Respiratory curves: a—in a state of sleep; b—in a state of wakefulness; c—during crying.
etc. The development of intracranial nerves and their myelination is completed only by the 3rd month, and that of the peripheral ones even later. Galvanic excitability is sharply reduced. As a natural consequence of these anatomical features, we have in the newborn an absence of higher psychic activity and a sharp predominance of reflex and automatic reactions. The lungs have a small capacity (35-45 cm3). The number of breaths in a sleeping newborn is 40-45; breathing is superficial, of the diaphragmatic type; the depth of breathing gradually increases. On the 1st day, the air exchange per minute is 1.13 liters; by the 3rd day, it already reaches 2 liters. During restlessness and crying, the irregularity of breathing becomes especially pronounced (Fig. 1): deep inhalations are replaced by a series of superficial respiratory movements and pauses. The first respiratory movement in the newborn is triggered by the irritation of the respiratory center due to the overloading of the blood with carbon dioxide. Temperature and mechanical irritation of the skin play a secondary role. In premature infants and in children who cry weakly, Vogt determined atelectatic areas in the lungs by X-ray for quite a long time. The heart is positioned more horizontally in the newborn due to the high position of the diaphragm. The cardiac impulse is in the 4th intercostal space, external to the nipple line. The weight of the heart is relatively high and equals 18.5-22.5 g (6.3 per 1 kg of weight; in adults, 4.84). There is no pericardial fat; the left ventricle (0.44-0.68 cm) is only slightly thicker than the right (0.34-0.44 cm). In terms of function, the vitality of the heart is remarkable. There are known cases of delivering live children by Caesarean section 15 minutes after the mother's death. Martin saw during an autopsy how the heart of a newborn was still contracting an hour after death. Pulse rate: 120-140 according to Filatov, 120-135 according to Seitz. No distinct difference between the pulse of boys and girls is observed. With an average rate of 120, a full circulation of blood occurs in 12 seconds, after 27 heart contractions (in adults, in 22 seconds). Embryocardia is characteristic, as systole accounts for 54.5% of the entire pulse period (in infants, 62.2%). Vessels. The lumen of the arteries in the newborn is relatively larger than in an adult. Capillaries are especially wide, and are even absolutely wider than in an adult, in connection with the organism's great need for oxygen. Conversely, the lumen of the veins is relatively narrow, approximately equal to the lumen of the arteries. Blood pressure is low and the lower, the weaker the child: according to Ney, on average 90 mm; 80 mm according to Trump; 59-64 according to Sladkov. With the beginning of pulmonary respiration, significant changes occur in the newborn's blood circulation, namely: 1) blood flow in the umbilical vessels ceases, 2) arterial blood is separated from venous, the ductus arteriosus (Botallo's duct) and the foramen ovale collapse, although their closure occurs later, and finally 3) blood rushes into the lungs—the pulmonary circulation unfolds. Regarding the blood, it has been established that there is no mixing of the mother's blood with the fetus's blood, and the hematopoiesis of the fetus proceeds independently; even in cases of leukemia and severe anemia in the mother, the composition of the fetus's blood is normal. Anemias in children of the first weeks of life are most often secondary (after hemorrhages). The blood of the newborn is distinguished by a high content of Hb (100-140%), an increased number of erythrocytes (5.5-7 million), and leukocytes. Table 3.—Summary table of Hb quantities in % in the newborn. Authors: 1st day, 2nd day, 3rd day, 4th day, 5th day. Schiff (Prague): 104.2, 132.3. Schiff (Budapest): 100, 130, 106. Perkin (Bern): 96.5, 119, 112. Lucas (USA): 135, 114, 114, 113. Starting from the 3rd day, the number of erythrocytes drops rapidly, and many authors link this phenomenon to the development of jaundice. Thus, Heimann found 93% Hb and 5.5 million erythrocytes in cases of severe jaundice, and 114% and 6-7 million erythrocytes in the absence of jaundice. Other authors deny this dependence. In the first days, and especially in the first 24 hours, nucleated erythrocytes are found in large quantities—according to Lippmann, 500 per 1 mm3 after 12 hours of life and 277 after 24. The number of leukocytes is sharply increased ('physiological leukocytosis') and has the character of neutrophilia. Starting from the 3rd day, the number of polynuclear cells decreases and the number of lymphocytes begins to increase, i.e., the ratio characteristic of an infant is established (see Leukocytosis). The alkalinity of the blood is reduced at birth, decreases further in the first days, and only at the end of the first week does the amount of OH ions begin to increase. The viscosity of the blood in the newborn is significantly higher than in an adult. Regarding the resistance of erythrocytes, there is very little information in the literature; an increase is noted, especially sharp in children with physiological jaundice. According to Frank, the child's blood is finally established in terms of individual forms no earlier than the 14th day. Büngeler and Schwartz reached peculiar conclusions based on a study of 330 newborns: blood from the umbilical cord is similar to the blood of an adult; changes occur during and after birth; their degree is in direct dependence on the duration and severity of labor, and the blood picture corresponds to what is observed during the parenteral administration of proteins or blood to animals and humans. This 'birth crisis' in the blood of the newborn is a consequence of the resorption of blood and protein substances as a result of birth trauma. In general, the blood picture confirms the fact that in this early period of life, major changes occur in the child's organism and that it only gradually arrives at the state of equilibrium necessary for the further proper development of the child. The kidneys in the newborn retain their fetal lobulated structure ('bear's', 'pig's') and are twice as heavy relative to body weight as in an adult: the weight of both = 23 g. The ureters are tortuous, in places dilated; the capacity of the bladder is 50-60 cm3. On a cross-section of the kidney, one can often observe the deposition of salts in the form of uric acid infarcts (see Uric acid infarct), which are encountered most often from the 2nd to the 5th day of life. In cases of jaundice in the newborn, a bile infarct consisting of bilirubin crystals can be deposited in the papillae of the medulla. Urine is usually present in a small amount at birth; its first portion is light and colorless; soon the urine becomes more intensely colored and becomes cloudy upon standing. The amount of salts is especially large during the period of greatest weight loss. The reaction of the urine is sharply acidic at first, and then becomes weakly acidic. Specific gravity is 1.006-1.012 on the 1st day, 1.008-1.013 on the 2nd-4th, then gradually falls to 1.003-1.004. On the first day, anuria is possible, which disappears with the beginning of fluid intake. The daily amount of urine also gradually increases (see). Protein is often detected in the urine, usually in the form of traces. French authors consider albuminuria in the newborn a rarity, a pathology, while German and Russian authors detect protein very often (Reuss, Flensburg in 100% of children) and do not attribute pathological significance to it. In general, one may think that albuminuria in the newborn is a physiological phenomenon, the causes of which are still unknown (see Albuminuria). Besides protein, Henckinger observed the excretion of sugar in the urine for several days in children delivered with forceps, which is not confirmed by observations of the Institute for the Protection of Motherhood and Infancy of the People's Commissariat of Health. Bilirubin is found in the form of a precipitate ('masse jaunes'), and in cases of pathological jaundice, also in a dissolved state. Traces of bile pigments are obviously encountered quite often even in physiological jaundice; sometimes urobilin and indican were found (Reuss). Of the urine enzymes, pepsin and rennin (labferment) are indicated; trypsin, maltase, and diastase were also found. In the sediment: epithelium of the urinary tract, a few leukocytes, isolated erythrocytes and shadows, occasionally hyaline casts and casts with salt deposits. The digestive tract of the newborn is equipped with everything necessary for its beginning function. Sucking is a reflex act, occurring without the participation of the brain, and is observed even in anencephalics. The sucking reflex is obtained from the irritation of the mucous membrane of the lips by the mother's nipple. For this important act, there are special adaptations in the newborn's mouth in the form of the 'Bichat fat pad,' embedded in the thickness of the cheeks to maintain their tone, and in the form of so-called 'accessory lips'—suction-like protrusions on the free edge of the gums. 'Sucking pads'—radial folds of macerated, pale mucous membrane of the lips—hardly help with sucking. The orbicularis oris muscle is well developed; the oral cavity is somewhat dry. The salivary glands function, but insufficiently. The presence of ptyalin is proven not only in the newborn but also in the fetus. The capacity of the stomach in the newborn is small—30-35 cm3—but it increases rapidly. Characteristic are the absence of a fundus, a somewhat more vertical position, weakness of the gastric sphincters, and increased sensitivity of the mucosa (frequent regurgitation). Motor and secretory functions are well developed; the gastric juice has all the components of an adult's juice, but its strength is weaker. The reaction of the gastric juice is acidic due to the presence of free HCl. According to Vogralik, the reaction is neutral only in the first minutes of life. The first stimulus for the secretory activity of the stomach glands is the amniotic fluid swallowed by the child, and the first process of digestion begins about 25 minutes after birth. Enzymes are present not only in the newborn but also in the fetus. Ibrahim found, in addition to rennin (labferment) and pepsin, a very active lipase.
The intestine of the newborn is relatively longer than that of an adult, but it is impossible to give exact figures, as measurement presents great difficulties: its length is from 2 to 4 m or is equal to the body length multiplied by 5, according to Marfan, or even by 8, according to Schwan. According to Pirquet, the length of the intestine is equal to ten times the Sitzhöhe. The significant length and rich blood supply indicate the important role of the intestine in the young organism. The glandular and lymphatic apparatuses are well developed, the muscular layer is insufficient. The permeability of the intestinal wall to antitoxins has been proven experimentally (Ehrlich, Salge, Bertarelli), and Calmette bases his anti-tuberculosis vaccination on the property of microbes to pass through the intestinal wall. At birth, the intestine contains 70-90 g of meconium, a thick, viscous, dark olive mass, on the first portion of which one can notice the so-called "meconial plug"—a dense mucous formation consisting of secretions from the lower sections of the intestine (see Stools). On the 2nd-3rd day, the stools acquire a mixed character and are replaced by a dark brown hunger stool. In subsequent days of life, they are often liquid, contain mucus and curds ("dyspepsia" of the newborn, "transitional catarrh"). Yellow breast-fed stool is established only later. The liver is comparatively large, always protruding about 3 cm from under the costal margin. Its absolute weight is about 130 g, relative 1:18 (in an adult 1:35). By weight, it is the second organ after the brain in the newborn. The glycogen-forming function is already present in the fetus; bile differs somewhat in composition from the bile of older children. In its functions, the liver is initially imperfect, and its ability to neutralize poisons is reduced. It is rich in vessels and poor in connective tissue elements. Of the hematopoietic organs, the spleen is relatively large, although it is not normally palpable; its weight is 8-10 g. The bone marrow is rich in formed elements and has the character of "red" marrow. The lymphatic glands are distinguished by the delicacy of the capsule, the width of the sinuses, and are rich in blood. In the vast majority of newborns, the peripheral glands are accessible to palpation, especially the axillary ones. Relatively little is known about the glands of internal secretion. Thomas thinks that they do not function in the fetus, reach full development shortly before birth, and begin to function shortly after. Maslov believes that in the newborn, the interrenal system and the germinal glands are the most active. As for the thymus gland, even data on its weight fluctuate sharply from 2 to 25 g (Hammar—13.26, Sokolov—4.8 g). The development of this gland can be very different; sometimes it consists almost entirely of lymphoid tissue, sometimes with a large admixture of connective tissue. Recently, an endocrine function has been attributed to it. The weight of the adrenals relates to the weight of the kidney as 1:3 (in an adult 1:8-1:28). Consequently, they are very large, especially if one remembers that the kidney in the newborn is also relatively large. The structure has an embryonic character; the medullary substance functions insufficiently (Thomas). However, in cases of hemorrhage in the adrenals, their acute insufficiency leads to sharp adynamia. The weight of the thyroid gland is 1.3-2.8 g and subsequently increases until old age. In the fetus, there is apparently no independent function of the thyroid gland, but the mother's gland is in a state of hyperfunction, and the supply to the newborn is likely at the expense of the maternal organism. The reserve of colloid in the first months of life can be replenished through the mother's milk. The reproductive apparatus of boys presents a number of features: the inner surface of the praeputium is fused with the surface of the glans penis by means of a multilayered epithelium. The name "newborn phimosis" does not correspond to reality, and this physiological adhesion would be more correctly called, according to Kalashnikov, "symphysis." It disappears over time. In girls, the lumen of the vagina is filled with desquamated epithelium and mucus, which often forms a real plug. The ovaries are at different levels, most often still in the greater pelvis. Their weight, like that of the male testicles, fluctuates around 2 g (see Ovaries). The sensory organs are sufficiently developed in the newborn. Regarding the eyes, one should note the absence of pigment in the iris; hence the indefinite bluish-gray color observed even in such pigmented races as Negroes. The lacrimal glands are developed, but crying is for the most part not accompanied by lacrimation, possibly due to the absence of a central impulse. The pupillary reaction is present, as is the corneal reflex, although somewhat weakened. Moving the palm in front of the eyes does not cause blinking as a startle reaction, as a psychoreflex. The newborn possesses light perception, but not a fine sense of vision. The ability for coordination is absent, which explains the converging movements of the eyes. Hearing is obviously absent immediately after birth, as the tympanic cavity is only gradually filled with air due to the onset of pulmonary respiration. Already in the first days, the newborn reacts to loud noises, but he learns to distinguish the direction of sound only after several weeks. The sense of taste is one of the most developed. Preyer observed it even in an anencephalus. Smearing the tongue of a newborn with a saline or quinine solution causes the corresponding facial expression. It must be thought that the sense of smell is absent immediately after birth, as the nasal cavity was filled with fluid for a long time. However, by the end of the first day, the sense of smell appears. The sense of touch is well developed; touching the lips causes a sucking reflex, tickling the nose causes sneezing, etc. Pain sensations are dulled and the reaction to pain is slowed. Sensitivity to temperature is quite developed, and it may be that cooling causes the first cry of the newborn, which is apparently reflexive, as it is also observed in anencephalics. Higher psychological functions are absent in the newborn, but simple experiences—pleasant, unpleasant—which can be detected very early, already belong to the realm of conscious, albeit primitive, ones. The study of the behavior of the newborn will undoubtedly reveal much of interest in the near future. The mortality of newborns is very high and is higher the younger the child is. Zeltner in Nuremberg gives the following figures for 1923-24: out of 100 infants, 15.3 died on the 1st day, 21 from the 1st to the 3rd day, 26.5 from the 1st to the 7th, and 32.4 from the 1st to the 14th. During the years 1921-24 inclusive, 19,799 children under one year of age died in Leningrad; of them, 6,495, i.e., 32.8%, died at the age of under one month (Shuster-Kadysh). According to information from Schrenk (Riga), out of the total number of deceased infants, the following died (in %): Table 4. Day of life 1909 1910 1911. 1st... 9.75 8.34 7.36. 2nd... 1.95 1.53 2.61. 3rd... 1.67 0.96 1.04. 4th... 0.80 0.91 1.04. 5th... 0.80 0.85 0.81. 6th... 0.63 1.08 0.76. 7th... 1.21 1.36 1.10. The high mortality falling on the 1st day of life should be attributed, on the one hand, to the vital weakness of children with low weight, and on the other, to birth trauma, which usually falls on very large children. Children with average weight perish in a smaller ratio. A certain predominance of boys is probably explained by their greater weight. The figure for "mortality of the 1st day" is the highest—it immediately and sharply decreases already on the 2nd day, and with each subsequent day, the child's chances of survival increase. Only on the 6th, 7th day is a certain increase observed, already in connection with mortality from infections (umbilical, intestinal, pulmonary, sepsis). In the USSR, the general mortality in the 1st year of life has decreased since 1923, but the mortality relating to the first days of life does not show this decrease. Obviously, the rate of decline in mortality in the first month, even under favorable conditions, is still somewhat slower than at the age after the first month (Dublin). Birth trauma, prematurity, and infection are the three main factors of newborn mortality, and from this, the enormous role that intra- and antenatal prophylaxis (correct organization of obstetric care, a wide network of women's consultation centers, correct treatment of syphilis, measures of a eugenic nature), as well as a careful, aseptic approach to the child, must play in the fight against it is understandable. Care and hygiene. The separation of newborns from mothers, which is widely practiced at the present time, was a real revolution in obstetric institutions when it was introduced. This measure is correct provided that the matter is rationally organized, there is a sufficient number of personnel, and they are well trained. A spacious, bright nursery, preferably two, at a distance from the maternity wards, well-ventilated and heated, high-type cribs (101 cm in height by 46 cm in width) with hair mattresses, Credé warmers for premature infants, boxes for the isolation of the sick, closed buckets for dirty diapers, continuous supply of hot and cold water, a sufficient quantity and proper quality of linen, careful numbering of children, and personnel sufficient and trained in the spirit of Okhmatmlad—these are the conditions without which a large gathering of children can have disastrous consequences. Care for the newborn begins from the moment of his exit from the birth canal and has as its goal the protection of the child from all kinds of harmful factors of extrauterine life (traumatic, thermal, microbial), as well as helping him with the difficulties of feeding. The separation of the newborn from the mother is carried out by cutting the umbilical cord after tying it or clamping it like a bleeding vessel (omphalotripsy).
It is customary to separate the child 6-7 minutes after birth, when the pulsation of the umbilical cord weakens, in view of the usefulness of such a transfusion of placental blood for him. Usually, the umbilical cord is tied with a sterile thin tape or thick silk at a distance of 1-2 cm from the umbilical ring. A second ligature is applied slightly higher, and the umbilical cord is cut with sterile scissors above the first. A short stump is preferable to a long one, as it presents a smaller surface for infection and mummifies faster. The so-called "two-stage" ligation, used in many German clinics, is advisable. When tying the tape, it is tied tightly in a bow, and after the toilet of the child it is re-tied.
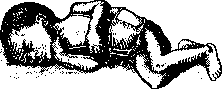
Figure 2. Flick's umbilical apron.
is tightened to avoid bleeding. The stump can be smeared with iodine and covered with gauze moistened in alcohol. Subsequent care consists of daily inspection and the application of a dry sterile dressing. Individual packets with a bandage and a piece of gauze are convenient, as are Flick's umbilical aprons, which protect the umbilical cord with a gauze shield on strings (Fig. 2). After the umbilical cord falls off, the umbilical wound is smeared with iodine and covered with a sterile dressing until it heals. Another aspect of care is Credé's eye prophylaxis (see Blennorrhea), which is mandatory during childbirth. It should be applied as early as possible. Recommended are: 1% silver nitrate (lapis), 10% protargol, and 5% sophol; the latter two preparations are milder and do not cause a sharp reaction from the child's conjunctiva. A whole series of precautions should be observed: keep the preparation in a dark brown vial with a ground-glass stopper, prescribe it for the institution in small quantities, and do not wash the child's eye after instilling the preparation in order to avoid washing it out. After the indicated prophylactic measures, the child's body is wiped clean of vernix caseosa with sterile oil using a piece of cotton wool or a soft sterile diaper (regarding leaving the vernix, see Vernix caseosa). Then a bath is given at 37-38°C using boiled water with the use of mild neutral soap (Marseille, egg soap). At the present time, some institutions prefer to replace the bath with wiping the child's body with oil due to the possibility of infection and cooling. It must be said that this fear is exaggerated, and provided the bath is kept clean, boiled water is used, and good technique is employed, a single bath is more advisable. After the toilet, the dressing on the umbilical cord should be tightened, bandaged, and the child dressed. All manipulations must be performed quickly and precisely so as not to cause cooling of the newborn. In the first hours (before the first feeding), it is advisable to wrap him with his arms and head covered, since his body temperature during cleaning still drops and only gradually returns to normal. Then, if the room temperature is good (20°C), one can put on a shirt, a jacket, a diaper, and, having wrapped him in a diaper under the armpits, cover him from above with a warm blanket with a duvet cover—the head is open, the arms are free. For the time of feedings, it is more convenient to wrap the newborn with the head and arms covered. The linen should be soft, well-ironed, and diapers should be made of absorbent fabric—best of all, gauze—in 4-8 layers. Morning toilet: every morning the newborn should be undressed, carefully examined, his face and hands washed with boiled water, and all skin folds washed and dried. If they are carefully dried and smeared with oil once a day, one can completely avoid the use of powder (talc), the quality of which is often poor. Then follows the washing of the eyes with boric acid, changing the umbilical bandage and inspection (without touching) of the umbilical cord, changing the linen, and combing the child. The nose (only in case of crusts, wheezing breathing) is wiped with a cotton swab with oil. The latter procedure should not be abused, especially during mass cleaning. The auricles are wiped with damp cotton wool and dried, and long nails are carefully trimmed while the child is asleep. The question of whether a newborn should be systematically bathed before the umbilical cord falls off is resolved by the majority of observers in the negative. Two reproaches are leveled against the bathing method: longer mummification of the umbilical cord and the possibility of its infection (see Omphalitis). Taking into account the constant contamination of our water, as well as the fact that dry maintenance of the umbilical cord is preferable for faster mummification, it will be correct to bathe the newborn only after the umbilical cord has fallen off. The child's oral cavity does not require any special care, as it is sufficiently washed by his saliva. Wiping can be harmful due to the great tenderness of the mucous membrane and can itself be the cause of injuries and diseases of the mouth. The use of air should be carried out from the very beginning of the child's life; this includes mandatory airing of the room several times a day, opening the transom or window in summer, and walks in accordance with the season and air temperature: in summer from the very first days of life, in winter more cautiously—after 3-4 weeks and only on warm days. In conditions of summer heat, when newborns easily overheat, it is advisable to give them air baths, leaving them undressed 1-2 times a day for 5 minutes. The use of light gymnastics, recommended by some doctors, is not considered desirable by the majority in this early period of life. Feeding. The nutritional requirement of a newborn is lower compared to an older child. His proper weight gain occurs with a much lower energy coefficient: 50-44 and even less if the volume of food, i.e., the amount of water, reaches a certain value. Finkelstein gives the following scheme: in the 1st week of life, a newborn needs 70 g multiplied by the number of days minus 1; for children weighing more than 3,200 g—80 g multiplied by the number of days minus 1. Kirstein's scheme takes into account the child's weight more accurately: on the 2nd day of life, he should receive 3-4% of his initial weight, on the 4th—8-9%, on the 6th—10-11%, on the 8th—12-13%, and on the 14th day—15%. Corresponding to this small requirement, as well as the state of sleep in which the newborn remains, the French school, as well as Reiss, do not put him to the breast at all in the first 24 hours or put him to it several times without definite intervals, guided by the child's waking time (Jaschke). This interval is also needed for the mother's rest. Other authors have observed large drops in weight and recommend early, and some even very early, application to the breast (Schick, Kononova). Vogralik considers feeding a newborn on the first day of life with another mother's milk to be a violation of nature, and Ivanova-Neznamova (Tomsk) observed that children put to the breast after 12 hours lost a greater percentage of weight than those who were put to it only 24 hours after birth. At the Moscow State Scientific Institute for the Protection of Motherhood and Infancy (Okhmatmlad), after various trials, they settled on the first application to the breast 8 hours after physiological labor and 24 hours after difficult labor, anesthesia, forceps, versions, etc. It is advisable to give the child a little boiled water at this time. After a cesarean section and in cases of eclampsia, it is often necessary to start breastfeeding even later. Premature infants, as children for whom a significant loss in weight is undesirable, can be fed earlier—after 6 hours. The number of feedings is also a controversial issue. In France, they willingly feed 7-10 times; they also use the following method: on the 1st day of life one feeding, on the 2nd—two, on the 3rd—three, on the 4th—four, on the 5th—five, on the 6th—six, and finally from the 7th day, a seven-time feeding schedule is established. In Germany, many conduct 5-time feeding every 4 hours with an 8-hour night break. Such infrequent feeding leads to large weight losses, and in the Institute of the People's Commissariat of Health, 6-time feeding (every 3.5 hours) is used as the most rational in institutional conditions. In an individual setting, 7-time feeding is preferable, which is practically difficult to implement in an institution. 10-time feeding is applied to smaller children (2,600 g and below). The duration of feeding is 15-20 minutes, no longer than half an hour for lazy suckers. In case of maternal hypogalactia, especially temporary, the newborn is sometimes prescribed more frequent, and sometimes mixed feeding, which also has to be resorted to in case of postpartum diseases. The choice of mixture depends on the individual conditions of each separate case: in the absence of breast milk—buttermilk, protein milk, Czerny's mixture, ordinary dilutions with water, decoctions. Finally, artificial feeding is also used in those rare cases when the death or serious illness of the mother occurs: active forms of tuberculosis, decompensated heart defects, chronic nephritis, psychoses, severe postpartum diseases. The doctor's task is to delay this transition to artificial feeding as much as possible, remembering that newborns are especially vulnerable and that every extra day of breastfeeding increases their chances of life. However, one should not insist too much in hopeless cases and bring the child to exhaustion. A common mistake is underfeeding the newborn, not overfeeding him. Finkelstein considers the main rule to be the full coverage of the child's nutritional needs, and in this sense, one must condemn those large dilutions on which newborns are sometimes kept for a long time, justifying this by their great fragility. One should not use a 1:2 dilution at all, or perhaps only prophylactically for one or two days, and then give 1:1 and even 2:1. Varlot successfully prescribes whole milk to newborns. No more than six meals, with a cautious addition of sugar in view of the possibility of fermentation processes. During the 1st week, 80 calories are sufficient, in the first days even less, but on the 2nd week, this amount should be raised to 100 and then 120. If the child gains little, the caloric content can be increased by adding fat (10% cream, butter), Larosan, or by increasing the percentage of sugar. Good results have also been obtained from other mixtures—Larosan, Feer's protein-cream mixture, buttermilk, Czerny's mixture, although mixtures rich in fat require careful use in the first weeks of life. The most suitable for a healthy newborn are, after all, ordinary milk dilutions.
Birth injuries. For every child, the act of birth, even a physiological one, constitutes a severe trauma, and a more or less pronounced concussion of the brain (commotio) is observed in the majority of children in the form of great drowsiness and mild vomiting, which may be partly of cerebral character. Furthermore, injuries also occur—from the mildest to those fatal to the child. They can be observed during any birth, both normal and rapid, precipitate ones, when the child's body is expelled without sufficient preparation and experiences a sharp difference in ambient pressure. Especially dangerous are prolonged labors, those with a narrow pelvis, breech presentations, and operative ones—versions, forceps, especially high ones. Injuries can be to the skin and soft parts; petechiae, small ecchymoses, testifying to the fragility of the child's vessels; traces of forceps blades, superficial or deeper (Pinard calls them the 'clinic's stamp'), injuries to the oral mucosa, tears of the frenulum when inserting a finger into the mouth to extract the head. In breech presentation—abrasions, bruises of the buttocks and genitals. Among muscle injuries, hematoma of the sternocleidomastoid muscle is encountered, forming a tumor under the muscle sheath. Its trauma occurs 1) during compression of the child's neck with fingers during the Mauriceau maneuver, 2) during the application of forceps, 3) in cephalic presentation, when the already emerged head is pulled downward to free the shoulders. It is clear that in the first cases, hemorrhages into the thickness can occur due to direct pressure, and in the latter, due to forcible stretching of the muscle (tears). With significant tears of muscle fibers, torticollis may sometimes form due to the muscle being overgrown with fibrous tissue; usually, however, the tumor resolves within 1-3 weeks. Treatment: after the umbilical cord falls off, baths, light massage, and in case of persistent torticollis—surgical intervention. Regarding the skeletal system, fractures are observed mainly of the upper girdle—the clavicle and humerus. Clavicle fractures are not rare (from 1.3 to 3% of all births), but often go unnoticed, as they may not cause limitations in movement. Fractures are often encountered even in normal births. In cephalic presentation, the fracture occurs during the freeing of the shoulders or when, upon exit, the anterior shoulder is pressed against the symphysis; the clavicle at this time is compressed in the direction of its longitudinal axis and breaks from bending at the weakest point—at the border of the middle and outer third; in breech births—during the Mauriceau maneuver. Usually, union occurs quickly—in 5-6 days. It must be a rule to always palpate the clavicles in the newborn; crepitus, and sometimes displacement of fragments, establish the diagnosis. Treatment: the arm bent at a right angle is wrapped in cotton and fixed with a bandage to the chest, with a pad in the axillary cavity—a Desault-type bandage. Spitzy recommends a cross-shaped splint. In the case of a subperiosteal fracture without displacement, a bandage is unnecessary.—Fractures of the humerus are comparatively rare, occurring sometimes in cephalic presentation, but more often in breech presentation with extended arms, at the moment of their reduction. The bone usually breaks near the middle, the fracture line is oblique, and the fragments can be displaced. Diagnosis is easy: the limb is immobile, crepitus and mobility of the fragments are clear. The course is mostly favorable, much less prolonged than in an adult. Union in 10-12 days with the formation of a large callus. The best method is the application of a rectangular Spitzy splint. It is cut from cardboard, wrapped in cotton, and placed under the child's back so that the shoulders lie on its horizontal part, and the forearms on the vertical parts. To achieve traction of the fragments, the child is fixed to the crossbars of the crib by means of bandages encompassing his elbows. He is fed the first days with expressed milk, and then by the mother's breast, who leans over
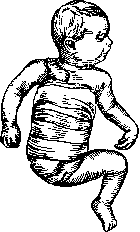
his crib. After 12 days, the splint is removed and replaced with a light bandage; after 14 days—baths, light massage, and passive movements in the joints.—Fractures of the forearm, dislocations, and separation of the humeral epiphysis are a great rarity. Fracture of the femur is observed in its upper or middle part, most often during pelvic extraction, but sometimes during spontaneous births and in cephalic presentation [see separate table, Vol. XX (art. 455-456), fig. 8]. The divergence of fragments can be significant—the upper in abduction, the lower in a position of adduction. Diagnosis is easy due to the complete absence of active movements, sharp mobility, and crepitus of the fragments. The fracture is serious, but union still mostly occurs well and shortening of the limb is rare. Many methods and apparatuses, more or less complex, have been proposed for the treatment of the fracture. One of the old methods: the broken limb is bent at the hip joint and bandaged to the child's body so that the fingers end up at his shoulder (fig. 3). The child's body forms a kind of splint. Plaster casts, aluminum and iron splints, etc., are used. The best results are given by suspending the leg upward with the help of a pulley (figure 4).
Fractures of the cranial bones are extremely rare due to their great elasticity and mobility in the sutures. Depressions are more common, localizing mainly on the parietal, sometimes on the frontal bones. The cause is pressure from the promontory in a narrow pelvis (especially in breech presentation) or by the blades of forceps. They are of various shapes (spoon-shaped, funnel-shaped, triangular, etc.) and proceed mostly favorably, as the bone of the newborn is resilient and elastic and often corrects itself spontaneously. Only deep depressions can cause cerebral phenomena in the form of convulsions, paralysis. Depressions can also be combined with cracks in the bone. Treatment in the absence of cerebral phenomena is expectant. In threatening cases, and sometimes later for cosmetic purposes, one tries to correct the bone depression, to push it out from the inside with a probe inserted into the suture, between the bones, or to lift it from the outside. Fig. 3. Bandage for a fracture of the femur.

Figure 4. Suspension
of the leg in case of a fracture of the femur.

Fig. 5. Peripheral paralysis of the facial nerve.
with a special instrument that screws into the bone like a corkscrew and pulls out the depression like a cork. Traumatic injuries of the peripheral nervous system lead to the formation of so-called obstetric paralyses. Most often during birth, the facial nerve and the brachial plexus are affected. Paralysis of the facial nerve occurs most often from its compression by the blades of forceps, sometimes from pressure of the promontory on the parotid region (peripheral paralysis), and finally, in rarer cases, it can also be of central origin due to intracerebral hemorrhage or underdevelopment of the nuclei of the facial nerve—so-called nuclear aplasia (Kernaplasie). The clinical picture is characteristic: when crying, the face is twisted to the healthy side, and the affected side remains immobile, often the eye does not close (peripheral paralysis of the upper and lower branches) (figure 5). The folds of the face, such as the nasolabial and frontal, are more sharply expressed on the healthy side when crying. The course of peripheral paralyses is usually favorable, sucking does not suffer, and recovery occurs spontaneously. After 3 weeks, one can try electrical stimulation. Paralyses of the upper extremities from compression or stretching of the brachial plexus are often encountered (fig. 6). This happens either during the Mauriceau maneuver (pressure) or during forcible pulling of the already emerged head downward, with the aim of freeing the shoulder (stretching, tears). With the latter maneuver, one should be as careful as possible. Paralyses usually develop during difficult births, in large children with broad shoulders, or during operative interventions. The limb hangs more or less immobile, the shoulder is lowered, the whole arm is slightly turned inward, and the palm is turned backward. The joints of the wrist and fingers are bent, the thumb is tucked inward. This is the most common type of upper plexus paralysis (Duchenne-Erb), in which the V and VI cervical roots or their joined trunk are affected. Another type, less frequently encountered, is lower plexus paralysis (Klumpke type), when the VIII cervical and I thoracic roots or their joined trunk are damaged. In this case, movements of the wrist and fingers (ulnar and radial nerves) usually suffer, while movements in the shoulder and elbow are usually not impaired. The prognosis is always serious, as treatment can be

Figure 6. Paralysis of the right plexus brachialis. Long-lasting—from several weeks to a year. Paralysis from stretching and tearing of nerve fibers has a more severe course than paralysis from pressure. Diagnosis must exclude fractures and detachment of the diaphysis of the humerus. Treatment in the first week is heat and rest, then light massage, baths; after 3-4 weeks—electrization. Passive movements in the joints are essential to avoid stiffness. Sometimes later, they resort to suturing nerves and excising scar tissue.—In concussion of the brain, the phenomena may sometimes be weakly expressed, and sometimes present a picture similar to the picture of cerebral hemorrhages. However, usually the clinical symptoms (convulsions, clouding of consciousness) quickly subside, the child begins to suck, and everything returns to normal by the 3rd or 4th day. "Hemorrhages must be placed in the first place among injuries in the newborn, both in terms of their frequency and the number of severe cases leading to disability and death of the child. The main cause is, of course, mechanical—the discrepancy between the dimensions of the child and the dimensions of the mother's osteo-tissue canal. Causes of a traumatic nature include rough methods of resuscitation of the newborn, among which, in the first place, one must place the Schultze swinging method. Not only Russian, French, but also German pediatricians oppose their use. The Sylvester method, harmless in itself, can also be harmful to the child if applied incorrectly and carelessly (see Asphyxia). The second cause is the great fragility of the vessels, that 'readiness for bleeding' ('Blutungsbereitschaft'), which characterizes the newborn, especially premature ones, which yield the highest percentage of severe hemorrhages. Finally, a condition favoring hemorrhages is the venous congestion that is created in the presenting part during the act of labor. Mild hemorrhages, which do not affect the general condition of the child at all, include petechiae, subcutaneous ecchymoses, hemorrhages into the sclera of the eyes, and into the muscles. A somewhat more serious hemorrhage is cephalohematoma (see) and finally, hemorrhages into internal organs—lungs, liver, adrenal glands, brain—must be classified as severe. Hemorrhages into the liver occur either during difficult labor or—much more often—during rough resuscitation of the child. If Glisson's capsule ruptures, blood flows freely into the abdominal cavity, and the child dies with symptoms of internal hemorrhage. Hemorrhages into the adrenal glands—most often during difficult breech births—present a picture of prostration of the child with pallor and a thready pulse. He reacts sluggishly to manipulations, does not cry. Death occurs quickly, in the first hours or days of life. Cases of intravital diagnosis have been described, when an adrenal hematoma was palpable through the abdominal wall and could even be operated on (Thomas). Hemorrhages into the brain are the cause of death in approximately one-third of stillborn children. Contributing causes: narrow pelvis, tight tissues, surgical interventions (especially high forceps), large size of the head, and especially prematurity of the fetus (Reuss). However, hemorrhages also occur during spontaneous and subsequent births (about 50% based on data from the State Scientific Institute for the Protection of Motherhood and Childhood of the People's Commissariat of Health). The mechanism of hemorrhage is obviously different. Sometimes, due to the overriding of the cranial bones over each other, the transverse and superior sagittal sinuses are compressed, and the veins draining into them are bent and can rupture. Sometimes, especially during rapid, forceful extraction of the head, the tentorium cerebelli with the veins embedded in it is ruptured. Reuss believes that the cause of the rupture of the tentorium cerebelli is the compression of the skull from temple to temple, while Stoeckel points to improper protection of the perineum. Small ruptures may not produce any significant hemorrhages and may scar over. Most often, cerebral hemorrhages are subdural. Their clinical picture can be very diverse. General clonic convulsions, initially agitation and lack of sleep, then clouding of consciousness, occasionally nuchal rigidity, bulging of the fontanelle, respiratory disorders, slowed pulse, and frequent yawning. The phenomena may gradually increase if the bleeding continues. Diagnosis is often difficult, as brain contusion (commotio) often presents an analogous picture, and it is often impossible to diagnose the localization of the hemorrhage. Lumbar puncture yields bloody fluid, especially in cases of low-lying (subtentorial) hemorrhages. The prognosis is always serious, especially for hemorrhages located low, in the region of vital centers. Small and favorably located hemorrhages can undoubtedly be resorbed. In terms of long-term consequences, the development of hydrocephalus, porencephaly, hemiplegia, etc., is possible, and they especially point to the connection of hemorrhages with Little's disease. Prevention of hemorrhage consists of the correct conduct and acceleration of the act of labor in cases of threatened asphyxia in the child as a factor causing venous congestion and hemorrhages. Careful resuscitation of the child, by no means according to Schultze. Later—rest, ice on the head, narcotics (chloral hydrate, luminal, bromine), careful feeding, and lumbar puncture, especially with symptoms of increased cerebral pressure. Some authors (especially American ones) successfully use trepanation for subdural hemorrhages in the anterior cranial fossa (Henschen). Hemorrhage into the spinal cord is encountered rarely during difficult breech extractions of the child. Physiological jaundice, 'reactions to pregnancy', dyspepsia of the newborn, 'transient fever'. A whole series of conditions is characteristic of the newborn, which are regarded by some authors as pathological, but which, according to modern scientific views, should be classified as the physiology of this period. These are: jaundice of the newborn, phenomena of the so-called 'sexual crisis', dyspepsia or transitional catarrh, and 'transient fever' of the newborn. Phenomena of physiological jaundice are observed in the vast majority of newborns (see Jaundice, jaundice of the newborn). Phenomena from the sexual sphere are also observed extremely often. The French give them the name 'sexual crisis' and place them in parallel with those phenomena that are observed at a later age during the period of puberty. This includes swelling of the mammary glands, characteristic of approximately 90% of full-term newborns. This phenomenon is incorrectly given the name mastitis, since there is no inflammation of the glands here. With great swelling, the skin becomes taut, shiny, and the milk ducts are dilated. Upon pressure, colostrum is easily expressed from them, similar in its appearance and composition to the colostrum of pregnant women. Reuss observed secretion even in the 3rd month of life; it lasts especially long with suction or squeezing of colostrum from the breast. Basch observed a parallelism between the intensity of swelling of the mammary glands in the infant and the richness of milk secretion in the mother. Any treatment is completely unnecessary. One should especially avoid the favorite practice of squeezing out the milk, which is often the cause of infection. With very large swellings, when the ducts are gaping and can be more easily infected, it is advisable to protect them with a sterile, slightly compressive bandage. True mastitis, i.e., inflammation of the mammary gland with the formation of pus, is a complication of the physiological process of swelling. As for the sexual apparatus of girls, the lumen of the vagina is filled with desquamated epithelium and mucus; the discharge is sometimes quite abundant, the labia majora and minora are edematous and swollen. All these phenomena are called vulvovaginitis of the newborn. At birth, the discharge turns out to be sterile (Shiryaeva-Rodionova, Smorodintsev and Gumakova, Meeserova), but soon it already contains various microbes: staphylococci, Escherichia coli, streptococci, etc. Various types of bacteria entering the vagina from the vulva probably die off quickly here due to the high acidity of the vaginal secretion and cannot be classified as its permanent flora. Later, Döderlein's bacillus predominates. Vaginal hemorrhages, incorrectly called menstrua neonatorum (since they do not have cyclicity), are observed in approximately 2% of all girls (Chebotarevskaya; Zhukovsky 35 cases per 10,000). They appear on the 3rd or 4th day and last from 2 to 5 days. Most often these are small serosanguineous and very rarely true abundant bloody discharges. They should not be confused with menstruatio praecox, which usually appears later, nor with septic hemorrhages from the vagina. If one examines the child through an ear speculum, it is visible that the blood flows from the uterus; several autopsies available in the literature indicate the presence of quite significant hyperemia of the endometrium. No special care is required for these small metrorrhagias—except for a small sterile pad in case of very abundant discharge in order to protect the legs from blood that is difficult to wash off.—In boys (approximately in 1/3) hydrocele of the scrotum (hydrocele) can be observed, which by no means has a traumatic origin, since it has been observed even during cesarean section at the moment of extraction of the child. During pathological-anatomical examination, enlargement of the testicles and prostate was found.
The most modern view is the one that attributes all the above-mentioned phenomena (mastitis, menstrua, hydrocele) to the so-called "reactions of the fetus to pregnancy." They are caused by the transfer from mother to fetus of various substances arising during the process of pregnancy. According to Halban, the irritants are substances that are produced by the chorion and circulate in the mother's blood. At the present time, the toxic erythema of the newborn, named so by Leiner because he saw its cause in the resorption of poisons from the intestinal tract, is also attributed to these same "reactions to pregnancy." During intrauterine life, the action of pregnancy poisons is neutralized by the action of the placenta. Upon the cessation of its action after the birth of the child, the still-circulating poisons and protein substances cause an allergic skin reaction in the newborn, analogous to serum sickness (Mayerhofer). A general (over 4%) and especially local hypereosinophilia is often found. There is also an opinion that toxic erythema is an early expression of exudative diathesis. Further observation of children by Dr. Kononova did not confirm this assumption. Toxic erythema appears on the 2nd-3rd day on the back, chest, elbows, face, and scalp, less so on the lower extremities; it can be very abundant, confluent; the red, irregularly shaped, sometimes raised spots often have an exudative nodule in the center, resembling a small urticarial wheal. The course is short (1-2 days), painless, and favorable. The rash often recurs. Dyspepsia of the newborn ("transitional catarrh") also belongs to physiological states. After the passage of meconium and the subsequent mixed or hunger stool, the stools take on a dyspeptic character, contain mucus, green matter, curds, are frequent, of liquid consistency, and have an acid reaction. They are an expression of irritation on the part of the intestinal mucosa, with which the latter reacts to unusual food, especially to breast milk rich in sugar, as well as to the appearance and change of the intestinal microbial flora. Vomiting and regurgitation are also associated with increased sensitivity of the stomach and insufficient closure of the cardia. Usually, these phenomena end or weaken by 2 weeks of life. Transient fever (transitorisches Fieber)—sudden and rapidly ending rises in temperature—is encountered in newborns on the 3rd-5th day of life in the absence of any pathological phenomena and often coincides with the moment of the greatest drop in the weight curve. They are observed not infrequently: Langstein in 13%, Haller in 17% of all newborns, last for a short time—from a few hours to 2-3 days—and should probably be linked to the dehydration of the child's organism (Durstfieber, Hungerfieber). Children with high birth weight have fever relatively more often than children with low birth weight. With insignificant weight loss, transient fever is not observed. Perhaps its cause lies not in the loss of water itself, but in the occurring changes in metabolism, which, of course, cannot take place in every child. The pathology of the newborn is almost exclusively reduced to infection, to which this age is so prone. Some diseases are peculiar only to newborns and do not recur in later life. Such are diseases of the navel, umbilical vessels, and pemphigus of the newborn. Other diseases, such as sepsis, are encountered at a later age as well, although significantly less often. In view of the newborn's susceptibility to infection, preventive measures are of great importance: strict hygiene of the mother in the last period of pregnancy, strictly aseptic approach to newborns, separating them from mothers who are often the primary sources of infection, early and strict isolation of sick children, etc. Pfaundler highly recommends boxing of wards for newborns and the use of masks for the nursing staff. Interesting is the type of crib-box proposed in Germany for this purpose with high glass walls, protecting the child from droplet infection. On the part of the skin, a typical disease for this age is pemphigus, or pemphigus of the newborn (see Pemphigus), which often causes real epidemics in institutions. A disease related to pemphigus is Ritter's dermatitis exfoliativa, characterized by a large extent of denuded surfaces, significant epidermolysis and desquamation, as well as a severe, often fatal course (see Dermatitis). Phenomena of sclerema and scleredema can be observed in the subcutaneous layer mainly in premature, and sometimes in full-term, but sick or chilled children (see Scleroderma). Regarding the oral cavity, the preventive slogan "Hands off the child's mouth!" has done its important work and significantly reduced the number of observed diseases, especially thrush (see). Sometimes so-called "palatal spots" are encountered in the form of grayish-white spots on the palate, with injected edges, of various shapes and sizes, which can far from always be linked to the wiping of mucus from the oral cavity at the birth of the child. Bednar's aphthae (see) are usually observed somewhat later. Septic enteritis and enterocolitis are sometimes one of the manifestations of sepsis, especially of enterogenic origin. Regarding melena, see Melaena. Relatively little is known about diseases of the urinary tract in newborns, partly due to the difficulties that collecting urine and functional examination of the kidneys present in newborns. Pyelitis of colibacillary origin is obviously encountered, but often passes unnoticed (Sauer). Nephritis or, more often, nephrosis, although rare, are encountered in syphilitics, in sepsis, and possibly in other infections. They can occasionally be observed in children of mothers suffering from nephritis and eclampsia. A case of hemorrhagic nephritis with 1% protein has been described in a 14-day-old child born to an eclamptic mother. Eye diseases in newborns must be the subject of special attention in view of the danger of their infection during childbirth. In addition to gonococcal conjunctivitis (see Blennorrhoea), conjunctivitis of other origins is also encountered, sometimes very persistent and similar in course to gonococcal diseases. Their causative agents are other diplococci or cocci. Their course is usually more favorable, and treatment is generally analogous to the treatment of blennorrhoea. Already in the first days, dacryocystitis can be observed in newborns due to the closure of the lumen of the nasolacrimal duct by an embryonic membrane or a mucous-gelatinous plug. Purulent otitis is not so rarely encountered during autopsies of children who died from some infection, and most often it is secondary. Reis observed bilateral otorrhea as early as the first day of life. The penetration of infected amniotic fluid into the tympanic cavity plays a definite role here. Erysipelas has its own peculiarities in newborns. Being an expression of sepsis, it very often leads to death. Clinically, it often takes on special forms in newborns—bullous, phlegmonous—and often appears in various parts of the body. There is no sure remedy for this disease. In the opinion of some authors, intensive hemotherapy supposedly gives promising results. Others have obtained a good result from the antivirus according to Besredka. American authors recommend draining the child's blood until pallor and immediately replacing it with blood of the same group, if possible, maternal. Diseases of the navel are reduced mainly to infection of this area. Bleeding from the navel—omphalorrhagia—is observed, which can be early and late. The former are most often a consequence of insufficiently tight ligation and, in the rarest cases, a symptom of congenital hemophilia. Late bleeding, however, is in most cases associated with a general infection of the organism, such as sepsis or syphilis. A mild infection is sometimes expressed only by slight suppuration, proliferation of granulations, and longer healing (weeping navel, umbilical fungus). More severe infections include umbilical ulcer, diphtheria, inflammation of the navel, or omphalitis, and finally, gangrene of the navel, which is now a great rarity and affects emaciated, weak children, especially during severe sepsis. Finally, the infection can also affect the umbilical vessels, whereby the external appearance of the navel can be completely normal, and the wound can even close. Arteries are affected more often than the vein, the infection of which is, of course, more dangerous in view of the possibility of its carriage into the general bloodstream. The causative agents of the infection (most often streptococci and staphylococci) cause the disintegration of vascular thrombi—hence the picture of thromboarteritis or thrombophlebitis. The infection can localize in the segments of the arteries adjacent to the navel and proceed favorably, and sometimes even unnoticeably, with slight temperature elevations and purulent discharge from the navel (pyorrhoea). With the spread of the infection deep inside, the bloodstream is flooded with infected products of thrombus disintegration, and the danger of such thromboarteritis totalis is enormous. Death often occurs on the eighth day, sometimes significantly later—in the seventh-eighth week of life. All attention must be directed to prevention, i.e., thorough asepsis in relation to the umbilical cord. Treatment: removal of the umbilical cord remnant, if any, hydrogen peroxide; in case of pyorrhoea, a probe is passed, and the opening is widened for drainage. General treatment is, of course, also necessary.
The umbilical wound can also serve as a portal of entry for infection by the tetanus bacillus, which is currently a great rarity in urban obstetric conditions (see Tetanus). The mortality rate at this tender age is high (93 according to consolidated statistics). According to Finkelstein, 62% in 25 cases treated with serum. Sepsis, to which the organism of the newborn is so prone, is the most severe disease of this age. The gastrointestinal tract, skin, respiratory tract, and umbilical cord can all serve as portals of entry. Infection occasionally occurs in utero, but most often during and after childbirth. A characteristic circumstance is that sepsis can arise in a newborn from a small skin wound (for example, an abrasion from forceps), from dirty amniotic fluid swallowed and aspirated by the child, or from a mild influenza-like illness that subsequently causes otitis, pneumonia, and a general infection of the organism. Accurate intravital diagnosis is made under the control of blood culture by puncturing the longitudinal sinus or any vein of the child. The clinical picture is distinguished by great variety: from violent forms with a fulminant course to protracted and latent ones, with barely expressed symptoms. Classic symptoms are sharp and early jaundice, a "septic appearance" of the child, swelling of the spleen, and various hemorrhages (but they are not always present); the temperature may show only slight rises or be below normal. Sometimes a protracted septic-pyemic form is also observed with the formation of metastases, in particular in the epiphyses of long bones and in the joints (epiphyseal osteomyelitis and purulent arthritis). Hemorrhagic forms of sepsis now also include those phenomena that were previously described under the name "hemorrhagic diathesis," as well as Buhl's disease and Winckel's disease (see Buhl's disease and Winckel's disease). Among treatment methods, preference should be given to early and intensive hemotherapy. American authors withdraw 30-100 cm3 from the child and immediately inject the same amount of same-group blood intravenously. In Robertson and Brown (Canada), 8 out of 29 cases of septicemia recovered. In the opinion of some authors, the mother is a physiological donor for her child, and her blood can be used even in case of blood group incompatibility. Citrated blood is injected into the longitudinal sinus, into any accessible vein, intramuscularly, and finally intraperitoneally. The operation should be repeated daily, up to 5-6 times in total, guided by careful clinical observation and the blood picture. It goes without saying that all means—cardiac stimulants, oxygen, careful feeding with expressed breast milk—must be applied in this difficult struggle. It is interesting to note the response of the newborn to infection. The fact that newborns, even during those infections to which they are prone, react differently than the more adult organism, both in terms of local and general reactions, has given reason to speak of "newborn allergy." Newborns are little susceptible to common childhood infectious diseases, partly probably due to passive immunity received from the mother. The fact of the transfer of antibodies from the mother's serum to the fetus has been proven by many authors (Kitasato, Schick, Ehrlich, et al.); purely passive immunity (measles) is, of course, transient. Another reason for low susceptibility may be insufficient differentiation of fetal cells. From this follows the insufficiency of receptors (Ehrlich) intended for the fixation of antigens. Probably, in the early stage of intrauterine life, the fetus is not infected, and then, as receptors develop, its susceptibility to infection increases. The possibility of independent production of antibodies by the fetal organism is not excluded. Their quantity seems to increase somewhat after birth, but still, in the first months of life, their production proceeds sluggishly, and the administration of therapeutic and prophylactic sera does not seem to have the same effect as in older children. All these interesting questions await their final resolution. The low susceptibility of newborns to childhood infections, however, presents significant fluctuations. Thus, in relation to smallpox, susceptibility is quite strong, and children of mothers with smallpox are also often born sick in the stage of eruption or even scarring. Children of mothers who have had measles have absolute immunity in the first 2 months, relative immunity up to 5 months, and after 9 months all children are susceptible to measles. Observations show that newborns of mothers who have not had measles do not have measles immunity (Bartsch on the Faroe Islands, et al.). The incidence of scarlet fever in newborns is negligible, and the described cases are isolated. When evaluating them, one must remember the possibility of diagnostic errors. Diphtheria is rare in newborns, mainly in the form of nasal diphtheria. Weak children are predominantly affected, while healthy ones show a certain resistance. Diphtheria of the navel, skin, and penis after circumcision is possible. Kassowitz and Schick found the Schick reaction to be negative in 84%, and Fischl and Groer found umbilical cord blood to be antitoxic and bactericidal against the Loeffler bacillus. Whooping cough is observed as a very rare exception during the first two weeks of life. Malaria can be transmitted from mother to fetus during the act of childbirth or earlier in cases where the placental filter is impaired due to existing damage. Cases of typical attacks have been described as early as the 1st day of life, as well as interesting cases of "carriers" of plasmodia. Along with the resistance of newborns to some infections, it is interesting to note their great susceptibility to lues, to gonorrhea, and to pyogenic and septic processes. A hypothesis (Achalme) has been put forward about a decrease in the phagocytic capacity of newborn leukocytes. Finally, of the two chronic infections—syphilis and tuberculosis, which play such an important role in the life of humanity, neither spares the newborn child. In terms of frequency, congenital syphilis certainly holds first place compared to tuberculosis, the congenital clinical forms of which are an extremely great rarity (see Syphilis, congenital syphilis, Tuberculosis).
Related articles
Mentioned in
Cite this page
“Newborn.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.pages.dev/article/newborn/